Transformative Facial Feminization: A Deep Dive into Personalized Surgical Approaches

A close-up side profile of a woman wearing a high-necked, light orange top and small hoop earrings with a gemstone. She has smooth, dark hair and is posing against a plain brown background.

Facial Feminization Surgery (FFS) represents a deeply intricate and profoundly personal journey. It offers a transformative pathway for individuals seeking to align their external appearance with their affirmed feminine identity. This highly specialized field within craniofacial and plastic surgery transcends mere aesthetic enhancements. It demands a meticulous, individualized approach that acknowledges the profound and inherent variations in human facial anatomy. The fundamental principle guiding successful facial feminization is understanding that no two faces are identical. Nor do they present the same set of masculine characteristics to be addressed. Therefore, a “one-size-fits-all” methodology is inherently inadequate for achieving optimal, natural-looking, and deeply satisfying results. Instead, the process necessitates a bespoke surgical strategy. This strategy is meticulously tailored to each patient’s unique underlying skeletal and soft tissue architecture. This architecture is a complex interplay of genetic predisposition, developmental factors, and the effects of hormonal influences.

This comprehensive guide will delve into the critical role of distinctive facial anatomy. It shapes the precise surgical interventions and techniques employed during FFS. We will underscore how a nuanced appreciation of individual features culminates in a truly personalized and effective transformation. We will explore how expert surgeons navigate the complex landscape of craniofacial differences between sexes. These differences range from the subtle contours of the brow to the more pronounced angles of the jaw. We will also examine how these anatomical nuances directly inform the selection and execution of feminizing procedures. The objective is not merely to soften overtly masculine traits. It is to sculpt a cohesive and balanced facial appearance that authentically reflects the individual’s gender identity. This enhances psychological well-being, alleviates gender dysphoria, and facilitates social affirmation (Barnett et al., 2023).

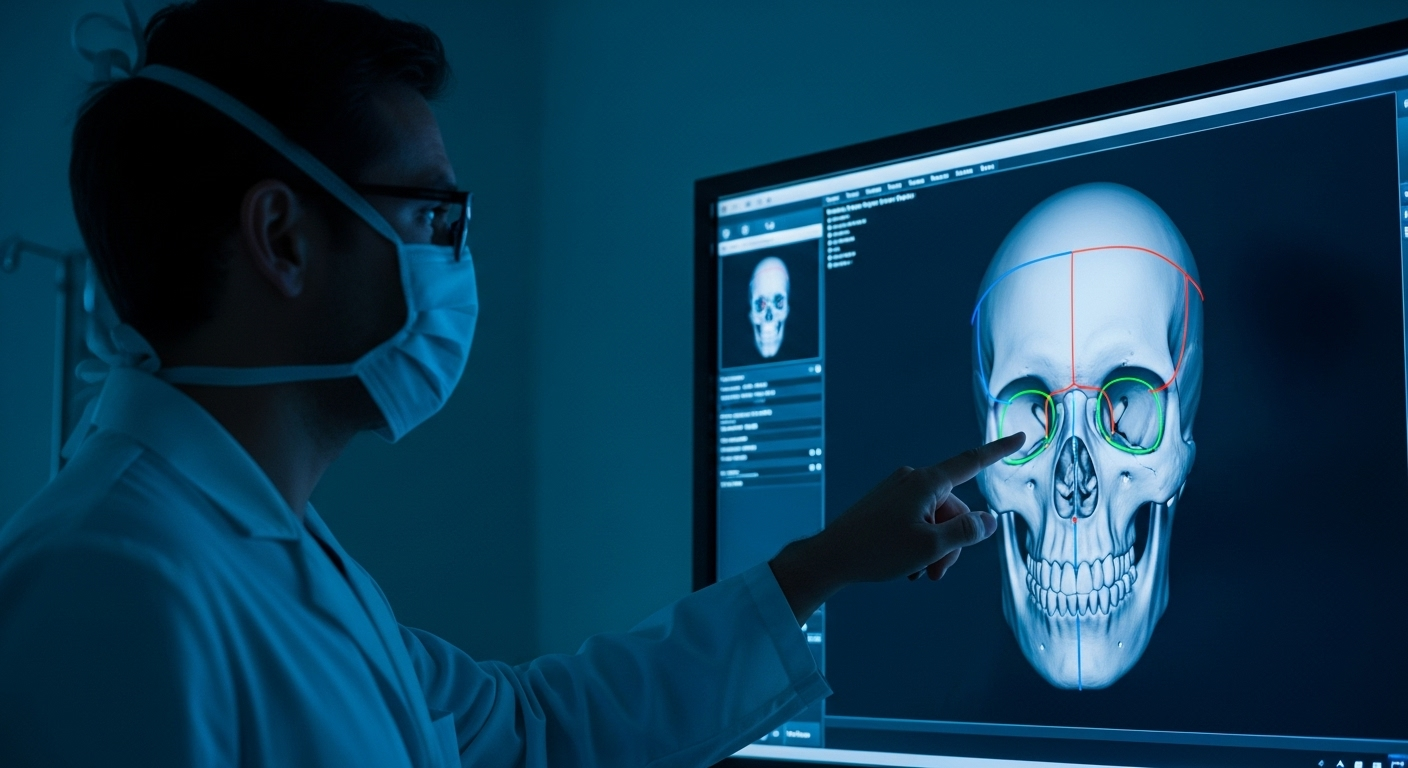
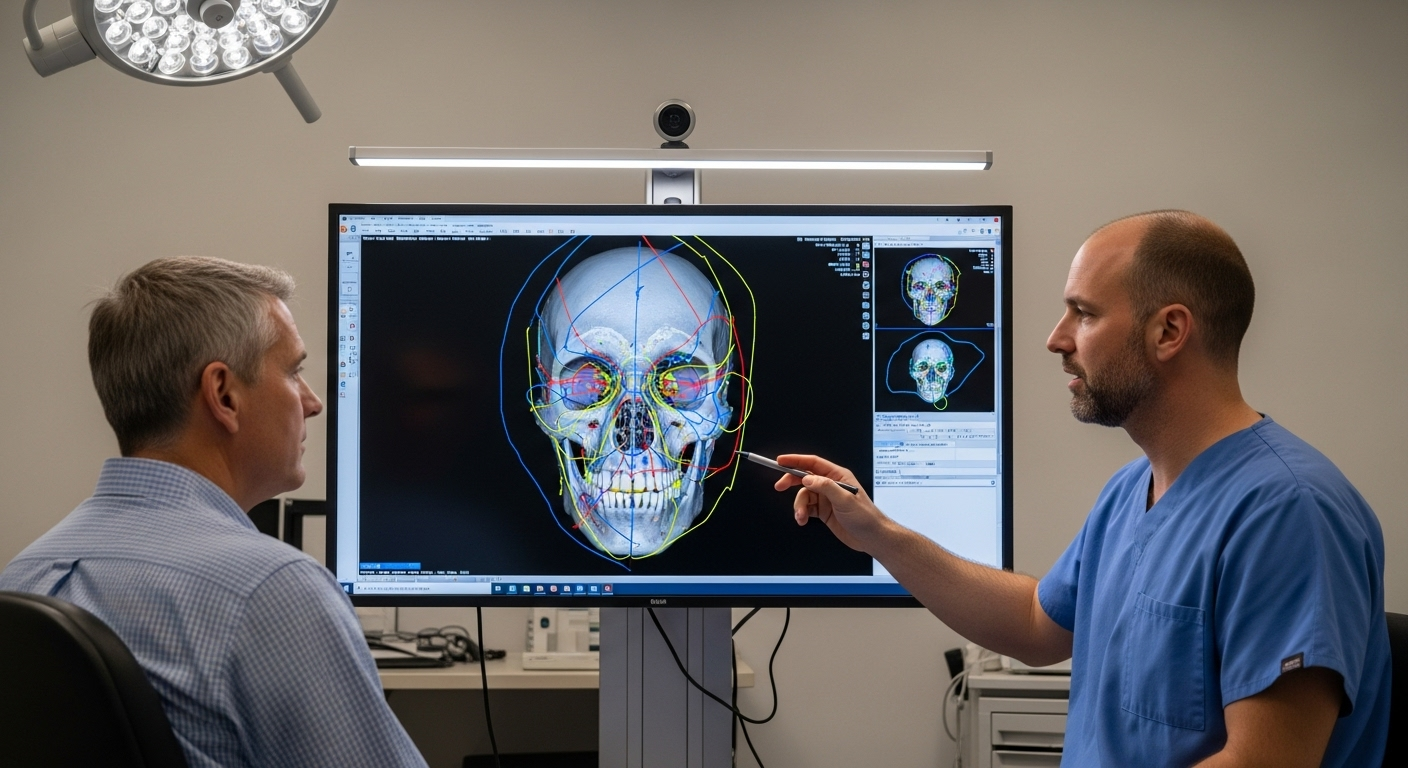
This exploration will highlight the advanced diagnostic tools. These include high-resolution 3D imaging and sophisticated virtual surgical planning systems. These tools empower surgeons to create a detailed, three-dimensional blueprint of the patient’s face. This technological integration enables an unprecedented level of precision in preoperative strategizing. It allows for simulated outcomes and customized surgical guides. Furthermore, we will examine how various surgical techniques are synergistically integrated. These encompass both osseous (bone) modifications, which address the fundamental framework of the face, and soft tissue refinements, which provide the delicate finishing touches. The goal is to produce a harmonious outcome that maintains naturalness while achieving profound feminization.

The discussion will extend to the critical considerations involved in managing patient expectations. This ensures they are grounded in surgical realism. It also ensures an understanding of the unique challenges posed by significant anatomical variations. We will also emphasize the paramount importance of selecting a highly experienced specialist. This specialist possesses a deep understanding of both aesthetic principles and complex craniofacial reconstruction. Ultimately, this detailed analysis aims to illuminate the profound interplay between individual facial anatomy and surgical artistry. It reveals how a deeply personalized approach is not just beneficial, but absolutely the cornerstone of transformative, durable, and profoundly impactful facial feminization outcomes.

A woman with long dark hair is standing in an art gallery, looking thoughtfully at a piece of artwork on the wall. She is wearing a black top and has her hand resting on her chin.

Understanding the Blueprint: Foundational Anatomy for Facial Feminization

Before any surgical intervention commences, a profound understanding of the patient’s foundational facial anatomy is paramount. A skilled facial feminization surgeon meticulously assesses the intricate interplay of underlying bone and overlying soft tissue structures. This comprehensive evaluation is critical because inherent differences in skeletal proportions and soft tissue distribution are key determinants of perceived gender.

Typically, masculine facial features often involve a more prominent brow ridge, a broader and squarer jawline, a larger and more anteriorly projected chin, and a distinct nasal profile characterized by a higher bridge and less upward rotation of the tip. However, the degree of expression of these features varies significantly among individuals due to genetic, ethnic, and developmental factors (Alraddadi, 2021). Recognizing these individual anatomical nuances is not merely an observational step but the foundational prerequisite for crafting a truly tailored and effective surgical plan.

To acquire this detailed anatomical blueprint, advanced diagnostic imaging plays an indispensable role. Three-dimensional computed tomography (3D CT) scans are frequently employed, providing a high-resolution, three-dimensional reconstruction of the patient’s unique skeletal and soft tissue architecture. These scans offer an unparalleled view of bone density, sinus pneumatization, nerve pathways, and the precise contours of the facial skeleton (Barnett et al., 2023). This data is then utilized in conjunction with virtual surgical planning (VSP) software, allowing surgeons to precisely measure existing structures and simulate potential surgical modifications.

Beyond static images, dynamic assessments of soft tissue mobility, skin elasticity, and muscle activity are also incorporated. Understanding the variations in tissue thickness and elasticity, for instance, is crucial for anticipating how overlying soft tissues will redrape following bone reductions or augmentations. The combination of comprehensive physical examination and advanced imaging provides the surgeon with a holistic understanding of the patient’s facial landscape, enabling them to formulate a feminization strategy that is both anatomically sound and aesthetically harmonious, moving beyond generic ideals to achieve results that are authentic to the individual.

A close-up photograph of a person's eye, focusing on the detailed texture and color of the iris and surrounding skin.

Regional Deep Dive: Anatomical Impact on Specific Feminization Techniques

The Forehead and Orbital Rims: Sculpting a Feminine Foundation

The upper third of the face, comprising the forehead and orbital rims, is a primary region for gender recognition. Variations in the frontal bone and supraorbital ridge (brow bone) are among the most significant sexually dimorphic features. Masculine foreheads often present with a prominent brow bossing, a heavier and more horizontally positioned brow relative to the superior orbital rim, and a forehead that recedes backward. In stark contrast, feminine foreheads are typically characterized by a smoother, rounder contour, a more vertically oriented profile, and eyebrows that arch higher, positioned above the orbital rim (Barnett et al., 2023). The degree of frontal bossing can vary considerably among individuals, directly impacting the complexity and choice of surgical intervention.

These anatomical variations directly influence the selection of forehead contouring procedures, primarily categorized into Type 1 (shaving), Type 2 (combination), or Type 3 (setback) techniques. For individuals with a relatively thick anterior frontal sinus wall and less pronounced bossing, a Type 1 procedure, involving direct burring or shaving of the prominent bone, may suffice to create a smoother transition. However, when the frontal sinus bone is thinner or the brow bossing is significantly prominent, a more extensive approach is often necessitated.

A Type 3 cranioplasty, also known as frontal sinus setback, involves carefully removing the anterior wall of the frontal sinus, meticulously reshaping it, and then reattaching it in a more recessed and feminized position (Barnett et al., 2023; Dr. MFO, 2025c). This reconstructive technique allows for a greater degree of reduction and a more profound feminizing effect, fundamentally altering the supraorbital contour and achieving the desired convex curvature of a feminine forehead.

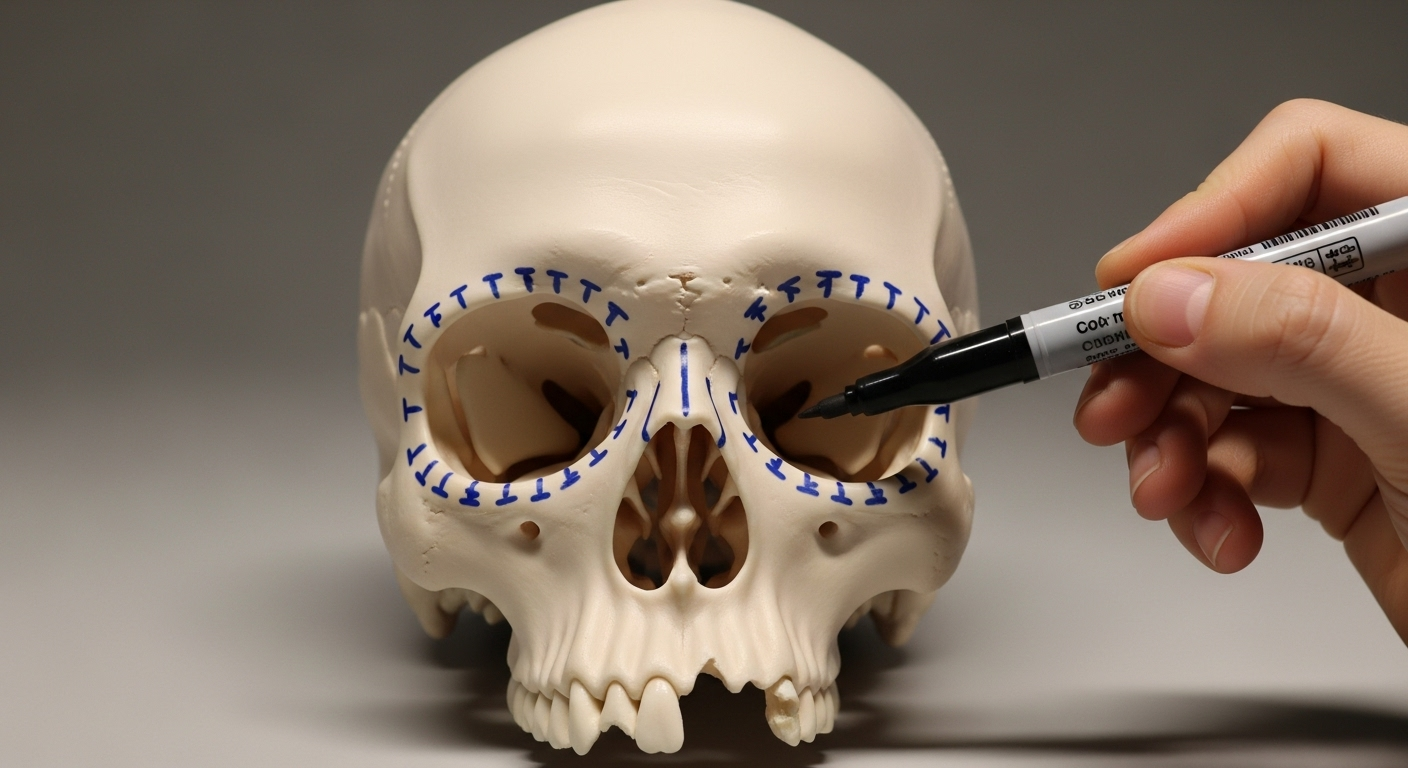
In conjunction with forehead contouring, orbital rim contouring is frequently performed to further enhance upper facial feminization. In masculine faces, the bony edges around the eye sockets can appear heavier and more angular, often casting shadows that masculinize the eyes. By carefully smoothing and rounding these edges, the eyes appear larger, more open, and less shadowed, contributing to a softer, more inviting gaze. The precise execution of these modifications, especially near critical structures such as the supraorbital and supratrochlear nerves, is paramount to prevent sensory deficits.

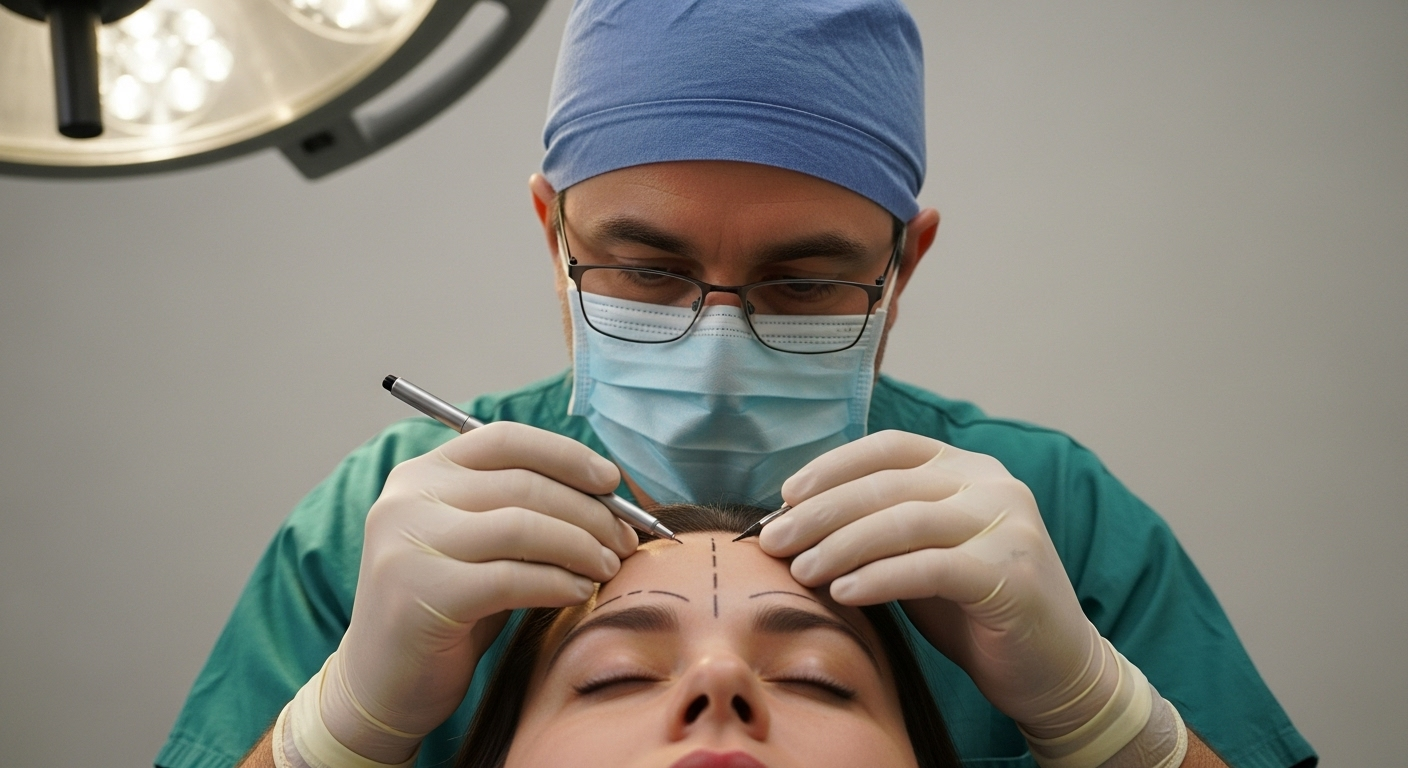
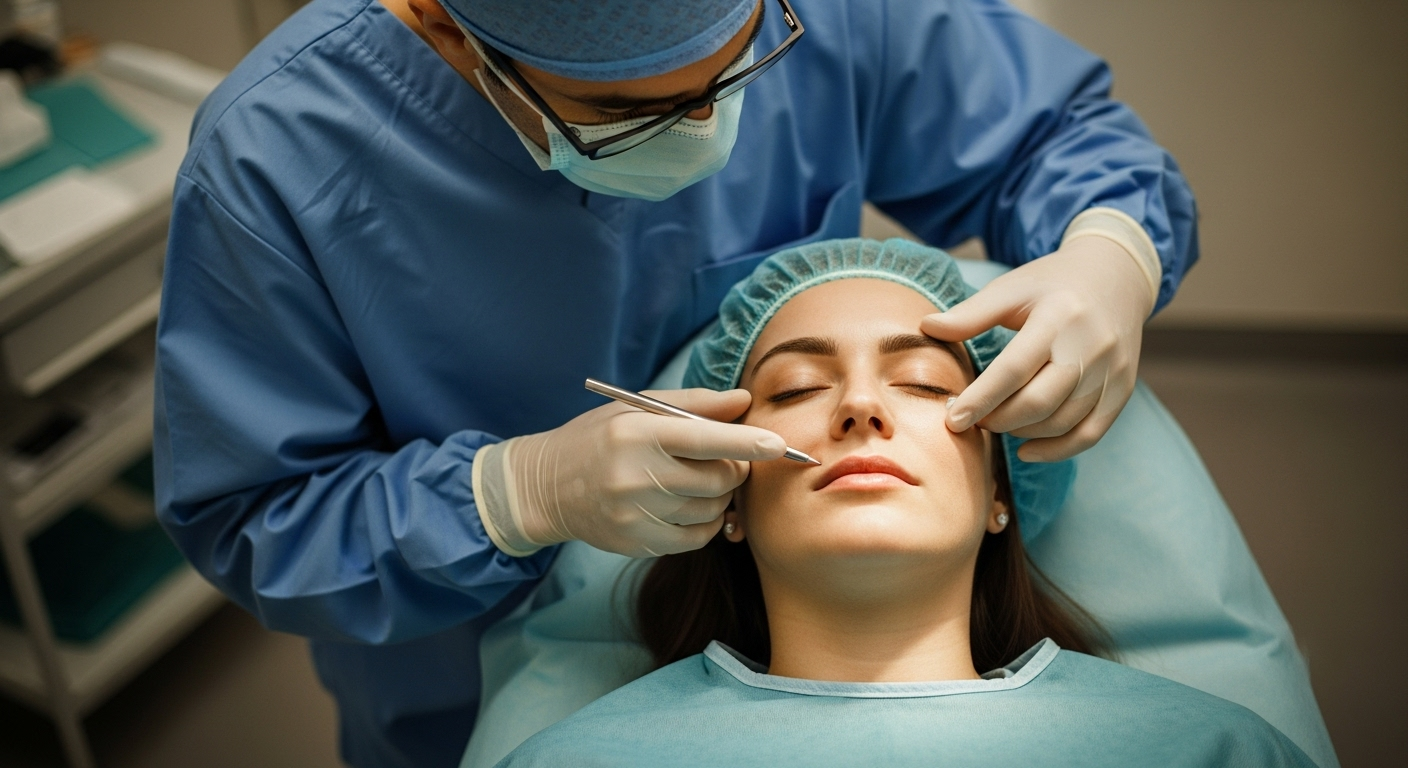
Additionally, the natural hairline position and any existing brow descent will guide the selection of brow lift techniques. A coronal incision, extending across the scalp, may be chosen for significant hairline advancement combined with forehead contouring, whereas an endoscopic brow lift, utilizing smaller incisions within the hairline, can achieve brow elevation with minimal hairline change, particularly when hairline lowering is not a primary objective. Virtual surgical planning, as detailed by Barnett et al. (2023), has emerged as an indispensable tool, allowing surgeons to precisely visualize desired outcomes and plan osteotomies with enhanced accuracy, significantly reducing operative time and minimizing complications like over-resection or nerve injury. This meticulous pre-surgical mapping ensures that the altered contours integrate seamlessly with the rest of the face, providing a harmonious and distinctly feminine upper facial aesthetic.

Midface and Cheeks: Sculpting Softness and Projection

The midface, prominently defined by the zygomatic (cheekbone) complex and the overlying soft tissues, plays a pivotal role in the perception of facial femininity and youthfulness. Significant variations exist in midface projection and contour between masculine and feminine physiognomies. Masculine midfaces often exhibit flatter zygomas with less anterior projection, contributing to a less triangulated facial shape. In contrast, feminine cheeks are typically characterized by higher, more anteriorly positioned zygomatic arches, creating a desirable convexity and contributing to a softer, more youthful, and often “heart-shaped” facial contour (Barnett et al., 2023). The distribution and volume of subcutaneous fat, including the malar fat pad and buccal fat, also vary considerably, further influencing overall midface appearance.

Surgical strategies for midface feminization are highly individualized, contingent upon the patient’s existing anatomical structure and desired aesthetic. When there is insufficient malar projection or a naturally flatter midface, cheek augmentation is often recommended. This can be achieved through various methods. Autologous fat grafting, which involves harvesting fat from other areas of the patient’s body (e.g., abdomen or thighs) via liposuction, processing it, and then injecting it into the cheeks, offers a natural solution. This technique provides a soft, natural-looking augmentation and can simultaneously improve the quality of the overlying skin. Alternatively, custom alloplastic implants, typically made of biocompatible materials such as silicone, can be placed over the cheekbones to provide permanent volume and definition. These implants are either pre-designed or custom-fabricated based on 3D virtual surgical planning to precisely match the desired contours (Barnett et al., 2023).

Conversely, in rare instances where cheekbones are excessively wide or prominently angled in a masculine manner, a surgeon might consider zygomatic arch reduction to soften the midface width. Furthermore, the distribution of buccal fat—a deep fat pad located within the cheek—can impact facial fullness. For individuals with a fuller, rounder lower face that detracts from a feminine aesthetic, buccal fat pad removal may be considered to create a more defined and hollowed submalar region, enhancing the appearance of higher cheekbones.

The delicate interplay between these procedures allows for the creation of an “ogee curve”—a graceful, double S-curve contour from the temple to the cheek, which is highly indicative of youthful, feminine cheeks. When combining nose and cheek procedures, as highlighted by Dr. MFO (2025b), synergistic anatomical planning is critical due to the interdependence of nasal and midface aesthetics. An overly prominent nose, for example, can make the midface appear recessed, while well-projected cheekbones can visually balance a nose. Therefore, modifications in one area profoundly influence the perception of the other, requiring an integrated approach to achieve overall facial harmony.

The Nose: Achieving Delicate Proportions

The nose, positioned centrally on the face, is a critical feature that significantly influences overall facial balance and perceived gender. Nasal structures exhibit immense diversity, yet distinct patterns contribute to gender recognition. Masculine noses often feature a broader nasal bridge, a more prominent dorsal hump, wider nostrils (alar base), and a less upwardly rotated, sometimes even downwardly projecting, nasal tip. In contrast, feminine noses are typically characterized by a smaller overall size, a narrower bridge, a softer or slightly concave dorsal profile, and a more refined, slightly upturned nasal tip, contributing to a more obtuse nasolabial angle (Barnett et al., 2023).

This wide spectrum of nasal anatomy necessitates a comprehensive range of rhinoplasty techniques during facial feminization. Dorsal hump reduction is a common procedure, involving the careful removal or rasping of excess bone and cartilage along the nasal bridge to create a smoother, more delicate profile. Concurrently, narrowing the nasal bones through osteotomies (controlled bone cuts) helps to reduce the overall width of the nasal bridge, contributing to a more refined appearance. Tip plasty techniques are pivotal for feminizing the nasal tip; these involve meticulous reshaping of the lower lateral cartilages through excisions, sutures, and grafts to make the tip smaller, more defined, and appropriately rotated upward (Barnett et al., 2023; Dr. MFO, 2025c). Alar base reduction may be performed to narrow excessively wide nostrils, which can be a masculine characteristic, ensuring the nasal base is proportionate to the feminized tip and bridge. The specific aims are to create a nose that harmonizes with the newly contoured forehead and midface, avoiding an overly aggressive or artificial appearance.

An open rhinoplasty approach, utilizing a small incision across the columella and internal incisions, is often favored in facial feminization due to the optimal access and visibility it provides to the underlying skeletal and cartilaginous framework. This allows the surgeon to precisely manipulate structures and address specific feminizing goals, such as caudal septal trimming for upward tip rotation (Barnett et al., 2023). The intricate relationship between the bony and cartilaginous components of the nose demands a highly skilled surgeon to achieve stable and aesthetically pleasing results.

Furthermore, the soft tissue envelope, comprising skin, subcutaneous fat, and muscle, plays a significant role in the final outcome; its thickness and elasticity determine how readily underlying changes will be revealed. Consideration of the nasal vascular supply, primarily from branches of the ophthalmic and facial arteries, and innervation from the trigeminal nerve, is crucial to minimize complications such as bleeding or sensory changes. The ultimate goal is to sculpt a nose that is in harmonious proportion with the overall feminized facial features, enhancing the patient’s self-perception and social comfort (Dr. MFO, 2025c).

Jawline and Chin: Softening the Lower Face

The lower third of the face, particularly the jawline and chin, are primary indicators of sexual dimorphism and significantly contribute to perceived gender. Masculine jawlines are typically broader, squarer, and more angular, often presenting with prominent mandibular angles and a thicker external oblique ridge. The chin in masculine faces can be wider, squarer, or excessively prominent, contributing to a strong, sometimes blunt, lower facial appearance. Conversely, feminine jawlines are generally narrower, more tapered, and often exhibit a graceful V-shape or oval contour with softer angles. The chin in feminine faces is typically more delicate, with less width and projection, contributing to a refined lower facial profile (Barnett et al., 2023).

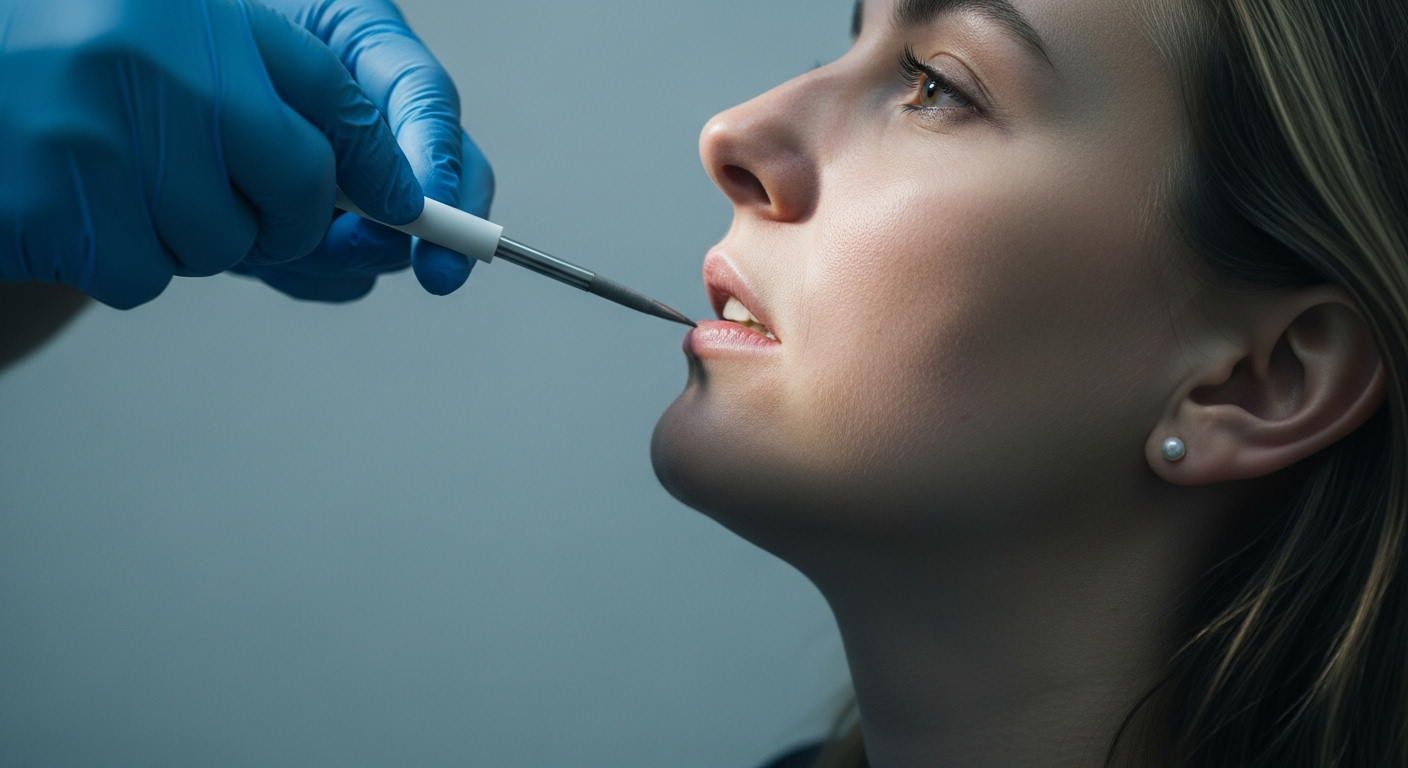
Surgical strategies for feminizing the jawline and chin involve meticulously tailored osseous modifications. Mandibular angle reduction is a key procedure designed to soften the posterior jawline. This involves carefully shaving or resecting a portion of the bone at the prominent jaw angles, transforming a square contour into a smoother, more tapered transition from the ear to the chin. This procedure is often performed through intraoral incisions (inside the mouth) to avoid visible external scarring, allowing for precise osteotomy and contouring while mitigating damage to vital structures such as the inferior alveolar nerve (Barnett et al., 2023; Dr. MFO, 2025c).

Chin reshaping, or genioplasty, addresses the size, projection, and shape of the chin. In facial feminization, the goal is often to reduce chin width, shorten its vertical height if it is excessively long, and/or reshape it to a more pointed or rounded form, depending on the patient’s desired outcome and existing anatomy. A common technique is the sliding genioplasty, where the chin bone is carefully cut horizontally, and the distal segment is repositioned. This segment can be moved backward for reduction, advanced for increased projection, vertically shortened, or narrowed to achieve the desired delicate, feminine contour. The repositioned bone segment is then secured with small plates and screws to ensure stability and predictable healing (Barnett et al., 2023; Dr. MFO, 2025c).

For chins that primarily require reduction in width or projection without significant repositioning, direct bone shaving or burring can be performed. The integration of these procedures often culminates in a “V-line” surgery, which combines mandibular angle reduction and genioplasty to create a significantly more tapered and feminine lower facial silhouette. In some cases, masseter muscle reduction, either surgically or through botulinum toxin injections, may also be considered for individuals with hypertrophied (enlarged) jaw muscles contributing to excessive lower facial width. The combined effect of these carefully planned interventions results in a more graceful, harmonious, and distinctly feminine lower face, balancing the features modified in the upper and mid-face (Dr. MFO, 2025a).

The Trachea: A Smoother Neckline

The laryngeal prominence, commonly known as the Adam’s apple, is a distinct secondary sex characteristic. It develops and becomes more prominent during male puberty due to the enlargement and acute angle of the thyroid cartilage. Its presence can be a significant source of gender dysphoria for many transgender women. This is because it is a highly visible feature immediately indicative of a masculine neck profile. A tracheal shave, also known as chondrolaryngoplasty, is a straightforward yet highly effective feminizing procedure. It is specifically designed to reduce the size and prominence of the Adam’s apple (Barnett et al., 2023; Dr. MFO, 2025c).

The procedure typically involves making a small, discreet transverse incision in a natural skin crease on the neck. This is often at the midpoint between the submental crease and the cervicomental angle, to minimize the visibility of any resulting scar. Through this incision, the surgeon carefully shaves down the most prominent part of the thyroid cartilage. This reduces its projection and creates a smoother, softer contour of the neck. Extreme care is taken to preserve a rim of cartilage superior to the level of the vocal cords for stabilization. Crucially, it avoids damaging the vocal cords themselves, which are located just behind the cartilage (Barnett et al., 2023). This meticulous approach ensures that vocal function is preserved. While primarily a modification of cartilage, which is a form of skeletal tissue, the tracheal shave profoundly impacts the overall appearance of the neck and profile. It contributes to a more feminine silhouette and alleviates a significant source of dysphoria.

The recovery from a tracheal shave is generally quicker than from more extensive bone procedures. Most acute swelling and discomfort subside within a few weeks. Patients may experience some temporary voice changes or a sensation of tightness immediately after the surgery. However, these usually resolve as the healing progresses. In some cases, submental fat excision and platysmaplasty (neck muscle tightening) may be performed concurrently. This further enhances the desired neck silhouette and achieves maximal skin tightening, especially in older patients where skin laxity is a greater concern (Barnett et al., 2023). For many individuals, achieving a smoother neckline provides immense psychological relief. It allows them to feel more comfortable and confident in their appearance, particularly when wearing clothing that exposes the neck. This relatively contained procedure offers a significant impact on overall gender affirmation. It addresses one of the most visible masculine features of the head and neck region.

Integrating Techniques for Holistic Feminization: The Art of Synergy

True facial feminization rarely involves a singular procedure. Instead, it is an intricate symphony of coordinated surgical interventions. Each intervention is meticulously planned to complement the others. It aims to holistically address the patient’s unique anatomy. The skilled surgeon acts as an architect. They orchestrate a series of modifications, ranging from fundamental bone restructuring to subtle soft tissue refinements. The goal is to achieve a balanced, harmonious, and naturally feminine outcome. This integrated approach ensures that the overall result is cohesive and congruent with the patient’s gender identity. It is not merely a collection of isolated, disconnected changes. The synergy between procedures is paramount, as altering one facial component inevitably influences the perception and aesthetics of adjacent and distant features.

For instance, a reduction in brow bossing not only feminizes the forehead but also optically enlarges the eyes, making a subtle rhinoplasty’s impact even more pronounced. Similarly, jawline and chin reshaping procedures provide a narrower foundation, over which soft tissues drape more delicately, enhancing the effect of cheek augmentation and lip lifts. The thoughtful sequencing and combination of these techniques are what elevate facial feminization from mere surgical alteration to a sophisticated art form.

The decision for a comprehensive, single-stage facial feminization surgery versus a staged approach (multiple surgeries performed over time) is heavily influenced by the anatomical complexity of the case, the patient’s overall physical health, and personal preferences. While a single-stage procedure offers the convenience of one recovery period and often significant cost savings, patient safety remains the ultimate priority. Studies indicate that an increased number of procedures performed per anesthetic event in facial feminization patients does not necessarily predict higher complication rates, suggesting that well-planned, comprehensive single-stage approaches can be safely undertaken under appropriate medical judgment (Barnett et al., 2023).

However, for individuals with extensive surgical needs, significant medical comorbidities, or those who prefer to recover from smaller interventions sequentially, a staged approach may be more appropriate. In such cases, structural hard tissue procedures like frontal sinus setback, supraorbital contouring, jawline tapering, and rhinoplasty are often prioritized, followed by subsequent soft tissue procedures like facelifts, neck lifts, and blepharoplasty, particularly in older patients where skin laxity is a consideration (Barnett et al., 2023; Dr. MFO, 2025c). This strategic sequencing ensures that the foundational skeletal changes are established before refining the overlying soft tissues, thereby optimizing both the aesthetic and functional outcomes. Regardless of the staging strategy, the overarching goal is to achieve seamless integration, where each surgical modification contributes harmoniously to the final feminine facial contour.

Preoperative Planning and Technological Advancements for Precision

The success of advanced facial feminization surgery, particularly in cases involving significant anatomical variations, hinges critically on comprehensive and precise preoperative planning. This crucial phase has undergone a profound revolution with the integration of cutting-edge imaging modalities and virtual technologies, offering an unprecedented level of accuracy and predictability. High-resolution imaging, such as Cone-Beam Computed Tomography (CBCT) and standard Computed Tomography (CT) scans, provides detailed three-dimensional anatomical data of the patient’s skull and overlying soft tissues (Barnett et al., 2023).

This granular data is absolutely essential for an accurate diagnosis of existing skeletal differences, including bone volume deficits, subtle asymmetries, malposition of facial segments, and a precise assessment of critical underlying structures such as nerve pathways and sinus cavities. The detailed understanding derived from these images forms the fundamental bedrock upon which the entire surgical strategy is built, allowing surgeons to meticulously map out the existing anatomy and pinpoint all areas requiring correction or augmentation.

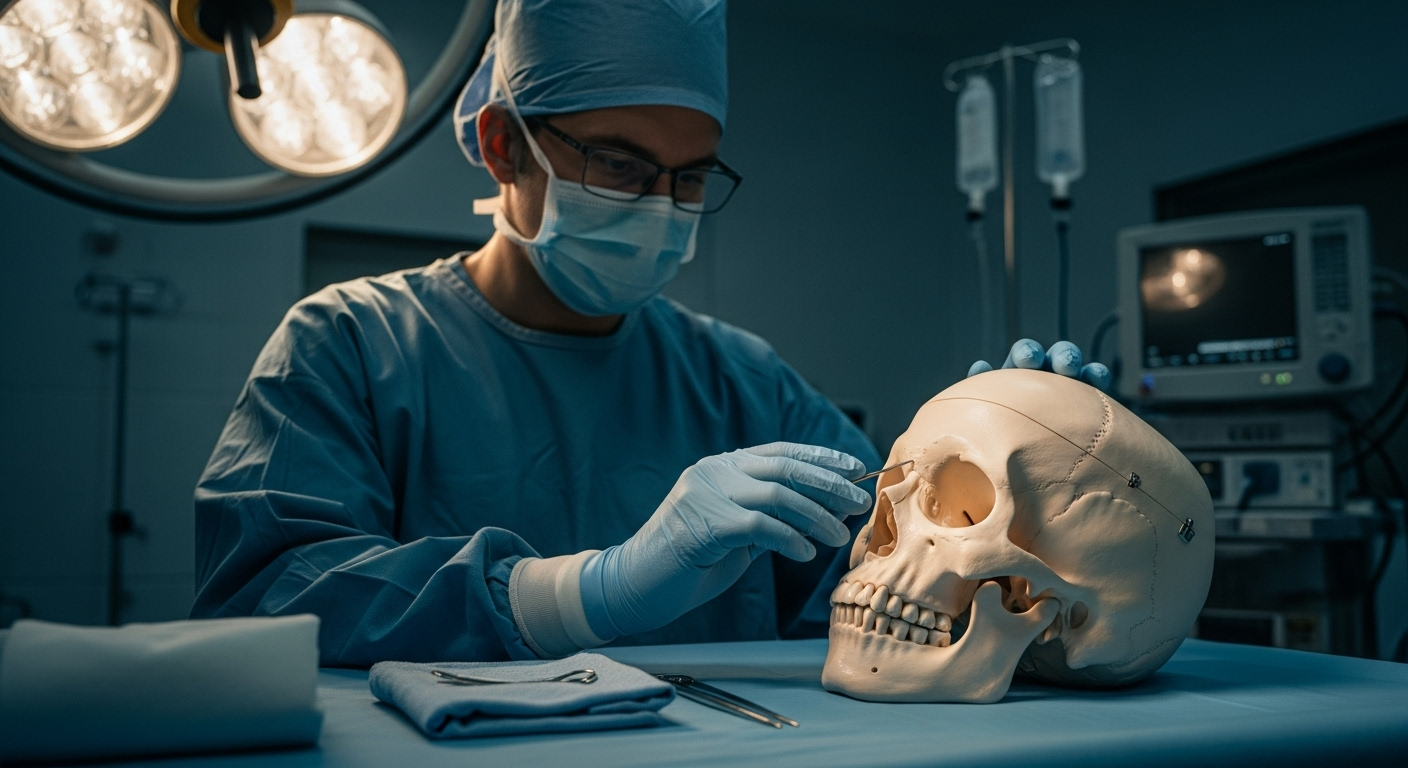
Building upon this rich imaging data, three-dimensional virtual surgical planning (VSP) systems have become indispensable tools in contemporary facial feminization. VSP involves importing the patient’s CT or CBCT data into specialized software, where a precise 3D digital model of the face and skull is generated. Within this sophisticated virtual environment, surgeons can meticulously plan every osteotomy (bone cut), bone graft placement, and custom implant positioning. This digital platform allows for the simulation of various surgical scenarios, enabling surgeons to virtually adjust bone segment movements, refine contours, and visualize the potential aesthetic and functional outcomes before making any physical incisions. This iterative planning process ensures precise measurement of bone reductions or augmentations, guaranteeing that the final contours align not only with feminizing principles but also with the patient’s specific reconstructive needs. For example, customized cutting guides and drilling templates can be virtually designed and subsequently 3D printed, which are then used intraoperatively to execute the planned osteotomies with remarkable accuracy, thereby minimizing human error and enhancing surgical precision (Barnett et al., 2023; Dr. MFO, 2025a).

Beyond virtual planning, the emerging role of artificial intelligence (AI) in preoperative morphing offers further advancements. AI-based software, such as DeepSurface AI, can generate three-dimensional morphs of the patient’s face, which can then be adjusted in real-time to demonstrate potential surgical outcomes across various facial regions (Barnett et al., 2023). While still an evolving area requiring further research, this technology holds immense potential for aligning patient expectations with realistic surgical possibilities, fostering more effective communication between patient and surgeon regarding desired goals.

Moreover, intraoperative navigation systems further enhance precision during the actual surgery. These systems, often likened to a GPS for the surgeon, track the exact position of surgical instruments in real-time relative to the patient’s anatomy and the pre-planned virtual model. This continuous validation of instrument placement and bone repositioning ensures that the surgery adheres precisely to the virtual plan, even in complex cases with distorted or atypical anatomy. The amalgamation of advanced imaging, virtual surgical planning, and intraoperative navigation systems not only significantly improves the accuracy, safety, and efficiency of facial feminization surgery but also substantially enhances the predictability of outcomes, ultimately leading to higher patient satisfaction and profoundly natural-looking results.

Intraoperative Considerations and Challenges in Complex Feminization Procedures

The execution of complex facial feminization surgery, particularly for patients with significant skeletal variations or previous interventions, presents a unique and demanding set of intraoperative considerations and challenges. These circumstances require not only exceptional surgical skill but also considerable adaptability and a deep understanding of anatomical variations. Unlike more routine aesthetic procedures, these cases often involve highly altered or atypical anatomy, which can obscure normal surgical landmarks and significantly increase the complexity of dissection and bone manipulation. The surgeon must be prepared to navigate unexpected findings and adjust the pre-planned strategy in real-time while maintaining the overarching feminization goals.

One of the most critical challenges lies in the meticulous management and preservation of vital neurovascular structures. The facial nerve and its numerous delicate branches, which control facial expressions, are particularly vulnerable during extensive soft tissue dissection and bone reshaping in regions like the midface and jawline. Similarly, branches of the trigeminal nerve, responsible for sensation, can be at risk, potentially leading to temporary or permanent numbness or altered sensation. Precise knowledge of anatomical variations in nerve pathways, which can occur as highlighted by Alraddadi (2021), coupled with meticulous surgical technique, is crucial to preserve nerve function and minimize the risks of facial paralysis or sensory deficits. The judicious use of intraoperative nerve monitoring can serve as an invaluable tool, providing real-time feedback to help identify and protect these delicate structures during complex dissections.

Vascular concerns are also heightened in reconstructive and extensive feminization cases. Tissues that have been scarred from previous surgeries or subjected to trauma may have a compromised blood supply, increasing the risk of flap necrosis, delayed wound healing, or excessive intraoperative bleeding. Careful, controlled dissection, gentle tissue handling, and meticulous hemostasis are paramount to preserve the delicate vascular network. When large bone grafts are utilized, ensuring adequate vascularity of the recipient bed is absolutely critical for graft survival and successful integration. In situations with severely compromised blood supply, specialized techniques such as vascularized bone grafts, where a segment of bone is transplanted along with its nourishing artery and vein and reconnected using microsurgical techniques, may be required. This represents the pinnacle of reconstructive artistry but also significantly increases operative time and technical demands (Dr. MFO, 2025a).

Managing inherent anatomical variations is another significant hurdle. As Alraddadi (2021) emphasizes, anatomical variations are normal presentations but can greatly influence clinical practice outcomes. No two cases of facial skeletal deficiency or dimorphism are identical, requiring surgeons to adapt their techniques dynamically to the unique presentation. While advanced virtual surgical planning provides a robust roadmap, the reality of the operating field can still present unforeseen anatomical deviations. This necessitates a surgeon with extensive experience in craniofacial and reconstructive surgery who can make informed, rapid decisions, potentially deviating from the initial plan if necessary, without compromising safety or aesthetic objectives. Factors such as unexpected bone density, the presence of fibrous scar tissue, or unusual sinus anatomy can all influence the precise execution of osteotomies and the stability of plate fixation strategies. Furthermore, achieving precise symmetry and harmonious contours in a face that may already be distorted requires continuous intraoperative assessment, often involving repeated visual inspection and palpation to ensure that bone reductions, advancements, or augmentations are balanced and aligned with the feminizing goals. The sheer volume and intricacy of combined bone and soft tissue work can lead to prolonged operative times, which in turn increases the risks associated with general anesthesia and overall patient recovery. Therefore, a highly coordinated surgical team, efficient instrumentation, and judicious patient selection based on a thorough preoperative assessment are essential prerequisites for successfully navigating these intraoperative complexities and achieving optimal, safe, and transformative results.

Post-Operative Recovery and Long-Term Management: Nurturing the Transformation

The post-operative phase following comprehensive facial feminization surgery, particularly when complex bone and soft tissue modifications have been performed, is a critical period that demands meticulous care, patience, and a well-structured management plan. The recovery timeline for extensive procedures is typically more protracted and can be more intense compared to standard aesthetic interventions, given the significant degree of bone manipulation, tissue reshaping, and potential for extensive swelling and bruising. Patients must be thoroughly prepared for this journey, understanding that the immediate post-operative appearance will evolve considerably over weeks and months.

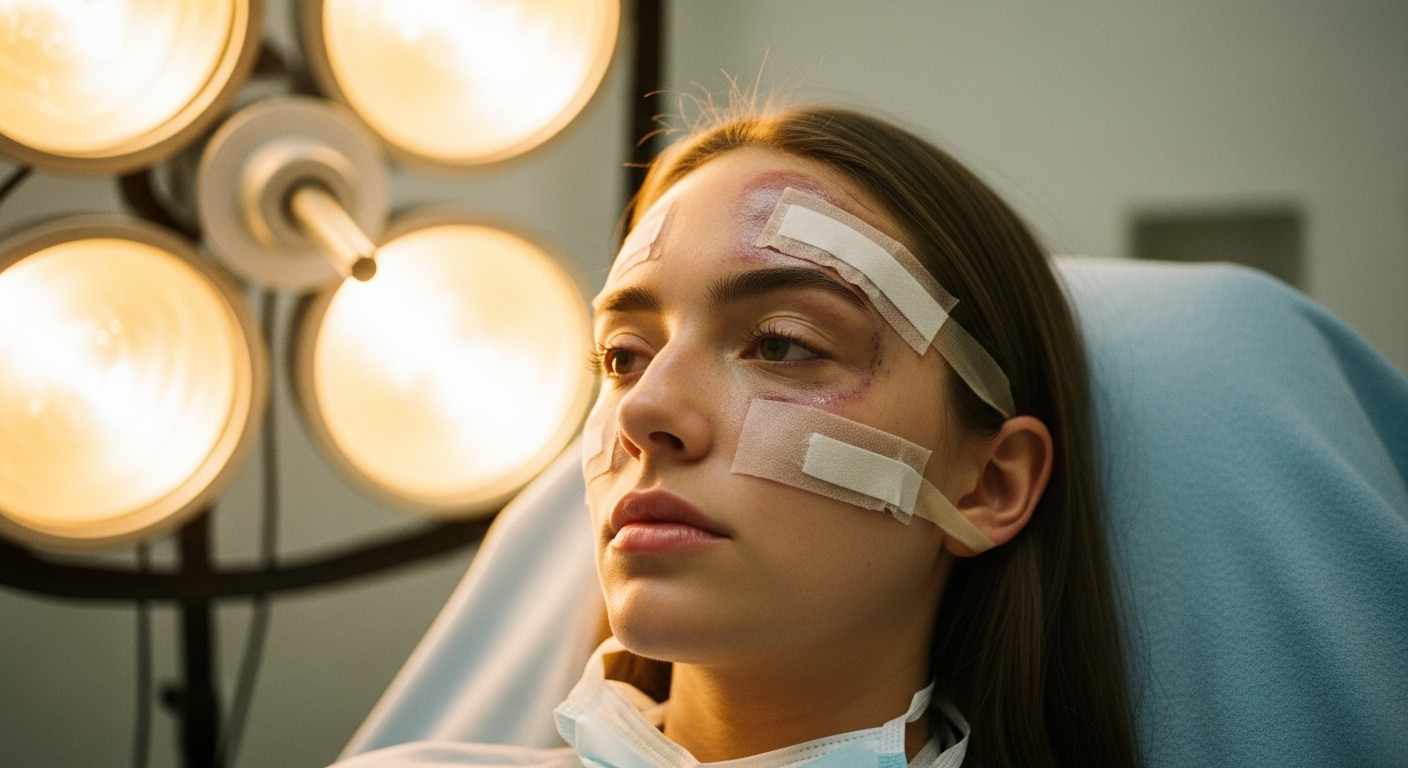
Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort. Swelling is an almost universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week after surgery, gradually subsiding over several weeks to months. Full resolution of residual swelling, especially in areas of significant bone work or grafting, can take up to a year or even longer for the final contours to fully emerge. Bruising will similarly resolve, usually within 2 to 4 weeks, with color changes from purplish-black to greenish-yellow before fading completely. Pain management is crucial and is typically achieved through a combination of prescribed analgesia, anti-inflammatory medications, and diligent application of cold compresses, which help to minimize swelling and alleviate discomfort. Hospitalization may extend for several days, particularly after complex osteotomies or large graft placements, allowing for close monitoring of vital signs, early detection of potential complications such as hematoma or infection, and effective pain control.

Specific post-operative care instructions are tailored to the procedures performed. For individuals undergoing jaw or chin osteotomies, a soft or liquid diet is often prescribed for several weeks to prevent undue stress on the healing bone segments and intraoral incisions. Meticulous oral hygiene, often involving antimicrobial mouth rinses, is paramount to prevent infection in the oral cavity. Activity restrictions are stringent in the initial weeks; patients are advised to avoid strenuous activities, heavy lifting, and anything that might elevate blood pressure or stress the healing facial structures. Gradually, activity levels are increased as recovery progresses and clearance is given by the surgical team. Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce swelling. Physical therapy or gentle lymphatic drainage massages may also be recommended in later stages of recovery to help expedite the resolution of swelling and improve soft tissue suppleness (Dr. MFO, 2025a).

Complex reconstructive procedures inherently carry potential complications beyond those of standard aesthetic surgery. While surgeons employ meticulous techniques to mitigate these, awareness and diligent monitoring are essential. Graft resorption, where a portion of transplanted autologous bone may be reabsorbed by the body, can lead to a partial loss of contour or volume, occasionally necessitating revision. For alloplastic implants, potential risks include implant exposure or infection, which can compromise implant integration and in severe cases require removal. Non-union or malunion of osteotomies, though rare, can occur if bone segments fail to heal properly, potentially leading to persistent asymmetry or functional issues, often requiring further surgical correction. Nerve damage, despite careful intraoperative preservation efforts, can manifest post-operatively as persistent numbness, altered sensation, or, in rare instances, motor weakness, particularly affecting facial expressions. Long-term stability expectations are a crucial aspect of patient counseling. While the extensive bone reshaping in feminization surgery provides a stable and lasting foundation, facial structures continue to undergo natural aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. Regular follow-up appointments are therefore essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction. A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey.

Functional and Aesthetic Restoration: Comprehensive Outcomes Beyond Appearance

The overarching goal of advanced facial feminization surgery, particularly when addressing severe facial skeletal deficiencies stemming from congenital anomalies, trauma, or complex developmental variations, extends far beyond mere aesthetic transformation. While the visual alignment of external features with an individual’s gender identity is paramount, equally significant is the comprehensive restoration of optimal facial function. For patients presenting with pre-existing functional impairments, the journey through feminization surgery offers a profound opportunity to simultaneously regain or improve vital physiological capabilities, thereby enhancing their overall quality of life and facilitating more seamless social interaction.

Functional impairments in such complex cases can be diverse and significantly impact daily life. These may include difficulties with mastication (chewing) due to severe jaw misalignment or temporomandibular joint (TMJ) dysfunction, which can be addressed through precise mandibular and maxillary osteotomies that not only feminize the jawline but also restore proper dental occlusion. Compromised vision or ocular discomfort arising from orbital dystopia (misplaced eyes) or malposition of the infraorbital rim can be alleviated through meticulous reconstruction of the orbital region, providing better support and protection for the eyes. Impaired breathing, often a consequence of severe nasal obstruction, septal deviation, or midface hypoplasia, can be corrected through comprehensive rhinoplasty that improves nasal airflow while simultaneously creating a more delicate nasal appearance (Barnett et al., 2023). Speech impediments, occasionally arising from abnormal oral or pharyngeal anatomy related to skeletal discrepancies, can also see improvements following corrective osseous surgery in the jaw and midface.

Therefore, a truly successful facial feminization outcome in these advanced cases is defined by the synergistic achievement of both highly feminine aesthetics and robust, enduring functional recovery. The intricate bone work, encompassing complex osteotomies, the strategic use of autologous bone grafts, and custom implant placements, plays a direct and foundational role in re-establishing proper skeletal support for these critical facial structures. For instance, correcting mandibular discrepancies not only sculpts a softer, more tapered jawline but critically restores proper dental occlusion and chewing efficiency, enabling better nutrition and comfort. Reconstructing the orbital rims and midface enhances visual field and provides improved protection for the eyes, while thoughtful rhinoplasty, beyond creating a more delicate nasal appearance, actively improves nasal airflow and respiratory function (Barnett et al., 2023). The integration of precise soft tissue management techniques further refines both outcomes. Accurate redraping of the skin, muscle, and fat over the newly contoured skeletal framework ensures natural-looking transitions and minimizes visible surgical evidence, contributing to a harmonious appearance that moves naturally with expression. Autologous fat grafting, beyond its aesthetic benefits of adding feminine volume to areas like the cheeks and lips, can also significantly improve local tissue quality, camouflage minor irregularities, and potentially enhance vascularity, further contributing to durable functional and aesthetic integration.

The meticulous preoperative planning involved, utilizing high-resolution 3D virtual surgical planning and intraoperative navigation, contributes profoundly to achieving this dual objective. By precisely defining bone movements, predicting soft tissue redraping, and mapping graft placements, surgeons can optimize both the feminizing aesthetic and the structural integrity necessary for restored function. Patient-reported outcome measures consistently demonstrate that individuals undergoing comprehensive facial feminization experience significant psychological benefits, including a profound reduction in gender dysphoria, improved self-esteem, and enhanced body image (Barnett et al., 2023). However, in reconstructive cases, these psychological gains are often compounded by the transformative impact of regaining lost or never-had functions, which further enhances overall quality of life, fosters greater independence, and facilitates more confident integration into society. The remarkable ability of modern reconstructive feminization surgery to simultaneously sculpt a face that is aesthetically feminine and fully functional represents the pinnacle of contemporary craniofacial and gender-affirming surgical practice, offering truly life-changing results for those facing the most profound anatomical challenges.

Selecting a Specialist: The Critical Choice for Complex Feminization

The decision to undergo advanced reconstructive facial feminization surgery for severe facial skeletal deficiencies is one of monumental significance. It necessitates the selection of a highly specialized and exceptionally experienced surgeon. The inherent complexity of these cases demands a level of expertise that extends far beyond the scope of a general plastic surgeon. It even surpasses that of one whose practice is solely focused on aesthetic feminization. Therefore, the paramount importance of choosing a surgeon with dual proficiency, deeply rooted in both routine facial feminization procedures and intricate maxillofacial reconstruction, cannot be overstated. Such a specialist possesses an unparalleled understanding of complex craniofacial anatomy, the biomechanics of bone remodeling and healing, and advanced reconstructive techniques. This includes microvascular surgery when vascularized grafts are indicated for compromised tissues (Dr. MFO, 2025a).

These highly specialized surgeons are adept at managing large skeletal defects. They correct severe congenital or acquired asymmetries. They also precisely reconstruct compromised facial units. Crucially, this dual expertise means the surgeon not only understands how to create aesthetically pleasing feminine contours. They also possess the foundational knowledge and technical skill to rebuild a stable and functional facial framework from a significantly compromised or deficient starting point. This includes profound proficiency in performing complex osteotomies with precision. It involves implementing advanced bone grafting techniques using either autologous tissue or customized alloplastic materials. It also includes the expert deployment of custom implants to restore lost volume and projection. Their training often encompasses a blend of plastic surgery, oral and maxillofacial surgery, and dedicated craniofacial fellowship training. This provides a robust skill set for the most challenging anatomical situations.

Furthermore, an ideal reconstructive feminization surgeon will be exceptionally well-versed in utilizing cutting-edge technologies that enhance precision and safety. This includes a mastery of high-resolution 3D virtual surgical planning (VSP) systems. It also encompasses the ability to design and utilize custom surgical guides and drilling templates. Proficiency with intraoperative navigation systems is also vital (Barnett et al., 2023; Dr. MFO, 2025a). Their capacity to leverage these advanced tools ensures optimal surgical accuracy. It minimizes potential risks and maximizes the predictability of outcomes. This is particularly true in scenarios characterized by distorted or atypical anatomy. Beyond technical skill, the most effective specialist will demonstrate a profoundly patient-centered approach. This involves engaging in thorough and empathetic consultations to fully understand the individual’s unique goals, specific concerns, and psychological needs. They are committed to providing realistic expectations regarding the surgical process, the nuances of recovery, and the potential long-term outcomes. This is especially vital given the inherent complexities and extended recovery periods of reconstructive cases. Verifying the surgeon’s credentials, including board certification in relevant surgical specialties and a comprehensive portfolio demonstrating successful outcomes in challenging reconstructive cases, is an essential step for prospective patients. Consulting with a surgeon who works within or collaborates with a multidisciplinary team, potentially including oral surgeons, orthodontists, and mental health professionals, further ensures a holistic and comprehensive approach to care. This addresses all facets of the patient’s well-being. Ultimately, the selection of such a highly experienced and uniquely qualified surgeon is the single most critical factor in achieving safe, functional, aesthetically transformative, and enduring results in advanced reconstructive facial feminization surgery. It provides patients with the confidence that their complex needs are in expert hands.

A woman with red hair is looking at the camera with a slight smile while sitting in front of a ring light.

Conclusion: The Critical Role of Individualized Anatomical Strategy

The journey through facial feminization surgery is a profoundly personal and meticulously orchestrated process. It is uniquely shaped by each individual’s distinct facial anatomy. As this comprehensive exploration has underscored, achieving natural, harmonious, and enduring results in feminization requires far more than a generalized approach. It demands an intricate understanding of the subtle and overt differences in skeletal and soft tissue structures that define facial gender. The ability to precisely assess, plan, and execute surgical modifications based on a patient’s unique biological blueprint is the hallmark of truly transformative and successful outcomes. We have delved into how variations in the frontal bone and orbital rims dictate specific forehead contouring techniques. We have also explored how midface projection influences strategies for cheek augmentation or reduction. Furthermore, we examined how the intricate cartilaginous and bony framework of the nose guides delicate rhinoplasty procedures. Similarly, the diverse forms of the mandible and chin necessitate highly individualized jawline and chin reshaping, while the laryngeal prominence requires careful reduction. Each of these regional modifications, when viewed in isolation, contributes to feminization. However, their true power emerges from their synergistic integration.

The advancements in preoperative planning, particularly the integration of high-resolution 3D imaging and virtual surgical planning systems, have revolutionized the field. They allow surgeons to create highly detailed blueprints of the desired transformation. This technological synergy enhances precision, minimizes risks, and optimizes predictability. It transitions complex cases from challenging guesswork to precisely engineered solutions. Intraoperative challenges, such as the meticulous preservation of neurovascular structures and the dynamic adaptation to anatomical variations, underscore the demanding nature of these procedures. These challenges also highlight the critical role of profound surgical experience. Furthermore, the post-operative recovery, often protracted and intensive, requires a comprehensive and patient-centered management plan to ensure optimal healing and long-term stability. Beyond the aesthetic alterations, successful facial feminization inherently encompasses the restoration or improvement of vital facial functions. This addresses potential impairments related to mastication, vision, and breathing. This dual emphasis on form and function ensures that the patient not only achieves an external appearance congruent with their identity but also experiences a significant enhancement in overall quality of life.

The selection of a highly specialized surgeon, one possessing deep expertise in both facial feminization and complex maxillofacial reconstruction, stands as the single most critical decision for individuals embarking on this journey. Their unique skill set, combining artistic vision with a profound anatomical understanding, is indispensable for navigating the intricacies of advanced cases and delivering results that are both safe and aesthetically profound. Ultimately, facial feminization surgery, particularly when tailored to the individual’s unique anatomy, is a powerful affirmation of identity. It fosters self-confidence and provides a deeper sense of authenticity. It is a testament to the continuous evolution of surgical science and artistry. It offers life-changing possibilities for those seeking harmony between their inner self and outer presentation. The ongoing commitment to precision, personalized care, and comprehensive outcomes will continue to define this vital and transformative field, providing hope and tangible results for countless individuals.

For those considering this transformative path, seeking consultation with a highly experienced and board-certified specialist is the essential first step. An initial discussion allows for a thorough assessment of individual needs, a detailed exploration of surgical options, and the collaborative development of a personalized treatment plan. This ensures that every aspect, from the initial consultation to long-term follow-up, is tailored to achieve the most harmonious, functional, and authentically feminine facial appearance possible.

Frequently Asked Questions

Why is individual facial anatomy so important in planning facial feminization surgery?

Individual facial anatomy is crucial because every face is unique, with varying bone structures and soft tissue distributions. A personalized surgical strategy, tailored to these specific anatomical nuances, ensures the most natural, harmonious, and effective feminization outcomes, as opposed to a generic approach.

What role do 3D imaging and virtual surgical planning play in customizing facial feminization procedures?

3D imaging, such as CT scans, provides a detailed blueprint of the patient’s skeletal and soft tissue architecture. Virtual surgical planning software allows surgeons to simulate procedures, precisely measure modifications, and design custom guides, significantly enhancing surgical precision, safety, and predictability.

How do bone modifications and soft tissue procedures interact synergistically in facial feminization?

Bone modifications (e.g., forehead contouring, jaw reduction) provide the foundational changes, redefining the facial framework. Soft tissue procedures (e.g., rhinoplasty, cheek augmentation, lip lifts) then refine these contours, add volume, and enhance expressions. Their synergistic combination ensures a cohesive, balanced, and naturally feminine appearance.

What are some of the critical challenges faced during complex facial feminization surgeries?

Challenges include meticulous preservation of vital neurovascular structures (like facial nerves), managing compromised blood supply in scarred tissues, adapting to unexpected anatomical variations, and ensuring precise symmetry. These demand exceptional surgical skill and adaptability.

What kind of recovery can be expected after extensive facial feminization surgery?

Recovery from extensive procedures typically involves significant swelling, bruising, and discomfort, which gradually subside over weeks to months. Full resolution of swelling and bone healing can take up to a year or more. Adherence to post-operative care, including rest, head elevation, and a soft diet, is crucial.

Beyond aesthetics, what other benefits does facial feminization surgery offer?

Beyond aesthetic alignment, facial feminization surgery can significantly improve or restore vital facial functions such as mastication (chewing), vision, and breathing, especially in cases of pre-existing skeletal deficiencies. This dual focus enhances overall quality of life, reduces psychological distress, and fosters greater social confidence.

What qualifications should one look for in a surgeon for complex facial feminization?

For complex cases, seek a surgeon with dual proficiency in both routine facial feminization and intricate maxillofacial reconstruction. This specialist should have extensive experience, board certification in relevant specialties, a strong portfolio of results, and expertise in advanced technologies like 3D virtual surgical planning.

Bibliography

Integrated FFS: Master Surgical Planning for 7 Seamless Multi-Procedure Outcomes

A young woman with a bright smile, looking away from the camera, standing indoors near a window.

Facial Feminization Surgery (FFS) represents a deeply intricate and profoundly personal journey, offering a transformative pathway for individuals seeking to align their external appearance with their affirmed feminine identity. This highly specialized field within craniofacial and plastic surgery transcends mere aesthetic enhancements, demanding a meticulous, individualized approach that acknowledges the profound and inherent variations in human facial anatomy. The fundamental principle guiding successful facial feminization is the understanding that no two faces are identical, nor do they present the same set of masculine characteristics to be addressed. Therefore, a “one-size-fits-all” methodology is inherently inadequate for achieving optimal, natural-looking, and deeply satisfying results. Instead, the process necessitates a bespoke surgical strategy meticulously tailored to each patient’s unique underlying skeletal and soft tissue architecture, which is a complex interplay of genetic predisposition, developmental factors, and the effects of hormonal influences.

This comprehensive guide will delve into the critical role of distinctive facial anatomy in shaping the precise surgical interventions and techniques employed during FFS, underscoring how a nuanced appreciation of individual features culminates in a truly personalized and effective transformation. We will explore how expert surgeons navigate the complex landscape of craniofacial differences between sexes, which range from the subtle contours of the brow to the more pronounced angles of the jaw, and how these anatomical nuances directly inform the selection and execution of feminizing procedures. The objective is not merely to soften overtly masculine traits but to sculpt a cohesive and balanced facial appearance that authentically reflects the individual’s gender identity, thereby enhancing psychological well-being, alleviating gender dysphoria, and facilitating social affirmation (Barnett et al., 2023).

This exploration will highlight the advanced diagnostic tools, such as high-resolution 3D imaging and sophisticated virtual surgical planning systems, that empower surgeons to create a detailed, three-dimensional blueprint of the patient’s face. This technological integration enables an unprecedented level of precision in preoperative strategizing, allowing for simulated outcomes and customized surgical guides. Furthermore, we will examine how various surgical techniques, encompassing both osseous (bone) modifications—which address the fundamental framework of the face—and soft tissue refinements—which provide the delicate finishing touches—are synergistically integrated to produce a harmonious outcome that maintains naturalness while achieving profound feminization.

The discussion will extend to the critical considerations involved in managing patient expectations, ensuring they are grounded in surgical realism, and understanding the unique challenges posed by significant anatomical variations. We will also emphasize the paramount importance of selecting a highly experienced specialist who possesses a deep understanding of both aesthetic principles and complex craniofacial reconstruction. Ultimately, this detailed analysis aims to illuminate the profound interplay between individual facial anatomy and surgical artistry, revealing how a deeply personalized approach is not just beneficial, but absolutely the cornerstone of transformative, durable, and profoundly impactful facial feminization outcomes.

A close-up portrait of a young woman with long brown hair, looking directly at the camera with a soft expression. The image is taken during sunset, casting a warm golden light on her face.

Understanding the Blueprint: Foundational Anatomy for Facial Feminization

Before any surgical intervention commences, a profound understanding of the patient’s foundational facial anatomy is paramount. A skilled facial feminization surgeon meticulously assesses the intricate interplay of underlying bone and overlying soft tissue structures. This comprehensive evaluation is critical because inherent differences in skeletal proportions and soft tissue distribution are key determinants of perceived gender.

Typically, masculine facial features often involve a more prominent brow ridge, a broader and squarer jawline, a larger and more anteriorly projected chin, and a distinct nasal profile characterized by a higher bridge and less upward rotation of the tip. However, the degree of expression of these features varies significantly among individuals due to genetic, ethnic, and developmental factors (Alraddadi, 2021). Recognizing these individual anatomical nuances is not merely an observational step but the foundational prerequisite for crafting a truly tailored and effective surgical plan.

To acquire this detailed anatomical blueprint, advanced diagnostic imaging plays an indispensable role. Three-dimensional computed tomography (3D CT) scans are frequently employed, providing a high-resolution, three-dimensional reconstruction of the patient’s unique skeletal and soft tissue architecture. These scans offer an unparalleled view of bone density, sinus pneumatization, nerve pathways, and the precise contours of the facial skeleton (Barnett et al., 2023). This data is then utilized in conjunction with virtual surgical planning (VSP) software, allowing surgeons to precisely measure existing structures and simulate potential surgical modifications.

Beyond static images, dynamic assessments of soft tissue mobility, skin elasticity, and muscle activity are also incorporated. Understanding the variations in tissue thickness and elasticity, for instance, is crucial for anticipating how overlying soft tissues will redrape following bone reductions or augmentations. The combination of comprehensive physical examination and advanced imaging provides the surgeon with a holistic understanding of the patient’s facial landscape, enabling them to formulate a feminization strategy that is both anatomically sound and aesthetically harmonious, moving beyond generic ideals to achieve results that are authentic to the individual.

A young woman with a nose piercing smiling warmly at sunset, with the sun casting a golden glow behind her.

Regional Deep Dive: Anatomical Impact on Specific Feminization Techniques

The Forehead and Orbital Rims: Sculpting a Feminine Foundation

The upper third of the face, comprising the forehead and orbital rims, is a primary region for gender recognition. Variations in the frontal bone and supraorbital ridge (brow bone) are among the most significant sexually dimorphic features. Masculine foreheads often present with a prominent brow bossing, a heavier and more horizontally positioned brow relative to the superior orbital rim, and a forehead that recedes backward. In stark contrast, feminine foreheads are typically characterized by a smoother, rounder contour, a more vertically oriented profile, and eyebrows that arch higher, positioned above the orbital rim (Barnett et al., 2023). The degree of frontal bossing can vary considerably among individuals, directly impacting the complexity and choice of surgical intervention.

These anatomical variations directly influence the selection of forehead contouring procedures, primarily categorized into Type 1 (shaving), Type 2 (combination), or Type 3 (setback) techniques. For individuals with a relatively thick anterior frontal sinus wall and less pronounced bossing, a Type 1 procedure, involving direct burring or shaving of the prominent bone, may suffice to create a smoother transition. However, when the frontal sinus bone is thinner or the brow bossing is significantly prominent, a more extensive approach is often necessitated.

A Type 3 cranioplasty, also known as frontal sinus setback, involves carefully removing the anterior wall of the frontal sinus, meticulously reshaping it, and then reattaching it in a more recessed and feminized position (Barnett et al., 2023). This reconstructive technique allows for a greater degree of reduction and a more profound feminizing effect, fundamentally altering the supraorbital contour and achieving the desired convex curvature of a feminine forehead.

In conjunction with forehead contouring, orbital rim contouring is frequently performed to further enhance upper facial feminization. In masculine faces, the bony edges around the eye sockets can appear heavier and more angular, often casting shadows that masculinize the eyes. By carefully smoothing and rounding these edges, the eyes appear larger, more open, and less shadowed, contributing to a softer, more inviting gaze. The precise execution of these modifications, especially near critical structures such as the supraorbital and supratrochlear nerves, is paramount to prevent sensory deficits.

Additionally, the natural hairline position and any existing brow descent will guide the selection of brow lift techniques. A coronal incision, extending across the scalp, may be chosen for significant hairline advancement combined with forehead contouring, whereas an endoscopic brow lift, utilizing smaller incisions within the hairline, can achieve brow elevation with minimal hairline change, particularly when hairline lowering is not a primary objective. Virtual surgical planning, as detailed by Barnett et al. (2023), has emerged as an indispensable tool, allowing surgeons to precisely visualize desired outcomes and plan osteotomies with enhanced accuracy, significantly reducing operative time and minimizing complications like over-resection or nerve injury. This meticulous pre-surgical mapping ensures that the altered contours integrate seamlessly with the rest of the face, providing a harmonious and distinctly feminine upper facial aesthetic.

A close-up portrait of a woman with a serious expression, illuminated by soft lighting against a dark background.

Midface and Cheeks: Sculpting Softness and Projection

The midface, prominently defined by the zygomatic (cheekbone) complex and the overlying soft tissues, plays a pivotal role in the perception of facial femininity and youthfulness. Significant variations exist in midface projection and contour between masculine and feminine physiognomies. Masculine midfaces often exhibit flatter zygomas with less anterior projection, contributing to a less triangulated facial shape. In contrast, feminine cheeks are typically characterized by higher, more anteriorly positioned zygomatic arches, creating a desirable convexity and contributing to a softer, more youthful, and often “heart-shaped” facial contour (Barnett et al., 2023). The distribution and volume of subcutaneous fat, including the malar fat pad and buccal fat, also vary considerably, further influencing overall midface appearance.

Surgical strategies for midface feminization are highly individualized, contingent upon the patient’s existing anatomical structure and desired aesthetic. When there is insufficient malar projection or a naturally flatter midface, cheek augmentation is often recommended. This can be achieved through various methods. Autologous fat grafting, which involves harvesting fat from other areas of the patient’s body (e.g., abdomen or thighs) via liposuction, processing it, and then injecting it into the cheeks, offers a natural solution. This technique provides a soft, natural-looking augmentation and can simultaneously improve the quality of the overlying skin. Alternatively, custom alloplastic implants, typically made of biocompatible materials such as silicone, can be placed over the cheekbones to provide permanent volume and definition. These implants are either pre-designed or custom-fabricated based on 3D virtual surgical planning to precisely match the desired contours (Barnett et al., 2023).

Conversely, in rare instances where cheekbones are excessively wide or prominently angled in a masculine manner, a surgeon might consider zygomatic arch reduction to soften the midface width. Furthermore, the distribution of buccal fat—a deep fat pad located within the cheek—can impact facial fullness. For individuals with a fuller, rounder lower face that detracts from a feminine aesthetic, buccal fat pad removal may be considered to create a more defined and hollowed submalar region, enhancing the appearance of higher cheekbones.

The delicate interplay between these procedures allows for the creation of an “ogee curve”—a graceful, double S-curve contour from the temple to the cheek, which is highly indicative of youthful, feminine cheeks. When combining nose and cheek procedures, as highlighted by Dr. MFO (2025b), synergistic anatomical planning is critical due to the interdependence of nasal and midface aesthetics. An overly prominent nose, for example, can make the midface appear recessed, while well-projected cheekbones can visually balance a nose. Therefore, modifications in one area profoundly influence the perception of the other, requiring an integrated approach to achieve overall facial harmony.

The Nose: Achieving Delicate Proportions

The nose, positioned centrally on the face, is a critical feature that significantly influences overall facial balance and perceived gender. Nasal structures exhibit immense diversity, yet distinct patterns contribute to gender recognition. Masculine noses often feature a broader nasal bridge, a more prominent dorsal hump, wider nostrils (alar base), and a less upwardly rotated, sometimes even downwardly projecting, nasal tip. In contrast, feminine noses are typically characterized by a smaller overall size, a narrower bridge, a softer or slightly concave dorsal profile, and a more refined, slightly upturned nasal tip, contributing to a more obtuse nasolabial angle (Barnett et al., 2023).

This wide spectrum of nasal anatomy necessitates a comprehensive range of rhinoplasty techniques during facial feminization. Dorsal hump reduction is a common procedure, involving the careful removal or rasping of excess bone and cartilage along the nasal bridge to create a smoother, more delicate profile. Concurrently, narrowing the nasal bones through osteotomies (controlled bone cuts) helps to reduce the overall width of the nasal bridge, contributing to a more refined appearance. Tip plasty techniques are pivotal for feminizing the nasal tip; these involve meticulous reshaping of the lower lateral cartilages through excisions, sutures, and grafts to make the tip smaller, more defined, and appropriately rotated upward (Barnett et al., 2023). Alar base reduction may be performed to narrow excessively wide nostrils, which can be a masculine characteristic, ensuring the nasal base is proportionate to the feminized tip and bridge. The specific aims are to create a nose that harmonizes with the newly contoured forehead and midface, avoiding an overly aggressive or artificial appearance.

An open rhinoplasty approach, utilizing a small incision across the columella and internal incisions, is often favored in facial feminization due to the optimal access and visibility it provides to the underlying skeletal and cartilaginous framework. This allows the surgeon to precisely manipulate structures and address specific feminizing goals, such as caudal septal trimming for upward tip rotation (Barnett et al., 2023). The intricate relationship between the bony and cartilaginous components of the nose demands a highly skilled surgeon to achieve stable and aesthetically pleasing results.

Furthermore, the soft tissue envelope, comprising skin, subcutaneous fat, and muscle, plays a significant role in the final outcome; its thickness and elasticity determine how readily underlying changes will be revealed. Consideration of the nasal vascular supply, primarily from branches of the ophthalmic and facial arteries, and innervation from the trigeminal nerve, is crucial to minimize complications such as bleeding or sensory changes. The ultimate goal is to sculpt a nose that is in harmonious proportion with the overall feminized facial features, enhancing the patient’s self-perception and social comfort (Dr. MFO, 2025c).

Jawline and Chin: Softening the Lower Face

The lower third of the face, particularly the jawline and chin, are primary indicators of sexual dimorphism and significantly contribute to perceived gender. Masculine jawlines are typically broader, squarer, and more angular, often presenting with prominent mandibular angles and a thicker external oblique ridge. The chin in masculine faces can be wider, squarer, or excessively prominent, contributing to a strong, sometimes blunt, lower facial appearance. Conversely, feminine jawlines are generally narrower, more tapered, and often exhibit a graceful V-shape or oval contour with softer angles. The chin in feminine faces is typically more delicate, with less width and projection, contributing to a refined lower facial profile (Barnett et al., 2023).

Surgical strategies for feminizing the jawline and chin involve meticulously tailored osseous modifications. Mandibular angle reduction is a key procedure designed to soften the posterior jawline. This involves carefully shaving or resecting a portion of the bone at the prominent jaw angles, transforming a square contour into a smoother, more tapered transition from the ear to the chin. This procedure is often performed through intraoral incisions (inside the mouth) to avoid visible external scarring, allowing for precise osteotomy and contouring while mitigating damage to vital structures such as the inferior alveolar nerve (Barnett et al., 2023).

Chin reshaping, or genioplasty, addresses the size, projection, and shape of the chin. In facial feminization, the goal is often to reduce chin width, shorten its vertical height if it is excessively long, and/or reshape it to a more pointed or rounded form, depending on the patient’s desired outcome and existing anatomy. A common technique is the sliding genioplasty, where the chin bone is carefully cut horizontally, and the distal segment is repositioned. This segment can be moved backward for reduction, advanced for increased projection, vertically shortened, or narrowed to achieve the desired delicate, feminine contour. The repositioned bone segment is then secured with small plates and screws to ensure stability and predictable healing (Barnett et al., 2023).

For chins that primarily require reduction in width or projection without significant repositioning, direct bone shaving or burring can be performed. The integration of these procedures often culminates in a “V-line” surgery, which combines mandibular angle reduction and genioplasty to create a significantly more tapered and feminine lower facial silhouette. In some cases, masseter muscle reduction, either surgically or through botulinum toxin injections, may also be considered for individuals with hypertrophied (enlarged) jaw muscles contributing to excessive lower facial width. The combined effect of these carefully planned interventions results in a more graceful, harmonious, and distinctly feminine lower face, balancing the features modified in the upper and mid-face (Dr. MFO, 2025a).

The Trachea: A Smoother Neckline

The laryngeal prominence, commonly known as the Adam’s apple, is a distinct secondary sex characteristic that develops and becomes more prominent during male puberty due to the enlargement and acute angle of the thyroid cartilage. Its presence can be a significant source of gender dysphoria for many transgender women, as it is a highly visible feature immediately indicative of a masculine neck profile. A tracheal shave, also known as chondrolaryngoplasty, is a straightforward yet highly effective feminizing procedure specifically designed to reduce the size and prominence of the Adam’s apple (Barnett et al., 2023).

The procedure typically involves making a small, discreet transverse incision in a natural skin crease on the neck, often at the midpoint between the submental crease and the cervicomental angle, to minimize the visibility of any resulting scar. Through this incision, the surgeon carefully shaves down the most prominent part of the thyroid cartilage, reducing its projection and creating a smoother, softer contour of the neck. Extreme care is taken to preserve a rim of cartilage superior to the level of the vocal cords for stabilization and, crucially, to avoid damaging the vocal cords themselves, which are located just behind the cartilage (Barnett et al., 2023). This meticulous approach ensures that vocal function is preserved. While primarily a modification of cartilage, which is a form of skeletal tissue, the tracheal shave profoundly impacts the overall appearance of the neck and profile, contributing to a more feminine silhouette and alleviating a significant source of dysphoria.

The recovery from a tracheal shave is generally quicker than from more extensive bone procedures, with most acute swelling and discomfort subsiding within a few weeks. Patients may experience some temporary voice changes or a sensation of tightness immediately after the surgery, but these usually resolve as the healing progresses. In some cases, submental fat excision and platysmaplasty (neck muscle tightening) may be performed concurrently to further enhance the desired neck silhouette and achieve maximal skin tightening, especially in older patients where skin laxity is a greater concern (Barnett et al., 2023). For many individuals, achieving a smoother neckline provides immense psychological relief, allowing them to feel more comfortable and confident in their appearance, particularly when wearing clothing that exposes the neck. This relatively contained procedure offers a significant impact on overall gender affirmation by addressing one of the most visible masculine features of the head and neck region.

A young woman with long, straight dark hair, wearing a gray shirt, smiling and looking up towards the light coming through a window.

Integrating Techniques for Holistic Feminization: The Art of Synergy

True facial feminization rarely involves a singular procedure. Instead, it is an intricate symphony of coordinated surgical interventions, each meticulously planned to complement the others and holistically address the patient’s unique anatomy. The skilled surgeon acts as an architect, orchestrating a series of modifications—ranging from fundamental bone restructuring to subtle soft tissue refinements—to achieve a balanced, harmonious, and naturally feminine outcome. This integrated approach ensures that the overall result is cohesive and congruent with the patient’s gender identity, rather than a collection of isolated, disconnected changes. The synergy between procedures is paramount, as altering one facial component inevitably influences the perception and aesthetics of adjacent and distant features.

For instance, a reduction in brow bossing not only feminizes the forehead but also optically enlarges the eyes, making a subtle rhinoplasty’s impact even more pronounced. Similarly, jawline and chin reshaping procedures provide a narrower foundation, over which soft tissues drape more delicately, enhancing the effect of cheek augmentation and lip lifts. The thoughtful sequencing and combination of these techniques are what elevate facial feminization from mere surgical alteration to a sophisticated art form.

The decision for a comprehensive, single-stage facial feminization surgery versus a staged approach (multiple surgeries performed over time) is heavily influenced by the anatomical complexity of the case, the patient’s overall physical health, and personal preferences. While a single-stage procedure offers the convenience of one recovery period and often significant cost savings, patient safety remains the ultimate priority. Studies indicate that an increased number of procedures performed per anesthetic event in facial feminization patients does not necessarily predict higher complication rates, suggesting that well-planned, comprehensive single-stage approaches can be safely undertaken under appropriate medical judgment (Barnett et al., 2023).

However, for individuals with extensive surgical needs, significant medical comorbidities, or those who prefer to recover from smaller interventions sequentially, a staged approach may be more appropriate. In such cases, structural hard tissue procedures like frontal sinus setback, supraorbital contouring, jawline tapering, and rhinoplasty are often prioritized, followed by subsequent soft tissue procedures like facelifts, neck lifts, and blepharoplasty, particularly in older patients where skin laxity is a consideration (Barnett et al., 2023). This strategic sequencing ensures that the foundational skeletal changes are established before refining the overlying soft tissues, thereby optimizing both the aesthetic and functional outcomes. Regardless of the staging strategy, the overarching goal is to achieve seamless integration, where each surgical modification contributes harmoniously to the final feminine facial contour.

Preoperative Planning and Technological Advancements for Precision

The success of advanced facial feminization surgery, particularly in cases involving significant anatomical variations, hinges critically on comprehensive and precise preoperative planning. This crucial phase has undergone a profound revolution with the integration of cutting-edge imaging modalities and virtual technologies, offering an unprecedented level of accuracy and predictability. High-resolution imaging, such as Cone-Beam Computed Tomography (CBCT) and standard Computed Tomography (CT) scans, provides detailed three-dimensional anatomical data of the patient’s skull and overlying soft tissues (Barnett et al., 2023).

This granular data is absolutely essential for an accurate diagnosis of existing skeletal differences, including bone volume deficits, subtle asymmetries, malposition of facial segments, and a precise assessment of critical underlying structures such as nerve pathways and sinus cavities. The detailed understanding derived from these images forms the fundamental bedrock upon which the entire surgical strategy is built, allowing surgeons to meticulously map out the existing anatomy and pinpoint all areas requiring correction or augmentation.

Building upon this rich imaging data, three-dimensional virtual surgical planning (VSP) systems have become indispensable tools in contemporary facial feminization. VSP involves importing the patient’s CT or CBCT data into specialized software, where a precise 3D digital model of the face and skull is generated. Within this sophisticated virtual environment, surgeons can meticulously plan every osteotomy (bone cut), bone graft placement, and custom implant positioning. This digital platform allows for the simulation of various surgical scenarios, enabling surgeons to virtually adjust bone segment movements, refine contours, and visualize the potential aesthetic and functional outcomes before making any physical incisions. This iterative planning process ensures precise measurement of bone reductions or augmentations, guaranteeing that the final contours align not only with feminizing principles but also with the patient’s specific reconstructive needs. For example, customized cutting guides and drilling templates can be virtually designed and subsequently 3D printed, which are then used intraoperatively to execute the planned osteotomies with remarkable accuracy, thereby minimizing human error and enhancing surgical precision (Barnett et al., 2023).

Beyond virtual planning, the emerging role of artificial intelligence (AI) in preoperative morphing offers further advancements. AI-based software, such as DeepSurface AI, can generate three-dimensional morphs of the patient’s face, which can then be adjusted in real-time to demonstrate potential surgical outcomes across various facial regions (Barnett et al., 2023). While still an evolving area requiring further research, this technology holds immense potential for aligning patient expectations with realistic surgical possibilities, fostering more effective communication between patient and surgeon regarding desired goals.

Moreover, intraoperative navigation systems further enhance precision during the actual surgery. These systems, often likened to a GPS for the surgeon, track the exact position of surgical instruments in real-time relative to the patient’s anatomy and the pre-planned virtual model. This continuous validation of instrument placement and bone repositioning ensures that the surgery adheres precisely to the virtual plan, even in complex cases with distorted or atypical anatomy. The amalgamation of advanced imaging, virtual surgical planning, and intraoperative navigation systems not only significantly improves the accuracy, safety, and efficiency of facial feminization surgery but also substantially enhances the predictability of outcomes, ultimately leading to higher patient satisfaction and profoundly natural-looking results.

Intraoperative Considerations and Challenges in Complex Feminization Procedures

The execution of complex facial feminization surgery, particularly for patients with significant skeletal variations or previous interventions, presents a unique and demanding set of intraoperative considerations and challenges. These circumstances require not only exceptional surgical skill but also considerable adaptability and a deep understanding of anatomical variations. Unlike more routine aesthetic procedures, these cases often involve highly altered or atypical anatomy, which can obscure normal surgical landmarks and significantly increase the complexity of dissection and bone manipulation. The surgeon must be prepared to navigate unexpected findings and adjust the pre-planned strategy in real-time while maintaining the overarching feminization goals.

One of the most critical challenges lies in the meticulous management and preservation of vital neurovascular structures. The facial nerve and its numerous delicate branches, which control facial expressions, are particularly vulnerable during extensive soft tissue dissection and bone reshaping in regions like the midface and jawline. Similarly, branches of the trigeminal nerve, responsible for sensation, can be at risk, potentially leading to temporary or permanent numbness or altered sensation. Precise knowledge of anatomical variations in nerve pathways, which can occur as highlighted by Alraddadi (2021), coupled with meticulous surgical technique, is crucial to preserve nerve function and minimize the risks of facial paralysis or sensory deficits. The judicious use of intraoperative nerve monitoring can serve as an invaluable tool, providing real-time feedback to help identify and protect these delicate structures during complex dissections.

Vascular concerns are also heightened in reconstructive and extensive feminization cases. Tissues that have been scarred from previous surgeries or subjected to trauma may have a compromised blood supply, increasing the risk of flap necrosis, delayed wound healing, or excessive intraoperative bleeding. Careful, controlled dissection, gentle tissue handling, and meticulous hemostasis are paramount to preserve the delicate vascular network. When large bone grafts are utilized, ensuring adequate vascularity of the recipient bed is absolutely critical for graft survival and successful integration. In situations with severely compromised blood supply, specialized techniques such as vascularized bone grafts, where a segment of bone is transplanted along with its nourishing artery and vein and reconnected using microsurgical techniques, may be required. This represents the pinnacle of reconstructive artistry but also significantly increases operative time and technical demands.

Managing inherent anatomical variations is another significant hurdle. As Alraddadi (2021) emphasizes, anatomical variations are normal presentations but can greatly influence clinical practice outcomes. No two cases of facial skeletal deficiency or dimorphism are identical, requiring surgeons to adapt their techniques dynamically to the unique presentation. While advanced virtual surgical planning provides a robust roadmap, the reality of the operating field can still present unforeseen anatomical deviations. This necessitates a surgeon with extensive experience in craniofacial and reconstructive surgery who can make informed, rapid decisions, potentially deviating from the initial plan if necessary, without compromising safety or aesthetic objectives. Factors such as unexpected bone density, the presence of fibrous scar tissue, or unusual sinus anatomy can all influence the precise execution of osteotomies and the stability of plate fixation strategies. Furthermore, achieving precise symmetry and harmonious contours in a face that may already be distorted requires continuous intraoperative assessment, often involving repeated visual inspection and palpation to ensure that bone reductions, advancements, or augmentations are balanced and aligned with the feminizing goals. The sheer volume and intricacy of combined bone and soft tissue work can lead to prolonged operative times, which in turn increases the risks associated with general anesthesia and overall patient recovery. Therefore, a highly coordinated surgical team, efficient instrumentation, and judicious patient selection based on a thorough preoperative assessment are essential prerequisites for successfully navigating these intraoperative complexities and achieving optimal, safe, and transformative results.

Post-Operative Recovery and Long-Term Management: Nurturing the Transformation

The post-operative phase following comprehensive facial feminization surgery, particularly when complex bone and soft tissue modifications have been performed, is a critical period that demands meticulous care, patience, and a well-structured management plan. The recovery timeline for extensive procedures is typically more protracted and can be more intense compared to standard aesthetic interventions, given the significant degree of bone manipulation, tissue reshaping, and potential for extensive swelling and bruising. Patients must be thoroughly prepared for this journey, understanding that the immediate post-operative appearance will evolve considerably over weeks and months.

Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort. Swelling is an almost universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week after surgery, gradually subsiding over several weeks to months. Full resolution of residual swelling, especially in areas of significant bone work or grafting, can take up to a year or even longer for the final contours to fully emerge. Bruising will similarly resolve, usually within 2 to 4 weeks, with color changes from purplish-black to greenish-yellow before fading completely. Pain management is crucial and is typically achieved through a combination of prescribed analgesia, anti-inflammatory medications, and diligent application of cold compresses, which help to minimize swelling and alleviate discomfort. Hospitalization may extend for several days, particularly after complex osteotomies or large graft placements, allowing for close monitoring of vital signs, early detection of potential complications such as hematoma or infection, and effective pain control.

Specific post-operative care instructions are tailored to the procedures performed. For individuals undergoing jaw or chin osteotomies, a soft or liquid diet is often prescribed for several weeks to prevent undue stress on the healing bone segments and intraoral incisions. Meticulous oral hygiene, often involving antimicrobial mouth rinses, is paramount to prevent infection in the oral cavity. Activity restrictions are stringent in the initial weeks; patients are advised to avoid strenuous activities, heavy lifting, and anything that might elevate blood pressure or stress the healing facial structures. Gradually, activity levels are increased as recovery progresses and clearance is given by the surgical team. Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce swelling. Physical therapy or gentle lymphatic drainage massages may also be recommended in later stages of recovery to help expedite the resolution of swelling and improve soft tissue suppleness.

Complex reconstructive procedures inherently carry potential complications beyond those of standard aesthetic surgery. While surgeons employ meticulous techniques to mitigate these, awareness and diligent monitoring are essential. Graft resorption, where a portion of transplanted autologous bone may be reabsorbed by the body, can lead to a partial loss of contour or volume, occasionally necessitating revision. For alloplastic implants, potential risks include implant exposure or infection, which can compromise implant integration and in severe cases require removal. Non-union or malunion of osteotomies, though rare, can occur if bone segments fail to heal properly, potentially leading to persistent asymmetry or functional issues, often requiring further surgical correction. Nerve damage, despite careful intraoperative preservation efforts, can manifest post-operatively as persistent numbness, altered sensation, or, in rare instances, motor weakness, particularly affecting facial expressions. Long-term stability expectations are a crucial aspect of patient counseling. While the extensive bone reshaping in feminization surgery provides a stable and lasting foundation, facial structures continue to undergo natural aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. Regular follow-up appointments are therefore essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction. A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey.

Functional and Aesthetic Restoration: Comprehensive Outcomes Beyond Appearance

The overarching goal of advanced facial feminization surgery, particularly when addressing severe facial skeletal deficiencies stemming from congenital anomalies, trauma, or complex developmental variations, extends far beyond mere aesthetic transformation. While the visual alignment of external features with an individual’s gender identity is paramount, equally significant is the comprehensive restoration of optimal facial function. For patients presenting with pre-existing functional impairments, the journey through feminization surgery offers a profound opportunity to simultaneously regain or improve vital physiological capabilities, thereby enhancing their overall quality of life and facilitating more seamless social interaction.

Functional impairments in such complex cases can be diverse and significantly impact daily life. These may include difficulties with mastication (chewing) due to severe jaw misalignment or temporomandibular joint (TMJ) dysfunction, which can be addressed through precise mandibular and maxillary osteotomies that not only feminize the jawline but also restore proper dental occlusion. Compromised vision or ocular discomfort arising from orbital dystopia (misplaced eyes) or malposition of the infraorbital rim can be alleviated through meticulous reconstruction of the orbital region, providing better support and protection for the eyes. Impaired breathing, often a consequence of severe nasal obstruction, septal deviation, or midface hypoplasia, can be corrected through comprehensive rhinoplasty that improves nasal airflow while simultaneously creating a more delicate nasal appearance (Barnett et al., 2023). Speech impediments, occasionally arising from abnormal oral or pharyngeal anatomy related to skeletal discrepancies, can also see improvements following corrective osseous surgery in the jaw and midface.

Therefore, a truly successful facial feminization outcome in these advanced cases is defined by the synergistic achievement of both highly feminine aesthetics and robust, enduring functional recovery. The intricate bone work, encompassing complex osteotomies, the strategic use of autologous bone grafts, and custom implant placements, plays a direct and foundational role in re-establishing proper skeletal support for these critical facial structures. For instance, correcting mandibular discrepancies not only sculpts a softer, more tapered jawline but critically restores proper dental occlusion and chewing efficiency, enabling better nutrition and comfort. Reconstructing the orbital rims and midface enhances visual field and provides improved protection for the eyes, while thoughtful rhinoplasty, beyond creating a more delicate nasal appearance, actively improves nasal airflow and respiratory function (Barnett et al., 2023). The integration of precise soft tissue management techniques further refines both outcomes. Accurate redraping of the skin, muscle, and fat over the newly contoured skeletal framework ensures natural-looking transitions and minimizes visible surgical evidence, contributing to a harmonious appearance that moves naturally with expression. Autologous fat grafting, beyond its aesthetic benefits of adding feminine volume to areas like the cheeks and lips, can also significantly improve local tissue quality, camouflage minor irregularities, and potentially enhance vascularity, further contributing to durable functional and aesthetic integration.

The meticulous preoperative planning involved, utilizing high-resolution 3D virtual surgical planning and intraoperative navigation, contributes profoundly to achieving this dual objective. By precisely defining bone movements, predicting soft tissue redraping, and mapping graft placements, surgeons can optimize both the feminizing aesthetic and the structural integrity necessary for restored function. Patient-reported outcome measures consistently demonstrate that individuals undergoing comprehensive facial feminization experience significant psychological benefits, including a profound reduction in gender dysphoria, improved self-esteem, and enhanced body image (Barnett et al., 2023). However, in reconstructive cases, these psychological gains are often compounded by the transformative impact of regaining lost or never-had functions, which further enhances overall quality of life, fosters greater independence, and facilitates more confident integration into society. The remarkable ability of modern reconstructive feminization surgery to simultaneously sculpt a face that is aesthetically feminine and fully functional represents the pinnacle of contemporary craniofacial and gender-affirming surgical practice, offering truly life-changing results for those facing the most profound anatomical challenges.

Selecting a Specialist: The Critical Choice for Complex Feminization

The decision to undergo advanced reconstructive facial feminization surgery for severe facial skeletal deficiencies is one of monumental significance, necessitating the selection of a highly specialized and exceptionally experienced surgeon. The inherent complexity of these cases demands a level of expertise that extends far beyond the scope of a general plastic surgeon or even one whose practice is solely focused on aesthetic feminization. Therefore, the paramount importance of choosing a surgeon with dual proficiency—deeply rooted in both routine facial feminization procedures and intricate maxillofacial reconstruction—cannot be overstated. Such a specialist possesses an unparalleled understanding of complex craniofacial anatomy, the biomechanics of bone remodeling and healing, and advanced reconstructive techniques, including microvascular surgery when vascularized grafts are indicated for compromised tissues (Dr. MFO, 2025a).

These highly specialized surgeons are adept at managing large skeletal defects, correcting severe congenital or acquired asymmetries, and precisely reconstructing compromised facial units. Crucially, this dual expertise means the surgeon not only understands how to create aesthetically pleasing feminine contours but also possesses the foundational knowledge and technical skill to rebuild a stable and functional facial framework from a significantly compromised or deficient starting point. This includes profound proficiency in performing complex osteotomies with precision, implementing advanced bone grafting techniques using either autologous tissue or customized alloplastic materials, and the expert deployment of custom implants to restore lost volume and projection. Their training often encompasses a blend of plastic surgery, oral and maxillofacial surgery, and dedicated craniofacial fellowship training, providing a robust skill set for the most challenging anatomical situations.

Furthermore, an ideal reconstructive feminization surgeon will be exceptionally well-versed in utilizing cutting-edge technologies that enhance precision and safety. This includes a mastery of high-resolution 3D virtual surgical planning (VSP) systems, the ability to design and utilize custom surgical guides and drilling templates, and proficiency with intraoperative navigation systems (Barnett et al., 2023). Their capacity to leverage these advanced tools ensures optimal surgical accuracy, minimizes potential risks, and maximizes the predictability of outcomes, particularly in scenarios characterized by distorted or atypical anatomy. Beyond technical skill, the most effective specialist will demonstrate a profoundly patient-centered approach. This involves engaging in thorough and empathetic consultations to fully understand the individual’s unique goals, specific concerns, and psychological needs. They are committed to providing realistic expectations regarding the surgical process, the nuances of recovery, and the potential long-term outcomes, which is especially vital given the inherent complexities and extended recovery periods of reconstructive cases. Verifying the surgeon’s credentials, including board certification in relevant surgical specialties and a comprehensive portfolio demonstrating successful outcomes in challenging reconstructive cases, is an essential step for prospective patients. Consulting with a surgeon who works within or collaborates with a multidisciplinary team, potentially including oral surgeons, orthodontists, and mental health professionals, further ensures a holistic and comprehensive approach to care, addressing all facets of the patient’s well-being. Ultimately, the selection of such a highly experienced and uniquely qualified surgeon is the single most critical factor in achieving safe, functional, aesthetically transformative, and enduring results in advanced reconstructive facial feminization surgery, providing patients with the confidence that their complex needs are in expert hands.

A professional woman in a black blazer posing confidently in an office setting with a large window in the background.

Conclusion: The Critical Role of Individualized Anatomical Strategy

The journey through facial feminization surgery is a profoundly personal and meticulously orchestrated process, uniquely shaped by each individual’s distinct facial anatomy. As this comprehensive exploration has underscored, achieving natural, harmonious, and enduring results in feminization requires far more than a generalized approach; it demands an intricate understanding of the subtle and overt differences in skeletal and soft tissue structures that define facial gender. The ability to precisely assess, plan, and execute surgical modifications based on a patient’s unique biological blueprint is the hallmark of truly transformative and successful outcomes. We have delved into how variations in the frontal bone and orbital rims dictate specific forehead contouring techniques, how midface projection influences strategies for cheek augmentation or reduction, and how the intricate cartilaginous and bony framework of the nose guides delicate rhinoplasty procedures. Similarly, the diverse forms of the mandible and chin necessitate highly individualized jawline and chin reshaping, while the laryngeal prominence requires careful reduction. Each of these regional modifications, when viewed in isolation, contributes to feminization, but their true power emerges from their synergistic integration.

The advancements in preoperative planning, particularly the integration of high-resolution 3D imaging and virtual surgical planning systems, have revolutionized the field, allowing surgeons to create highly detailed blueprints of the desired transformation. This technological synergy enhances precision, minimizes risks, and optimizes predictability, transitioning complex cases from challenging guesswork to precisely engineered solutions. Intraoperative challenges, such as the meticulous preservation of neurovascular structures and the dynamic adaptation to anatomical variations, underscore the demanding nature of these procedures and highlight the critical role of profound surgical experience. Furthermore, the post-operative recovery, often protracted and intensive, requires a comprehensive and patient-centered management plan to ensure optimal healing and long-term stability. Beyond the aesthetic alterations, successful facial feminization inherently encompasses the restoration or improvement of vital facial functions, addressing potential impairments related to mastication, vision, and breathing. This dual emphasis on form and function ensures that the patient not only achieves an external appearance congruent with their identity but also experiences a significant enhancement in overall quality of life.

The selection of a highly specialized surgeon, one possessing deep expertise in both facial feminization and complex maxillofacial reconstruction, stands as the single most critical decision for individuals embarking on this journey. Their unique skill set, combining artistic vision with a profound anatomical understanding, is indispensable for navigating the intricacies of advanced cases and delivering results that are both safe and aesthetically profound. Ultimately, facial feminization surgery, particularly when tailored to the individual’s unique anatomy, is a powerful affirmation of identity, fostering self-confidence and providing a deeper sense of authenticity. It is a testament to the continuous evolution of surgical science and artistry, offering life-changing possibilities for those seeking harmony between their inner self and outer presentation. The ongoing commitment to precision, personalized care, and comprehensive outcomes will continue to define this vital and transformative field, providing hope and tangible results for countless individuals.

Frequently Asked Questions

Why is individual facial anatomy so important in planning facial feminization surgery?

Individual facial anatomy is crucial because every face is unique, with varying bone structures and soft tissue distributions. A personalized surgical strategy, tailored to these specific anatomical nuances, ensures the most natural, harmonious, and effective feminization outcomes, as opposed to a generic approach.

What role do 3D imaging and virtual surgical planning play in customizing facial feminization procedures?

3D imaging, such as CT scans, provides a detailed blueprint of the patient’s skeletal and soft tissue architecture. Virtual surgical planning software allows surgeons to simulate procedures, precisely measure modifications, and design custom guides, significantly enhancing surgical precision, safety, and predictability.

How do bone modifications and soft tissue procedures interact synergistically in facial feminization?

Bone modifications (e.g., forehead contouring, jaw reduction) provide the foundational changes, redefining the facial framework. Soft tissue procedures (e.g., rhinoplasty, cheek augmentation, lip lifts) then refine these contours, add volume, and enhance expressions. Their synergistic combination ensures a cohesive, balanced, and naturally feminine appearance.

What are some of the critical challenges faced during complex facial feminization surgeries?

Challenges include meticulous preservation of vital neurovascular structures (like facial nerves), managing compromised blood supply in scarred tissues, adapting to unexpected anatomical variations, and ensuring precise symmetry. These demand exceptional surgical skill and adaptability.

What kind of recovery can be expected after extensive facial feminization surgery?

Recovery from extensive procedures typically involves significant swelling, bruising, and discomfort, which gradually subside over weeks to months. Full resolution of swelling and bone healing can take up to a year or more. Adherence to post-operative care, including rest, head elevation, and a soft diet, is crucial.

Beyond aesthetics, what other benefits does facial feminization surgery offer?

Beyond aesthetic alignment, facial feminization surgery can significantly improve or restore vital facial functions such as mastication (chewing), vision, and breathing, especially in cases of pre-existing skeletal deficiencies. This dual focus enhances overall quality of life, reduces psychological distress, and fosters greater social confidence.

What qualifications should one look for in a surgeon for complex facial feminization?

For complex cases, seek a surgeon with dual proficiency in both routine facial feminization and intricate maxillofacial reconstruction. This specialist should have extensive experience, board certification in relevant specialties, a strong portfolio of results, and expertise in advanced technologies like 3D virtual surgical planning.

Bibliography

  • Alraddadi, A. (2021). Literature Review of Anatomical Variations: Clinical Significance, Identification Approach, and Teaching Strategies. Cureus, 13(4), e14451. https://pmc.ncbi.nlm.nih.gov/articles/PMC8117423/
  • Barnett, S. L., Choe, J., Aiello, C., & Bradley, J. P. (2023). Facial Feminization Surgery: Anatomical Differences, Preoperative Planning, Techniques, and Ethical Considerations. Medicina (Kaunas), 59(12), 2070. https://pmc.ncbi.nlm.nih.gov/articles/PMC10744788/
  • Dr. MFO. (2025a, October 13). Advanced Reconstructive FFS: Surgical Techniques for Severe Facial Skeletal Deficiencies. https://www.dr-mfo.com/advanced-reconstructive-ffs-surgical-techniques/
  • Dr. MFO. (2025b, July 4). Key Anatomical Considerations for Combined Nose and Cheek Procedures in Transgender FFS. https://www.dr-mfo.com/combined-nose-cheek-ffs-anatomical-considerations/
  • Dr. MFO. (2025c, July 10). FFS Procedures: Bone vs. Soft Tissue Modification for Facial Feminization. https://www.dr-mfo.com/ffs-procedures-bone-vs-soft-tissue-modification/
  • KLS Martin. (n.d.). IPS Implants® Transformation. Retrieved October 26, 2025, from https://www.klsmartin.com/en/products/individual-patient-solutions-cmf/ips-implants/ips-implants-transformation/
  • Singh, G. D., & Singh, M. (2021). Virtual Surgical Planning: Modeling from the Present to the Future. Journal of Clinical Medicine, 10(23), 5655. https://pmc.ncbi.nlm.nih.gov/articles/PMC8658225/
  • Stryker. (n.d.). VSP® Solutions. Retrieved October 26, 2025, from https://www.stryker.com/us/en/craniomaxillofacial/systems/virtual-surgical-planning–vsp-.html

Advanced FFS: 5 Critical Interventions for Craniofacial Stability & Resorption

A close-up portrait of a woman's face, focusing on her eyes and nose against a neutral background.

Craniofacial instability and bone resorption are significant, yet often underestimated, complications that can arise following facial feminization surgery (FFS). These issues, characterized by the unwanted movement of surgically modified bone segments or implants, and the gradual loss of bone tissue, can profoundly impact both the aesthetic longevity and functional integrity of the surgical outcome.

The intricate nature of FFS, which often involves extensive reshaping and repositioning of facial skeletal structures, inherently carries a risk of such challenges, especially in cases where the underlying anatomy is already complex or compromised.

While initial surgical success might be achieved, the long-term stability of these delicate modifications is paramount for enduring patient satisfaction and well-being. Therefore, understanding the mechanisms behind these post-operative phenomena and mastering advanced reconstructive strategies to address them is crucial for any specialist in this field. Without meticulous attention to the biomechanical forces at play and the biological processes of bone healing, even expertly performed primary FFS can lead to unforeseen complications that necessitate further intervention.

The impact of craniofacial instability extends beyond superficial aesthetic concerns, potentially affecting vital functions such as mastication, vision, and breathing. For instance, an unstable jawline contour can disrupt dental occlusion, leading to chewing difficulties and temporomandibular joint issues. Similarly, bone resorption in the orbital region can compromise eye support and protection, potentially leading to visual disturbances or discomfort. Recognizing and effectively managing these complications requires a specialized approach, one that integrates a deep understanding of craniofacial anatomy with advanced surgical techniques honed through extensive experience in reconstructive procedures. This comprehensive perspective ensures that interventions not only restore a harmonious feminine aesthetic but also preserve or improve essential facial functions.

This article delves into the complexities of craniofacial instability and bone resorption following facial feminization surgery, providing an in-depth analysis of their underlying causes, precise diagnostic methodologies, and cutting-edge surgical interventions designed for correction. It will explore the nuanced interplay of surgical technique, material science, and patient biology that contributes to these post-operative challenges.

Furthermore, we will examine advanced reconstructive strategies, including sophisticated bone grafting methods, custom implant solutions, and refined internal fixation systems, which are essential for re-establishing structural integrity and achieving stable, natural-looking results. The discussion will also cover critical perioperative management considerations, outline the recovery trajectory, and highlight the long-term outlook for patients undergoing these complex reconstructive procedures. Ultimately, this exploration aims to underscore the critical importance of specialized expertise and advanced technological integration in addressing and overcoming the intricate challenges posed by post-FFS craniofacial instability and bone resorption, ensuring optimal, enduring outcomes for individuals seeking a complete and affirming transformation.

A woman with a serious expression, wearing a green turtleneck sweater, sitting on a brown couch against a dark background.

Understanding the Problem

Causes of Bone Resorption Post-FFS

Bone resorption, or the partial loss of bone in a specific area, represents a significant concern after facial feminization surgery, particularly in regions where bone reduction or reshaping has occurred. This phenomenon can lead to depressions, irregularities, and asymmetries that compromise the intended aesthetic outcome.

Understanding its multifactorial causes is crucial for prevention and effective treatment. One primary mechanism involves the exposure of medullary bone during surgical burring. The forehead bone, for example, consists of an outer cortical layer and an inner medullary or spongy layer. While cortical bone is dense and less prone to resorption, the softer, more porous medullary bone, if left unprotected and extensively exposed, is highly susceptible to reabsorption (Facialteam, 2020). This typically occurs within the first weeks or months post-surgery, manifesting as visible or palpable depressions.

Furthermore, the surgical technique itself plays a critical role. In procedures involving the frontal sinus region, such as forehead reconstruction where the anterior wall is removed and later re-fixed, inadequate stability of the bone fragment can trigger resorption. If the fixation system or material used does not ensure sufficient stability, micro-movements during the healing phase can lead to poor bone consolidation and subsequent loss of bone tissue (Facialteam, 2020). This highlights the necessity of rigid and stable fixation methods to promote proper bone healing and prevent undesired resorption. Excessive weakening or perforation of the frontal sinus wall through aggressive burring can also predispose the area to resorption.

Implant materials also influence the risk of resorption. While autologous bone grafts, derived from the patient’s own body, integrate biologically and are less prone to rejection, their long-term viability can be affected by factors such as the vascularity of the recipient site and biomechanical stresses.

Alloplastic implants, made from synthetic biocompatible materials, generally do not resorb, but their placement can sometimes induce pressure atrophy in the underlying bone if not meticulously designed and secured. Patient-specific healing responses and systemic factors like nutritional status or hormonal imbalances can also play a role in the extent of bone resorption. Additionally, biomechanical stresses, particularly in dynamic areas like the jawline, can contribute to bone remodeling that is not always favorable, potentially leading to resorption in areas of high stress or inadequate support.

Manifestations of Instability

Craniofacial instability post-FFS can manifest in various ways, ranging from subtle aesthetic irregularities to significant functional impairments. These manifestations often become apparent as the initial post-operative swelling subsides, revealing underlying structural issues. One common presentation involves the shifting or malposition of surgically modified bone segments or implants. For instance, if a bone flap from a forehead setback procedure is not rigidly fixed, it may shift, creating an uneven contour or an undesirable depression. Similarly, alloplastic implants, if inadequately secured, can migrate or become palpable through the soft tissue, leading to an unnatural appearance and potential discomfort (Facialteam, 2020).

Aesthetic consequences of instability can include visible depressions, asymmetries, or an unharmonious facial contour. Patients may notice palpable edges of bone segments or implants that were intended to be smooth and integrated. These irregularities can be a significant source of distress, undermining the psychological benefits of the initial feminization surgery. Moreover, soft tissue alterations, such as uneven redraping or localized sagging, can occur as a secondary effect of underlying skeletal instability, further compromising the aesthetic outcome.

Beyond aesthetics, instability can lead to considerable functional problems. In the lower face, an unstable jawline or chin can result in malocclusion, making chewing difficult or painful. Discrepancies in the temporomandibular joint (TMJ) can also arise, causing pain, clicking, or limited jaw movement. Instability in the midface or orbital region might compromise vision or ocular comfort, while nasal bone instability could lead to impaired breathing or chronic sinusitis if the nasal passages are affected.

The integrity of critical neurovascular structures can also be jeopardized if unstable bone fragments impinge upon nerves or blood vessels, potentially causing persistent numbness, pain, or compromised tissue viability. Therefore, addressing instability is not only about restoring facial harmony but also about ensuring the long-term functionality and health of the craniofacial complex.

Diagnostic Approaches

Accurate diagnosis is the cornerstone of effective intervention for craniofacial instability and bone resorption post-FFS. Advanced imaging techniques have revolutionized the ability to precisely identify and map these complex anatomical issues, providing surgeons with a detailed blueprint for reconstructive planning. High-resolution imaging modalities, such as Cone-Beam Computed Tomography (CBCT) and standard Computed Tomography (CT) scans, are indispensable tools in this diagnostic phase (Barnett et al., 2023). These scans generate detailed three-dimensional anatomical data of the patient’s skull and overlying soft tissues, offering an unparalleled view of the underlying skeletal architecture.

The granular data obtained from CT or CBCT scans allows for an accurate diagnosis of existing skeletal differences, including subtle bone volume deficits, malposition of facial segments, and precise assessment of critical underlying structures. Surgeons can meticulously identify areas of bone resorption, quantify the extent of bone loss, and detect any shifting or migration of implants or bone fragments. These images are also crucial for evaluating the integrity of fixation devices and assessing the overall stability of the reconstructed areas. Furthermore, advanced software can be used to generate three-dimensional reconstructions, which aid in visualizing the complex interplay between different facial components and precisely pinpointing the source of instability or contour irregularities.

Beyond static images, specialized software tools can perform quantitative analyses, measuring bone density, assessing bone graft integration, and comparing current anatomy to the pre-operative plan or ideal feminine facial templates. This objective data helps in understanding the precise nature of the post-operative changes and guiding the choice of the most appropriate reconstructive strategy. The ability to precisely map out existing anatomy, including the exact location of critical neurovascular structures, is paramount for minimizing risks during subsequent revision surgeries. By leveraging these cutting-edge diagnostic approaches, specialists can formulate highly individualized and accurate treatment plans that address the specific intricacies of each patient’s post-FFS complications, thereby optimizing the potential for successful functional and aesthetic restoration.

A smiling woman with sunglasses on her head, looking to the side with a blurred city background.

Advanced Surgical Strategies for Correction

Correcting craniofacial instability and bone resorption after facial feminization surgery demands a sophisticated array of advanced surgical strategies. These interventions move beyond simple aesthetic adjustments, focusing on rebuilding and stabilizing the underlying skeletal framework. The choice of technique is highly personalized, dependent on the nature and extent of the identified deficiencies and instabilities. The goal is to restore structural integrity, achieve harmonious contours, and ensure long-term stability and function.

Bone Grafting Techniques

Bone grafting is a fundamental technique in reconstructive facial surgery, particularly when addressing volume deficits and structural insufficiencies resulting from bone resorption. It involves transplanting bone tissue to augment or rebuild compromised areas. There are two primary types: autogenous and alloplastic grafts. Autogenous bone grafts, harvested from the patient’s own body, are considered the gold standard due to their biological compatibility. They contain living bone cells (osteocytes and osteoblasts) and growth factors, promoting successful integration and remodeling into the recipient site with minimal risk of rejection (Dr. MFO, 2025a).

Common donor sites for autogenous grafts include the cranial vault, ribs, and iliac crest. Cranial bone grafts are often preferred for facial reconstruction because of their membranous origin, which makes them less prone to resorption compared to endochondral bone. They are ideal for reconstructing thin, contoured areas like the forehead and orbital rims. Rib grafts, with their natural curvature, can be advantageous for larger defects or for creating specific contours in the jawline or chin. The iliac crest offers a generous supply of corticocancellous bone, providing robust structural support and excellent osteogenic potential, making it suitable for substantial augmentations in the jaw or midface (Dr. MFO, 2025a).

The meticulous shaping and secure fixation of the harvested graft to the recipient site are critical for successful integration. Micro-screws and plates are typically used to ensure precise placement and rigid stability, facilitating osteoinduction and osteoconduction. Successful graft take relies on adequate vascularization of the recipient bed and close contact between the graft and the existing bone. For extreme defects with compromised vascularity, vascularized bone grafts, which include their own blood supply, may be considered, although these are highly complex microsurgical procedures.

A close-up black and white photograph of a person smiling, showing their teeth.

Custom Implant Solutions

When autologous bone is limited, or precise, intricate contouring is essential, custom alloplastic implants offer an excellent alternative. These implants are fabricated from biocompatible synthetic materials, eliminating the need for a donor site. Polyetheretherketone (PEEK) and porous polyethylene (Medpor) are frequently used materials due to their inertness, strength, and ability to be custom-designed (Dr. MFO, 2025a). PEEK implants are robust and can be precisely milled to match complex anatomical contours, providing predictable structural support. Porous polyethylene allows for tissue ingrowth, promoting better integration with surrounding soft tissues and reducing implant migration risk.

The design process for these patient-specific implants is highly sophisticated, utilizing Computer-Aided Design (CAD) and Computer-Aided Manufacturing (CAM) technologies. High-resolution CT or CBCT scans provide detailed 3D digital models of the patient’s facial skeleton. Surgeons then use specialized software to virtually sculpt the desired feminine contours and design an implant that perfectly complements the existing bone structure while correcting deficiencies (Barnett et al., 2023). This virtual planning ensures unparalleled precision, exact anatomical fit, and optimal aesthetic outcomes. Custom implants are particularly advantageous for severe asymmetry, large volume deficits, or when a very specific shape is needed that would be difficult to achieve with freehand bone grafting (Dr. MFO, 2025a).

Internal Fixation Systems

Advanced internal fixation systems are indispensable for achieving rigid and stable fixation in complex craniofacial reconstruction, especially after extensive osteotomies or bone segment repositioning. These systems typically consist of small, biocompatible plates and screws, often made from titanium or resorbable polymers. Titanium systems offer superior strength and are widely used for their durability and inertness. Resorbable plates and screws, while less rigid initially, gradually degrade over time, avoiding potential long-term issues associated with permanent hardware, although their application is more limited in high-stress areas.

The design of these plate and screw systems is tailored to the specific anatomical region and the forces they need to withstand. Micro-plates and screws are used for delicate areas like the orbital rims, while stronger plates are employed for the jawline or forehead. The principles of rigid internal fixation emphasize bicortical fixation (engaging both cortical layers of bone) and ensuring adequate plate length and screw number to resist rotational and shear forces. This rigid fixation is critical for promoting primary bone healing, minimizing micromovement at osteotomy sites, and preventing non-union or malunion. Precision in plate bending and screw placement is paramount to maintain the surgically established contours and prevent palpable hardware.

A close-up photograph of a person's face focusing on their eyes and nose.

Osteosynthesis Refinements

Osteosynthesis, the surgical immobilization of bone fragments, is refined in complex feminization procedures to re-establish bone continuity and stability with exceptional accuracy. This involves precise bone cuts (osteotomies) and their subsequent stable fixation. For instance, in severe cases, modified Le Fort osteotomies can be employed to advance a hypoplastic midface, reshape the maxilla, or correct vertical and transverse discrepancies. Similarly, sagittal split osteotomies of the mandible are crucial for repositioning the lower jaw, allowing for advancement, setback, or rotational changes to create a softer, more tapered jawline and a delicate chin (Dr. MFO, 2025a).

Virtual surgical planning (VSP) significantly refines osteosynthesis by allowing surgeons to pre-plan every cut and movement in a 3D digital environment. This planning facilitates the creation of custom cutting guides and drilling templates, which are then 3D printed and used intraoperatively. These guides ensure that osteotomies are executed with remarkable accuracy, precisely matching the virtual plan and minimizing human error (Barnett et al., 2023). The use of these guides enhances both the safety and predictability of complex bone manipulations, ensuring that bone segments are repositioned correctly and achieve proper bony union. This precision is essential for long-term structural integrity and aesthetic harmony.

Soft Tissue Considerations

While bone reconstruction forms the foundation of corrective strategies, effective soft tissue management is equally critical for optimal aesthetic redraping and a natural final appearance. The overlying skin, fat, and muscle must conform smoothly to the newly established skeletal contours. Techniques such as liposuction, fat grafting, and targeted excisions can be employed to refine soft tissue volume and distribution. For instance, autologous fat grafting, in addition to its aesthetic benefits of adding feminine volume to areas like the cheeks and lips, can also improve local tissue quality and camouflage minor irregularities (Dr. MFO, 2025a).

The tension and elasticity of the soft tissues are carefully considered during surgical planning. In cases where significant bone reduction has occurred, excess soft tissue may require re-draping or even excisional procedures (e.g., a facelift or neck lift) to prevent sagging and ensure a smooth, youthful contour. The goal is to achieve seamless integration, where the soft tissues naturally follow the feminized skeletal framework, minimizing visible surgical evidence and contributing to a harmonious, balanced facial appearance. This integrated approach, addressing both hard and soft tissues, ensures comprehensive and enduring aesthetic outcomes.

Perioperative Management

Perioperative management in complex reconstructive feminization surgery for craniofacial instability and bone resorption is a critical component for ensuring patient safety and optimizing outcomes. These procedures, often lengthy and involving extensive bone manipulation, necessitate specialized considerations across anesthesia, blood loss management, and infection prevention.

Anesthesia for these complex cases requires a highly skilled anesthesiologist with experience in craniofacial surgery. Prolonged operative times and significant fluid shifts are common, demanding meticulous monitoring of vital signs, fluid balance, and airway management. Strategies for controlled hypotension may be employed to minimize intraoperative bleeding, enhancing surgical visibility and reducing overall blood loss. Post-operative pain management is also a key consideration, often involving multimodal analgesia protocols to ensure patient comfort during the intensive recovery phase.

Minimizing blood loss is paramount, as excessive bleeding can obscure the surgical field, increase operative time, and necessitate blood transfusions. Techniques like precise dissection, meticulous hemostasis using electrocautery, and pharmacologic agents (e.g., tranexamic acid) are routinely employed. In cases involving extensive bone cuts or large graft harvesting, surgeons may utilize specialized instruments that reduce bleeding from bone surfaces. Proactive planning for potential blood loss, including pre-operative assessments of coagulation status and availability of blood products, is standard practice.

Infection prevention is another crucial aspect, especially when implants or bone grafts are used. Strict sterile technique throughout the procedure is non-negotiable. Patients typically receive broad-spectrum intravenous antibiotics pre-operatively, intraoperatively, and for a short period post-operatively. Meticulous wound care, often involving antimicrobial rinses for intraoral incisions, is essential. The presence of foreign materials like implants can increase infection risk, underscoring the importance of rigorous aseptic protocols and prompt management of any signs of infection. Furthermore, ensuring adequate nutrition and optimizing overall patient health before surgery can significantly reduce the risk of complications. A highly coordinated multidisciplinary team, including surgeons, anesthesiologists, and nursing staff, is essential for successfully navigating these perioperative complexities.

Recovery and Long-Term Outlook

The post-operative recovery phase following comprehensive reconstructive feminization surgery for craniofacial instability and bone resorption is often more protracted and intensive than typical aesthetic FFS procedures. Patients must be prepared for a journey that demands patience and adherence to a structured management plan, as the significant degree of bone manipulation and tissue reshaping contributes to extensive swelling and bruising.

Immediately after surgery, substantial facial swelling, bruising, and discomfort are expected. Swelling typically peaks within the first few days to a week, gradually subsiding over several weeks to months. However, complete resolution of residual swelling, particularly in areas of major bone work or grafting, can take up to a year or even longer for the final contours to fully emerge (Face2Face Clinic, n.d.).

Bruising will similarly resolve, usually within 2 to 4 weeks, transitioning through various color changes before fading completely. Pain management is crucial and typically involves prescribed analgesia, anti-inflammatory medications, and diligent application of cold compresses to minimize swelling and alleviate discomfort. Hospitalization may be extended for several days after complex osteotomies or large graft placements, allowing for close monitoring of vital signs and early detection of potential complications like hematoma or infection.

Specific post-operative care instructions are meticulously tailored to the procedures performed. For jaw or chin osteotomies, a soft or liquid diet is frequently prescribed for several weeks to prevent undue stress on the healing bone segments and intraoral incisions. Meticulous oral hygiene, often incorporating antimicrobial mouth rinses, is paramount to prevent infection in the oral cavity. Initial activity restrictions are stringent, with patients advised to avoid strenuous activities, heavy lifting, and anything that might elevate blood pressure.

Activity levels are gradually increased as recovery progresses and surgical clearance is granted. Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce swelling (Face2Face Clinic, n.d.). Physical therapy or gentle lymphatic drainage massages may also be advised in later stages to expedite swelling resolution and improve soft tissue suppleness.

Reconstructive procedures inherently carry potential complications beyond those of standard aesthetic surgery. While meticulous surgical techniques are employed to mitigate these, patient awareness and diligent monitoring are essential. Graft resorption, where a portion of transplanted autologous bone is reabsorbed, can lead to a partial loss of contour or volume, occasionally necessitating revision.

For alloplastic implants, potential risks include implant exposure or infection, which can compromise integration and, in severe cases, require removal. Non-union or malunion of osteotomies, though rare, can occur if bone segments fail to heal properly, potentially leading to persistent asymmetry or functional issues requiring further surgical correction. Nerve damage, despite careful intraoperative preservation efforts, can manifest as persistent numbness, altered sensation, or, rarely, motor weakness affecting facial expressions (Barnett et al., 2023).

Regarding long-term stability, the extensive bone reshaping in reconstructive FFS provides a stable and lasting foundation for the feminized face. However, facial structures naturally undergo aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. Regular follow-up appointments are essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction. A commitment to ongoing care and realistic long-term expectations are vital for a successful and enduring reconstructive feminization journey. This comprehensive approach nurtures the transformation, ensuring both aesthetic and functional longevity.

A woman with sunglasses and a denim shirt leaning against a beige wall.

Conclusion: Addressing Post-FFS Craniofacial Challenges with Expertise

The emergence of craniofacial instability and bone resorption following facial feminization surgery represents a complex and demanding set of post-operative challenges. These issues, characterized by the unwanted movement of bone segments or implants and the gradual loss of bone tissue, underscore the intricate biological and biomechanical factors at play in facial skeletal reconstruction. Effective management of these complications is not merely about refining aesthetics but also about ensuring the long-term functional integrity of the facial structures, which is paramount for a patient’s overall quality of life and self-affirmation. This in-depth exploration has highlighted that achieving successful and stable outcomes in these challenging scenarios requires a specialized, multidisciplinary approach that goes far beyond the scope of conventional aesthetic procedures.

We have delved into the multifactorial causes of bone resorption, including the critical role of medullary bone exposure and inadequate fixation techniques. Understanding these underlying mechanisms is fundamental to both preventing and effectively treating post-operative irregularities. Furthermore, the diverse manifestations of craniofacial instability, from subtle aesthetic asymmetries to significant functional impairments affecting chewing, vision, or breathing, underscore the broad impact these complications can have. Precision diagnostics, utilizing advanced 3D imaging technologies such as CT and CBCT scans, coupled with virtual surgical planning, have emerged as indispensable tools. These technologies provide an extraordinarily detailed blueprint of the existing anatomy, allowing surgeons to meticulously identify problem areas and precisely map out corrective interventions, thereby enhancing safety and predictability.

The core of addressing these challenges lies in advanced surgical strategies. Autologous bone grafting, drawing on the body’s own regenerative capacity, offers biologically compatible solutions for volume restoration and structural support, with careful consideration given to donor site selection and rigid fixation. Complementing this, custom alloplastic implants, precisely designed using CAD/CAM technologies, provide tailored solutions for complex defects and specific contouring needs, minimizing donor site morbidity. Complex osteotomies and refined osteosynthesis techniques are crucial for repositioning and stabilizing bone segments, guided by virtual planning to ensure exact execution. Simultaneously, meticulous soft tissue management ensures harmonious redraping over the newly reconstructed skeletal framework, contributing to a natural and cohesive aesthetic result.

Perioperative management, encompassing specialized anesthesia, meticulous blood loss control, and stringent infection prevention protocols, is equally vital to minimize risks and optimize the immediate post-surgical course. The recovery journey, often intensive and extended, necessitates a comprehensive, patient-centered plan, with diligent monitoring for potential complications such as graft resorption, implant issues, or nerve damage. Despite these complexities, the long-term outlook for patients undergoing advanced reconstructive feminization surgery is highly promising, particularly when performed by a uniquely qualified specialist. The extensive bone reshaping provides a stable foundation, offering enduring aesthetic and functional improvements that profoundly enhance a patient’s physical comfort, psychological well-being, and confident integration into society.

Ultimately, the selection of a highly specialized surgeon, one with dual proficiency in both facial feminization and complex maxillofacial reconstruction, is the single most critical decision for individuals navigating these advanced post-FFS challenges. Their unparalleled understanding of intricate craniofacial anatomy, biomechanics, and advanced reconstructive techniques, combined with a compassionate, patient-centered approach, ensures the highest standard of care.

This expertise, coupled with the continuous evolution of surgical science and technological innovation, offers life-changing possibilities. To explore how these advanced techniques can rectify existing issues and safeguard the long-term success of your facial feminization journey, we strongly recommend scheduling a consultation with such a distinguished specialist. This proactive step ensures personalized guidance, a thorough assessment of your unique needs, and the collaborative development of a precise treatment plan aimed at achieving harmonious, functional, and enduring results.

Frequently Asked Questions

What are craniofacial instability and bone resorption in the context of facial feminization surgery?

Craniofacial instability refers to the unwanted movement or malposition of surgically altered bone segments or implants. Bone resorption is the gradual loss of bone tissue in areas where bone reduction or reshaping has occurred. Both can compromise the aesthetic and functional outcomes of facial feminization surgery.

What causes bone resorption after facial feminization surgery?

Bone resorption can be caused by factors such as the extensive exposure of medullary bone during surgical burring, inadequate fixation of bone fragments, properties of implant materials, patient-specific healing responses, and biomechanical stresses on the treated areas.

How is craniofacial instability diagnosed?

Craniofacial instability is typically diagnosed using advanced imaging techniques like high-resolution Computed Tomography (CT) or Cone-Beam Computed Tomography (CBCT) scans. These provide detailed 3D anatomical data, allowing surgeons to identify bone volume deficits, implant migration, and structural malposition.

What advanced surgical techniques are used to correct bone resorption and instability?

Advanced techniques include autologous bone grafting (using the patient’s own bone from donor sites like the cranium or iliac crest), custom alloplastic implants (3D printed from biocompatible materials like PEEK), rigid internal fixation systems, and precise osteotomies guided by virtual surgical planning.

What is the role of 3D virtual surgical planning in these complex procedures?

3D virtual surgical planning utilizes patient CT/CBCT data to create a digital model, allowing surgeons to simulate procedures, plan precise osteotomies, design custom implants and guides, and visualize outcomes before surgery. This enhances accuracy, safety, and predictability.

What can a patient expect during recovery from advanced reconstructive feminization surgery?

Recovery involves significant swelling, bruising, and discomfort, often for several weeks to months. It requires strict adherence to post-operative instructions, including a soft diet, activity restrictions, and meticulous wound care. Full resolution of swelling and bone healing can take up to a year or more.

Why is selecting a specialist with dual expertise important for addressing these complications?

A surgeon with dual expertise in both facial feminization and complex maxillofacial reconstruction is critical. This specialist should have extensive experience, board certification in relevant specialties, a strong portfolio of results, and expertise in advanced technologies like 3D virtual surgical planning.

Bibliography

  • Barnett, S. L., Choe, J., Aiello, C., & Bradley, J. P. (2023). Facial Feminization Surgery: Anatomical Differences, Preoperative Planning, Techniques, and Ethical Considerations. Medicina (Kaunas), 59(12), 2070. https://pmc.ncbi.nlm.nih.gov/articles/PMC10744788/
  • Dr. MFO. (2025a, October 13). Advanced Reconstructive FFS: Surgical Techniques for Severe Facial Skeletal Deficiencies. https://www.dr-mfo.com/advanced-reconstructive-ffs-surgical-techniques/
  • Face2Face Clinic. (n.d.). Recovery after FFS. Retrieved October 26, 2025, from https://face2face.surgery/en/ffs/recovery
  • Facialteam. (2020, September 29). Types of bone irregularities after FFS Surgery. https://facialteam.eu/blog/depressions-irregularities-bone-asymmetries/
  • Birbe, J. (2025). Orthofacial Surgery, the Esthetic Surgery of the Facial Skeleton: Techniques, Approaches, and Outcomes. IntechOpen. https://www.intechopen.com/chapters/1216609

7 Critical Insights: Mastering Facial Skeletal Augmentation in FFS

A woman holding a picture of a face while consulting with a healthcare professional wearing a mask and scrubs.

Facial Feminization Surgery (FFS) represents a deeply intricate and profoundly personal journey, offering a transformative pathway for individuals seeking to align their external appearance with their affirmed feminine identity. This highly specialized field within craniofacial and plastic surgery transcends mere aesthetic enhancements, demanding a meticulous, individualized approach that acknowledges the profound and inherent variations in human facial anatomy. The fundamental principle guiding successful facial feminization is the understanding that no two faces are identical, nor do they present the same set of masculine characteristics to be addressed. Therefore, a “one-size-fits-all” methodology is inherently inadequate for achieving optimal, natural-looking, and deeply satisfying results. Instead, the process necessitates a bespoke surgical strategy meticulously tailored to each patient’s unique underlying skeletal and soft tissue architecture, which is a complex interplay of genetic predisposition, developmental factors, and the effects of hormonal influences.

This comprehensive guide will delve into the critical role of distinctive facial anatomy in shaping the precise surgical interventions and techniques employed during FFS, underscoring how a nuanced appreciation of individual features culminates in a truly personalized and effective transformation. We will explore how expert surgeons navigate the complex landscape of craniofacial differences between sexes, which range from the subtle contours of the brow to the more pronounced angles of the jaw, and how these anatomical nuances directly inform the selection and execution of feminizing procedures. The objective is not merely to soften overtly masculine traits but to sculpt a cohesive and balanced facial appearance that authentically reflects the individual’s gender identity, thereby enhancing psychological well-being, alleviating gender dysphoria, and facilitating social affirmation (Barnett et al., 2023).

This exploration will highlight the advanced diagnostic tools, such as high-resolution 3D imaging and sophisticated virtual surgical planning systems, that empower surgeons to create a detailed, three-dimensional blueprint of the patient’s face. This technological integration enables an unprecedented level of precision in preoperative strategizing, allowing for simulated outcomes and customized surgical guides. Furthermore, we will examine how various surgical techniques, encompassing both osseous (bone) modifications—which address the fundamental framework of the face—and soft tissue refinements—which provide the delicate finishing touches—are synergistically integrated to produce a harmonious outcome that maintains naturalness while achieving profound feminization.

The discussion will extend to the critical considerations involved in managing patient expectations, ensuring they are grounded in surgical realism, and understanding the unique challenges posed by significant anatomical variations. We will also emphasize the paramount importance of selecting a highly experienced specialist who possesses a deep understanding of both aesthetic principles and complex craniofacial reconstruction. Ultimately, this detailed analysis aims to illuminate the profound interplay between individual facial anatomy and surgical artistry, revealing how a deeply personalized approach is not just beneficial, but absolutely the cornerstone of transformative, durable, and profoundly impactful facial feminization outcomes.

A doctor examining a 3D digital model of a skull displayed on a computer screen, highlighting the teeth and jaw area.

Understanding the Blueprint: Foundational Anatomy for Facial Feminization

Before any surgical intervention commences, a profound understanding of the patient’s foundational facial anatomy is paramount. A skilled facial feminization surgeon meticulously assesses the intricate interplay of underlying bone and overlying soft tissue structures. This comprehensive evaluation is critical because inherent differences in skeletal proportions and soft tissue distribution are key determinants of perceived gender.

Typically, masculine facial features often involve a more prominent brow ridge, a broader and squarer jawline, a larger and more anteriorly projected chin, and a distinct nasal profile characterized by a higher bridge and less upward rotation of the tip. However, the degree of expression of these features varies significantly among individuals due to genetic, ethnic, and developmental factors (Alraddadi, 2021). Recognizing these individual anatomical nuances is not merely an observational step but the foundational prerequisite for crafting a truly tailored and effective surgical plan.

To acquire this detailed anatomical blueprint, advanced diagnostic imaging plays an indispensable role. Three-dimensional computed tomography (3D CT) scans are frequently employed, providing a high-resolution, three-dimensional reconstruction of the patient’s unique skeletal and soft tissue architecture. These scans offer an unparalleled view of bone density, sinus pneumatization, nerve pathways, and the precise contours of the facial skeleton (Barnett et al., 2023). This data is then utilized in conjunction with virtual surgical planning (VSP) software, allowing surgeons to precisely measure existing structures and simulate potential surgical modifications.

Beyond static images, dynamic assessments of soft tissue mobility, skin elasticity, and muscle activity are also incorporated. Understanding the variations in tissue thickness and elasticity, for instance, is crucial for anticipating how overlying soft tissues will redrape following bone reductions or augmentations. The combination of comprehensive physical examination and advanced imaging provides the surgeon with a holistic understanding of the patient’s facial landscape, enabling them to formulate a feminization strategy that is both anatomically sound and aesthetically harmonious, moving beyond generic ideals to achieve results that are authentic to the individual.

A surgeon in medical attire, including a mask and gloves, is performing a procedure on a patient's forehead. The patient is lying down with their eyes closed while the surgeon holds a tool and draws lines on the forehead as a guide for the procedure.

Regional Deep Dive: Anatomical Impact on Specific Feminization Techniques

The Forehead and Orbital Rims: Sculpting a Feminine Foundation

The upper third of the face, comprising the forehead and orbital rims, is a primary region for gender recognition. Variations in the frontal bone and supraorbital ridge (brow bone) are among the most significant sexually dimorphic features. Masculine foreheads often present with a prominent brow bossing, a heavier and more horizontally positioned brow relative to the superior orbital rim, and a forehead that recedes backward. In stark contrast, feminine foreheads are typically characterized by a smoother, rounder contour, a more vertically oriented profile, and eyebrows that arch higher, positioned above the orbital rim (Barnett et al., 2023). The degree of frontal bossing can vary considerably among individuals, directly impacting the complexity and choice of surgical intervention.

These anatomical variations directly influence the selection of forehead contouring procedures, primarily categorized into Type 1 (shaving), Type 2 (combination), or Type 3 (setback) techniques. For individuals with a relatively thick anterior frontal sinus wall and less pronounced bossing, a Type 1 procedure, involving direct burring or shaving of the prominent bone, may suffice to create a smoother transition. However, when the frontal sinus bone is thinner or the brow bossing is significantly prominent, a more extensive approach is often necessitated.

A Type 3 cranioplasty, also known as frontal sinus setback, involves carefully removing the anterior wall of the frontal sinus, meticulously reshaping it, and then reattaching it in a more recessed and feminized position (Barnett et al., 2023). This reconstructive technique allows for a greater degree of reduction and a more profound feminizing effect, fundamentally altering the supraorbital contour and achieving the desired convex curvature of a feminine forehead.

In conjunction with forehead contouring, orbital rim contouring is frequently performed to further enhance upper facial feminization. In masculine faces, the bony edges around the eye sockets can appear heavier and more angular, often casting shadows that masculinize the eyes. By carefully smoothing and rounding these edges, the eyes appear larger, more open, and less shadowed, contributing to a softer, more inviting gaze. The precise execution of these modifications, especially near critical structures such as the supraorbital and supratrochlear nerves, is paramount to prevent sensory deficits.

Additionally, the natural hairline position and any existing brow descent will guide the selection of brow lift techniques. A coronal incision, extending across the scalp, may be chosen for significant hairline advancement combined with forehead contouring, whereas an endoscopic brow lift, utilizing smaller incisions within the hairline, can achieve brow elevation with minimal hairline change, particularly when hairline lowering is not a primary objective. Virtual surgical planning, as detailed by Barnett et al. (2023), has emerged as an indispensable tool, allowing surgeons to precisely visualize desired outcomes and plan osteotomies with enhanced accuracy, significantly reducing operative time and minimizing complications like over-resection or nerve injury. This meticulous pre-surgical mapping ensures that the altered contours integrate seamlessly with the rest of the face, providing a harmonious and distinctly feminine upper facial aesthetic.

A woman with red hair is looking out of a window, with sunlight illuminating her face, creating a serene and contemplative atmosphere.

Midface and Cheeks: Sculpting Softness and Projection

The midface, prominently defined by the zygomatic (cheekbone) complex and the overlying soft tissues, plays a pivotal role in the perception of facial femininity and youthfulness. Significant variations exist in midface projection and contour between masculine and feminine physiognomies. Masculine midfaces often exhibit flatter zygomas with less anterior projection, contributing to a less triangulated facial shape. In contrast, feminine cheeks are typically characterized by higher, more anteriorly positioned zygomatic arches, creating a desirable convexity and contributing to a softer, more youthful, and often “heart-shaped” facial contour (Barnett et al., 2023). The distribution and volume of subcutaneous fat, including the malar fat pad and buccal fat, also vary considerably, further influencing overall midface appearance.

Surgical strategies for midface feminization are highly individualized, contingent upon the patient’s existing anatomical structure and desired aesthetic. When there is insufficient malar projection or a naturally flatter midface, cheek augmentation is often recommended. This can be achieved through various methods. Autologous fat grafting, which involves harvesting fat from other areas of the patient’s body (e.g., abdomen or thighs) via liposuction, processing it, and then injecting it into the cheeks, offers a natural solution. This technique provides a soft, natural-looking augmentation and can simultaneously improve the quality of the overlying skin. Alternatively, custom alloplastic implants, typically made of biocompatible materials such as silicone, can be placed over the cheekbones to provide permanent volume and definition. These implants are either pre-designed or custom-fabricated based on 3D virtual surgical planning to precisely match the desired contours (Barnett et al., 2023).

Conversely, in rare instances where cheekbones are excessively wide or prominently angled in a masculine manner, a surgeon might consider zygomatic arch reduction to soften the midface width. Furthermore, the distribution of buccal fat—a deep fat pad located within the cheek—can impact facial fullness. For individuals with a fuller, rounder lower face that detracts from a feminine aesthetic, buccal fat pad removal may be considered to create a more defined and hollowed submalar region, enhancing the appearance of higher cheekbones.

The delicate interplay between these procedures allows for the creation of an “ogee curve”—a graceful, double S-curve contour from the temple to the cheek, which is highly indicative of youthful, feminine cheeks. When combining nose and cheek procedures, as highlighted by Dr. MFO (2025b), synergistic anatomical planning is critical due to the interdependence of nasal and midface aesthetics. An overly prominent nose, for example, can make the midface appear recessed, while well-projected cheekbones can visually balance a nose. Therefore, modifications in one area profoundly influence the perception of the other, requiring an integrated approach to achieve overall facial harmony.

The Nose: Achieving Delicate Proportions

The nose, positioned centrally on the face, is a critical feature that significantly influences overall facial balance and perceived gender. Nasal structures exhibit immense diversity, yet distinct patterns contribute to gender recognition. Masculine noses often feature a broader nasal bridge, a more prominent dorsal hump, wider nostrils (alar base), and a less upwardly rotated, sometimes even downwardly projecting, nasal tip. In contrast, feminine noses are typically characterized by a smaller overall size, a narrower bridge, a softer or slightly concave dorsal profile, and a more refined, slightly upturned nasal tip, contributing to a more obtuse nasolabial angle (Barnett et al., 2023).

This wide spectrum of nasal anatomy necessitates a comprehensive range of rhinoplasty techniques during facial feminization. Dorsal hump reduction is a common procedure, involving the careful removal or rasping of excess bone and cartilage along the nasal bridge to create a smoother, more delicate profile. Concurrently, narrowing the nasal bones through osteotomies (controlled bone cuts) helps to reduce the overall width of the nasal bridge, contributing to a more refined appearance. Tip plasty techniques are pivotal for feminizing the nasal tip; these involve meticulous reshaping of the lower lateral cartilages through excisions, sutures, and grafts to make the tip smaller, more defined, and appropriately rotated upward (Barnett et al., 2023). Alar base reduction may be performed to narrow excessively wide nostrils, which can be a masculine characteristic, ensuring the nasal base is proportionate to the feminized tip and bridge. The specific aims are to create a nose that harmonizes with the newly contoured forehead and midface, avoiding an overly aggressive or artificial appearance.

An open rhinoplasty approach, utilizing a small incision across the columella and internal incisions, is often favored in facial feminization due to the optimal access and visibility it provides to the underlying skeletal and cartilaginous framework. This allows the surgeon to precisely manipulate structures and address specific feminizing goals, such as caudal septal trimming for upward tip rotation (Barnett et al., 2023). The intricate relationship between the bony and cartilaginous components of the nose demands a highly skilled surgeon to achieve stable and aesthetically pleasing results.

Furthermore, the soft tissue envelope, comprising skin, subcutaneous fat, and muscle, plays a significant role in the final outcome; its thickness and elasticity determine how readily underlying changes will be revealed. Consideration of the nasal vascular supply, primarily from branches of the ophthalmic and facial arteries, and innervation from the trigeminal nerve, is crucial to minimize complications such as bleeding or sensory changes. The ultimate goal is to sculpt a nose that is in harmonious proportion with the overall feminized facial features, enhancing the patient’s self-perception and social comfort (Dr. MFO, 2025c).

Jawline and Chin: Softening the Lower Face

The lower third of the face, particularly the jawline and chin, are primary indicators of sexual dimorphism and significantly contribute to perceived gender. Masculine jawlines are typically broader, squarer, and more angular, often presenting with prominent mandibular angles and a thicker external oblique ridge. The chin in masculine faces can be wider, squarer, or excessively prominent, contributing to a strong, sometimes blunt, lower facial appearance. Conversely, feminine jawlines are generally narrower, more tapered, and often exhibit a graceful V-shape or oval contour with softer angles. The chin in feminine faces is typically more delicate, with less width and projection, contributing to a refined lower facial profile (Barnett et al., 2023).

Surgical strategies for feminizing the jawline and chin involve meticulously tailored osseous modifications. Mandibular angle reduction is a key procedure designed to soften the posterior jawline. This involves carefully shaving or resecting a portion of the bone at the prominent jaw angles, transforming a square contour into a smoother, more tapered transition from the ear to the chin. This procedure is often performed through intraoral incisions (inside the mouth) to avoid visible external scarring, allowing for precise osteotomy and contouring while mitigating damage to vital structures such as the inferior alveolar nerve (Barnett et al., 2023).

Chin reshaping, or genioplasty, addresses the size, projection, and shape of the chin. In facial feminization, the goal is often to reduce chin width, shorten its vertical height if it is excessively long, and/or reshape it to a more pointed or rounded form, depending on the patient’s desired outcome and existing anatomy. A common technique is the sliding genioplasty, where the chin bone is carefully cut horizontally, and the distal segment is repositioned. This segment can be moved backward for reduction, advanced for increased projection, vertically shortened, or narrowed to achieve the desired delicate, feminine contour. The repositioned bone segment is then secured with small plates and screws to ensure stability and predictable healing (Barnett et al., 2023).

For chins that primarily require reduction in width or projection without significant repositioning, direct bone shaving or burring can be performed. The integration of these procedures often culminates in a “V-line” surgery, which combines mandibular angle reduction and genioplasty to create a significantly more tapered and feminine lower facial silhouette. In some cases, masseter muscle reduction, either surgically or through botulinum toxin injections, may also be considered for individuals with hypertrophied (enlarged) jaw muscles contributing to excessive lower facial width. The combined effect of these carefully planned interventions results in a more graceful, harmonious, and distinctly feminine lower face, balancing the features modified in the upper and mid-face (Dr. MFO, 2025a).

The Trachea: A Smoother Neckline

The laryngeal prominence, commonly known as the Adam’s apple, is a distinct secondary sex characteristic that develops and becomes more prominent during male puberty due to the enlargement and acute angle of the thyroid cartilage. Its presence can be a significant source of gender dysphoria for many transgender women, as it is a highly visible feature immediately indicative of a masculine neck profile. A tracheal shave, also known as chondrolaryngoplasty, is a straightforward yet highly effective feminizing procedure specifically designed to reduce the size and prominence of the Adam’s apple (Barnett et al., 2023).

The procedure typically involves making a small, discreet transverse incision in a natural skin crease on the neck, often at the midpoint between the submental crease and the cervicomental angle, to minimize the visibility of any resulting scar. Through this incision, the surgeon carefully shaves down the most prominent part of the thyroid cartilage, reducing its projection and creating a smoother, softer contour of the neck. Extreme care is taken to preserve a rim of cartilage superior to the level of the vocal cords for stabilization and, crucially, to avoid damaging the vocal cords themselves, which are located just behind the cartilage (Barnett et al., 2023). This meticulous approach ensures that vocal function is preserved. While primarily a modification of cartilage, which is a form of skeletal tissue, the tracheal shave profoundly impacts the overall appearance of the neck and profile, contributing to a more feminine silhouette and alleviating a significant source of dysphoria.

The recovery from a tracheal shave is generally quicker than from more extensive bone procedures, with most acute swelling and discomfort subsiding within a few weeks. Patients may experience some temporary voice changes or a sensation of tightness immediately after the surgery, but these usually resolve as the healing progresses. In some cases, submental fat excision and platysmaplasty (neck muscle tightening) may be performed concurrently to further enhance the desired neck silhouette and achieve maximal skin tightening, especially in older patients where skin laxity is a greater concern (Barnett et al., 2023). For many individuals, achieving a smoother neckline provides immense psychological relief, allowing them to feel more comfortable and confident in their appearance, particularly when wearing clothing that exposes the neck. This relatively contained procedure offers a significant impact on overall gender affirmation by addressing one of the most visible masculine features of the head and neck region.

A professional woman in a business suit standing in front of a modern building with glass windows.

Integrating Techniques for Holistic Feminization: The Art of Synergy

True facial feminization rarely involves a singular procedure. Instead, it is an intricate symphony of coordinated surgical interventions, each meticulously planned to complement the others and holistically address the patient’s unique anatomy. The skilled surgeon acts as an architect, orchestrating a series of modifications—ranging from fundamental bone restructuring to subtle soft tissue refinements—to achieve a balanced, harmonious, and naturally feminine outcome. This integrated approach ensures that the overall result is cohesive and congruent with the patient’s gender identity, rather than a collection of isolated, disconnected changes. The synergy between procedures is paramount, as altering one facial component inevitably influences the perception and aesthetics of adjacent and distant features.

For instance, a reduction in brow bossing not only feminizes the forehead but also optically enlarges the eyes, making a subtle rhinoplasty’s impact even more pronounced. Similarly, jawline and chin reshaping procedures provide a narrower foundation, over which soft tissues drape more delicately, enhancing the effect of cheek augmentation and lip lifts. The thoughtful sequencing and combination of these techniques are what elevate facial feminization from mere surgical alteration to a sophisticated art form.

The decision for a comprehensive, single-stage facial feminization surgery versus a staged approach (multiple surgeries performed over time) is heavily influenced by the anatomical complexity of the case, the patient’s overall physical health, and personal preferences. While a single-stage procedure offers the convenience of one recovery period and often significant cost savings, patient safety remains the ultimate priority. Studies indicate that an increased number of procedures performed per anesthetic event in facial feminization patients does not necessarily predict higher complication rates, suggesting that well-planned, comprehensive single-stage approaches can be safely undertaken under appropriate medical judgment (Barnett et al., 2023).

However, for individuals with extensive surgical needs, significant medical comorbidities, or those who prefer to recover from smaller interventions sequentially, a staged approach may be more appropriate. In such cases, structural hard tissue procedures like frontal sinus setback, supraorbital contouring, jawline tapering, and rhinoplasty are often prioritized, followed by subsequent soft tissue procedures like facelifts, neck lifts, and blepharoplasty, particularly in older patients where skin laxity is a consideration (Barnett et al., 2023). This strategic sequencing ensures that the foundational skeletal changes are established before refining the overlying soft tissues, thereby optimizing both the aesthetic and functional outcomes. Regardless of the staging strategy, the overarching goal is to achieve seamless integration, where each surgical modification contributes harmoniously to the final feminine facial contour.

Preoperative Planning and Technological Advancements for Precision

The success of advanced facial feminization surgery, particularly in cases involving significant anatomical variations, hinges critically on comprehensive and precise preoperative planning. This crucial phase has undergone a profound revolution with the integration of cutting-edge imaging modalities and virtual technologies, offering an unprecedented level of accuracy and predictability. High-resolution imaging, such as Cone-Beam Computed Tomography (CBCT) and standard Computed Tomography (CT) scans, provides detailed three-dimensional anatomical data of the patient’s skull and overlying soft tissues (Barnett et al., 2023).

This granular data is absolutely essential for an accurate diagnosis of existing skeletal differences, including bone volume deficits, subtle asymmetries, malposition of facial segments, and a precise assessment of critical underlying structures such as nerve pathways and sinus cavities. The detailed understanding derived from these images forms the fundamental bedrock upon which the entire surgical strategy is built, allowing surgeons to meticulously map out the existing anatomy and pinpoint all areas requiring correction or augmentation.

Building upon this rich imaging data, three-dimensional virtual surgical planning (VSP) systems have become indispensable tools in contemporary facial feminization. VSP involves importing the patient’s CT or CBCT data into specialized software, where a precise 3D digital model of the face and skull is generated. Within this sophisticated virtual environment, surgeons can meticulously plan every osteotomy (bone cut), bone graft placement, and custom implant positioning. This digital platform allows for the simulation of various surgical scenarios, enabling surgeons to virtually adjust bone segment movements, refine contours, and visualize the potential aesthetic and functional outcomes before making any physical incisions. This iterative planning process ensures precise measurement of bone reductions or augmentations, guaranteeing that the final contours align not only with feminizing principles but also with the patient’s specific reconstructive needs. For example, customized cutting guides and drilling templates can be virtually designed and subsequently 3D printed, which are then used intraoperatively to execute the planned osteotomies with remarkable accuracy, thereby minimizing human error and enhancing surgical precision (Barnett et al., 2023).

Beyond virtual planning, the emerging role of artificial intelligence (AI) in preoperative morphing offers further advancements. AI-based software, such as DeepSurface AI, can generate three-dimensional morphs of the patient’s face, which can then be adjusted in real-time to demonstrate potential surgical outcomes across various facial regions (Barnett et al., 2023). While still an evolving area requiring further research, this technology holds immense potential for aligning patient expectations with realistic surgical possibilities, fostering more effective communication between patient and surgeon regarding desired goals.

Moreover, intraoperative navigation systems further enhance precision during the actual surgery. These systems, often likened to a GPS for the surgeon, track the exact position of surgical instruments in real-time relative to the patient’s anatomy and the pre-planned virtual model. This continuous validation of instrument placement and bone repositioning ensures that the surgery adheres precisely to the virtual plan, even in complex cases with distorted or atypical anatomy. The amalgamation of advanced imaging, virtual surgical planning, and intraoperative navigation systems not only significantly improves the accuracy, safety, and efficiency of facial feminization surgery but also substantially enhances the predictability of outcomes, ultimately leading to higher patient satisfaction and profoundly natural-looking results.

A young girl lying on a medical bed with her eyes covered by gauze and tape, surrounded by surgical lights.

Intraoperative Considerations and Challenges in Complex Feminization Procedures

The execution of complex facial feminization surgery, particularly for patients with significant skeletal variations or previous interventions, presents a unique and demanding set of intraoperative considerations and challenges. These circumstances require not only exceptional surgical skill but also considerable adaptability and a deep understanding of anatomical variations. Unlike more routine aesthetic procedures, these cases often involve highly altered or atypical anatomy, which can obscure normal surgical landmarks and significantly increase the complexity of dissection and bone manipulation. The surgeon must be prepared to navigate unexpected findings and adjust the pre-planned strategy in real-time while maintaining the overarching feminization goals.

One of the most critical challenges lies in the meticulous management and preservation of vital neurovascular structures. The facial nerve and its numerous delicate branches, which control facial expressions, are particularly vulnerable during extensive soft tissue dissection and bone reshaping in regions like the midface and jawline. Similarly, branches of the trigeminal nerve, responsible for sensation, can be at risk, potentially leading to temporary or permanent numbness or altered sensation. Precise knowledge of anatomical variations in nerve pathways, which can occur as highlighted by Alraddadi (2021), coupled with meticulous surgical technique, is crucial to preserve nerve function and minimize the risks of facial paralysis or sensory deficits. The judicious use of intraoperative nerve monitoring can serve as an invaluable tool, providing real-time feedback to help identify and protect these delicate structures during complex dissections.

Vascular concerns are also heightened in reconstructive and extensive feminization cases. Tissues that have been scarred from previous surgeries or subjected to trauma may have a compromised blood supply, increasing the risk of flap necrosis, delayed wound healing, or excessive intraoperative bleeding. Careful, controlled dissection, gentle tissue handling, and meticulous hemostasis are paramount to preserve the delicate vascular network. When large bone grafts are utilized, ensuring adequate vascularity of the recipient bed is absolutely critical for graft survival and successful integration. In situations with severely compromised blood supply, specialized techniques such as vascularized bone grafts, where a segment of bone is transplanted along with its nourishing artery and vein and reconnected using microsurgical techniques, may be required. This represents the pinnacle of reconstructive artistry but also significantly increases operative time and technical demands.

Managing inherent anatomical variations is another significant hurdle. As Alraddadi (2021) emphasizes, anatomical variations are normal presentations but can greatly influence clinical practice outcomes. No two cases of facial skeletal deficiency or dimorphism are identical, requiring surgeons to adapt their techniques dynamically to the unique presentation. While advanced virtual surgical planning provides a robust roadmap, the reality of the operating field can still present unforeseen anatomical deviations. This necessitates a surgeon with extensive experience in craniofacial and reconstructive surgery who can make informed, rapid decisions, potentially deviating from the initial plan if necessary, without compromising safety or aesthetic objectives. Factors such as unexpected bone density, the presence of fibrous scar tissue, or unusual sinus anatomy can all influence the precise execution of osteotomies and the stability of plate fixation strategies. Furthermore, achieving precise symmetry and harmonious contours in a face that may already be distorted requires continuous intraoperative assessment, often involving repeated visual inspection and palpation to ensure that bone reductions, advancements, or augmentations are balanced and aligned with the feminizing goals. The sheer volume and intricacy of combined bone and soft tissue work can lead to prolonged operative times, which in turn increases the risks associated with general anesthesia and overall patient recovery. Therefore, a highly coordinated surgical team, efficient instrumentation, and judicious patient selection based on a thorough preoperative assessment are essential prerequisites for successfully navigating these intraoperative complexities and achieving optimal, safe, and transformative results.

Post-Operative Recovery and Long-Term Management: Nurturing the Transformation

The post-operative phase following comprehensive facial feminization surgery, particularly when complex bone and soft tissue modifications have been performed, is a critical period that demands meticulous care, patience, and a well-structured management plan. The recovery timeline for extensive procedures is typically more protracted and can be more intense compared to standard aesthetic interventions, given the significant degree of bone manipulation, tissue reshaping, and potential for extensive swelling and bruising. Patients must be thoroughly prepared for this journey, understanding that the immediate post-operative appearance will evolve considerably over weeks and months.

Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort. Swelling is an almost universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week after surgery, gradually subsiding over several weeks to months. Full resolution of residual swelling, especially in areas of significant bone work or grafting, can take up to a year or even longer for the final contours to fully emerge. Bruising will similarly resolve, usually within 2 to 4 weeks, with color changes from purplish-black to greenish-yellow before fading completely. Pain management is crucial and is typically achieved through a combination of prescribed analgesia, anti-inflammatory medications, and diligent application of cold compresses, which help to minimize swelling and alleviate discomfort. Hospitalization may extend for several days, particularly after complex osteotomies or large graft placements, allowing for close monitoring of vital signs, early detection of potential complications such as hematoma or infection, and effective pain control.

Specific post-operative care instructions are tailored to the procedures performed. For individuals undergoing jaw or chin osteotomies, a soft or liquid diet is often prescribed for several weeks to prevent undue stress on the healing bone segments and intraoral incisions. Meticulous oral hygiene, often involving antimicrobial mouth rinses, is paramount to prevent infection in the oral cavity. Activity restrictions are stringent in the initial weeks; patients are advised to avoid strenuous activities, heavy lifting, and anything that might elevate blood pressure or stress the healing facial structures. Gradually, activity levels are increased as recovery progresses and clearance is given by the surgical team. Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce swelling. Physical therapy or gentle lymphatic drainage massages may also be recommended in later stages of recovery to help expedite the resolution of swelling and improve soft tissue suppleness.

Complex reconstructive procedures inherently carry potential complications beyond those of standard aesthetic surgery. While surgeons employ meticulous techniques to mitigate these, awareness and diligent monitoring are essential. Graft resorption, where a portion of transplanted autologous bone may be reabsorbed by the body, can lead to a partial loss of contour or volume, occasionally necessitating revision. For alloplastic implants, potential risks include implant exposure or infection, which can compromise implant integration and in severe cases require removal. Non-union or malunion of osteotomies, though rare, can occur if bone segments fail to heal properly, potentially leading to persistent asymmetry or functional issues, often requiring further surgical correction. Nerve damage, despite careful intraoperative preservation efforts, can manifest post-operatively as persistent numbness, altered sensation, or, in rare instances, motor weakness, particularly affecting facial expressions. Long-term stability expectations are a crucial aspect of patient counseling. While the extensive bone reshaping in feminization surgery provides a stable and lasting foundation, facial structures continue to undergo natural aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. Regular follow-up appointments are therefore essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction. A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey.

Functional and Aesthetic Restoration: Comprehensive Outcomes Beyond Appearance

The overarching goal of advanced facial feminization surgery, particularly when addressing severe facial skeletal deficiencies stemming from congenital anomalies, trauma, or complex developmental variations, extends far beyond mere aesthetic transformation. While the visual alignment of external features with an individual’s gender identity is paramount, equally significant is the comprehensive restoration of optimal facial function. For patients presenting with pre-existing functional impairments, the journey through feminization surgery offers a profound opportunity to simultaneously regain or improve vital physiological capabilities, thereby enhancing their overall quality of life and facilitating more seamless social interaction.

Functional impairments in such complex cases can be diverse and significantly impact daily life. These may include difficulties with mastication (chewing) due to severe jaw misalignment or temporomandibular joint (TMJ) dysfunction, which can be addressed through precise mandibular and maxillary osteotomies that not only feminize the jawline but also restore proper dental occlusion. Compromised vision or ocular discomfort arising from orbital dystopia (misplaced eyes) or malposition of the infraorbital rim can be alleviated through meticulous reconstruction of the orbital region, providing better support and protection for the eyes. Impaired breathing, often a consequence of severe nasal obstruction, septal deviation, or midface hypoplasia, can be corrected through comprehensive rhinoplasty that improves nasal airflow while simultaneously creating a more delicate nasal appearance (Barnett et al., 2023). Speech impediments, occasionally arising from abnormal oral or pharyngeal anatomy related to skeletal discrepancies, can also see improvements following corrective osseous surgery in the jaw and midface.

Therefore, a truly successful facial feminization outcome in these advanced cases is defined by the synergistic achievement of both highly feminine aesthetics and robust, enduring functional recovery. The intricate bone work, encompassing complex osteotomies, the strategic use of autologous bone grafts, and custom implant placements, plays a direct and foundational role in re-establishing proper skeletal support for these critical facial structures. For instance, correcting mandibular discrepancies not only sculpts a softer, more tapered jawline but critically restores proper dental occlusion and chewing efficiency, enabling better nutrition and comfort. Reconstructing the orbital rims and midface enhances visual field and provides improved protection for the eyes, while thoughtful rhinoplasty, beyond creating a more delicate nasal appearance, actively improves nasal airflow and respiratory function (Barnett et al., 2023). The integration of precise soft tissue management techniques further refines both outcomes. Accurate redraping of the skin, muscle, and fat over the newly contoured skeletal framework ensures natural-looking transitions and minimizes visible surgical evidence, contributing to a harmonious appearance that moves naturally with expression. Autologous fat grafting, beyond its aesthetic benefits of adding feminine volume to areas like the cheeks and lips, can also significantly improve local tissue quality, camouflage minor irregularities, and potentially enhance vascularity, further contributing to durable functional and aesthetic integration.

The meticulous preoperative planning involved, utilizing high-resolution 3D virtual surgical planning and intraoperative navigation, contributes profoundly to achieving this dual objective. By precisely defining bone movements, predicting soft tissue redraping, and mapping graft placements, surgeons can optimize both the feminizing aesthetic and the structural integrity necessary for restored function. Patient-reported outcome measures consistently demonstrate that individuals undergoing comprehensive facial feminization experience significant psychological benefits, including a profound reduction in gender dysphoria, improved self-esteem, and enhanced body image (Barnett et al., 2023). However, in reconstructive cases, these psychological gains are often compounded by the transformative impact of regaining lost or never-had functions, which further enhances overall quality of life, fosters greater independence, and facilitates more confident integration into society. The remarkable ability of modern reconstructive feminization surgery to simultaneously sculpt a face that is aesthetically feminine and fully functional represents the pinnacle of contemporary craniofacial and gender-affirming surgical practice, offering truly life-changing results for those facing the most profound anatomical challenges.

Selecting a Specialist: The Critical Choice for Complex Feminization

The decision to undergo advanced reconstructive facial feminization surgery for severe facial skeletal deficiencies is one of monumental significance, necessitating the selection of a highly specialized and exceptionally experienced surgeon. The inherent complexity of these cases demands a level of expertise that extends far beyond the scope of a general plastic surgeon or even one whose practice is solely focused on aesthetic feminization. Therefore, the paramount importance of choosing a surgeon with dual proficiency—deeply rooted in both routine facial feminization procedures and intricate maxillofacial reconstruction—cannot be overstated. Such a specialist possesses an unparalleled understanding of complex craniofacial anatomy, the biomechanics of bone remodeling and healing, and advanced reconstructive techniques, including microvascular surgery when vascularized grafts are indicated for compromised tissues (Dr. MFO, 2025a).

These highly specialized surgeons are adept at managing large skeletal defects, correcting severe congenital or acquired asymmetries, and precisely reconstructing compromised facial units. Crucially, this dual expertise means the surgeon not only understands how to create aesthetically pleasing feminine contours but also possesses the foundational knowledge and technical skill to rebuild a stable and functional facial framework from a significantly compromised or deficient starting point. This includes profound proficiency in performing complex osteotomies with precision, implementing advanced bone grafting techniques using either autologous tissue or customized alloplastic materials, and the expert deployment of custom implants to restore lost volume and projection. Their training often encompasses a blend of plastic surgery, oral and maxillofacial surgery, and dedicated craniofacial fellowship training, providing a robust skill set for the most challenging anatomical situations.

Furthermore, an ideal reconstructive feminization surgeon will be exceptionally well-versed in utilizing cutting-edge technologies that enhance precision and safety. This includes a mastery of high-resolution 3D virtual surgical planning (VSP) systems, the ability to design and utilize custom surgical guides and drilling templates, and proficiency with intraoperative navigation systems (Barnett et al., 2023). Their capacity to leverage these advanced tools ensures optimal surgical accuracy, minimizes potential risks, and maximizes the predictability of outcomes, particularly in scenarios characterized by distorted or atypical anatomy. Beyond technical skill, the most effective specialist will demonstrate a profoundly patient-centered approach. This involves engaging in thorough and empathetic consultations to fully understand the individual’s unique goals, specific concerns, and psychological needs. They are committed to providing realistic expectations regarding the surgical process, the nuances of recovery, and the potential long-term outcomes, which is especially vital given the inherent complexities and extended recovery periods of reconstructive cases. Verifying the surgeon’s credentials, including board certification in relevant surgical specialties and a comprehensive portfolio demonstrating successful outcomes in challenging reconstructive cases, is an essential step for prospective patients. Consulting with a surgeon who works within or collaborates with a multidisciplinary team, potentially including oral surgeons, orthodontists, and mental health professionals, further ensures a holistic and comprehensive approach to care, addressing all facets of the patient’s well-being. Ultimately, the selection of such a highly experienced and uniquely qualified surgeon is the single most critical factor in achieving safe, functional, aesthetically transformative, and enduring results in advanced reconstructive facial feminization surgery, providing patients with the confidence that their complex needs are in expert hands.

A black and white portrait of a woman with smooth, straight hair and striking features, looking directly at the camera with a serious expression.

Conclusion: The Critical Role of Individualized Anatomical Strategy

The journey through facial feminization surgery is a profoundly personal and meticulously orchestrated process, uniquely shaped by each individual’s distinct facial anatomy. As this comprehensive exploration has underscored, achieving natural, harmonious, and enduring results in feminization requires far more than a generalized approach; it demands an intricate understanding of the subtle and overt differences in skeletal and soft tissue structures that define facial gender. The ability to precisely assess, plan, and execute surgical modifications based on a patient’s unique biological blueprint is the hallmark of truly transformative and successful outcomes. We have delved into how variations in the frontal bone and orbital rims dictate specific forehead contouring techniques, how midface projection influences strategies for cheek augmentation or reduction, and how the intricate cartilaginous and bony framework of the nose guides delicate rhinoplasty procedures. Similarly, the diverse forms of the mandible and chin necessitate highly individualized jawline and chin reshaping, while the laryngeal prominence requires careful reduction. Each of these regional modifications, when viewed in isolation, contributes to feminization, but their true power emerges from their synergistic integration.

The advancements in preoperative planning, particularly the integration of high-resolution 3D imaging and virtual surgical planning systems, have revolutionized the field, allowing surgeons to create highly detailed blueprints of the desired transformation. This technological synergy enhances precision, minimizes risks, and optimizes predictability, transitioning complex cases from challenging guesswork to precisely engineered solutions. Intraoperative challenges, such as the meticulous preservation of neurovascular structures and the dynamic adaptation to anatomical variations, underscore the demanding nature of these procedures and highlight the critical role of profound surgical experience. Furthermore, the post-operative recovery, often protracted and intensive, requires a comprehensive and patient-centered management plan to ensure optimal healing and long-term stability. Beyond the aesthetic alterations, successful facial feminization inherently encompasses the restoration or improvement of vital facial functions, addressing potential impairments related to mastication, vision, and breathing. This dual emphasis on form and function ensures that the patient not only achieves an external appearance congruent with their identity but also experiences a significant enhancement in overall quality of life.

The selection of a highly specialized surgeon, one possessing deep expertise in both facial feminization and complex maxillofacial reconstruction, stands as the single most critical decision for individuals embarking on this journey. Their unique skill set, combining artistic vision with a profound anatomical understanding, is indispensable for navigating the intricacies of advanced cases and delivering results that are both safe and aesthetically profound. Ultimately, facial feminization surgery, particularly when tailored to the individual’s unique anatomy, is a powerful affirmation of identity, fostering self-confidence and providing a deeper sense of authenticity. It is a testament to the continuous evolution of surgical science and artistry, offering life-changing possibilities for those seeking harmony between their inner self and outer presentation. The ongoing commitment to precision, personalized care, and comprehensive outcomes will continue to define this vital and transformative field, providing hope and tangible results for countless individuals.

Frequently Asked Questions

Why is individual facial anatomy so important in planning facial feminization surgery?

Individual facial anatomy is crucial because every face is unique, with varying bone structures and soft tissue distributions. A personalized surgical strategy, tailored to these specific anatomical nuances, ensures the most natural, harmonious, and effective feminization outcomes, as opposed to a generic approach.

What role do 3D imaging and virtual surgical planning play in customizing facial feminization procedures?

3D imaging, such as CT scans, provides a detailed blueprint of the patient’s skeletal and soft tissue architecture. Virtual surgical planning software allows surgeons to simulate procedures, precisely measure modifications, and design custom guides, significantly enhancing surgical precision, safety, and predictability.

How do bone modifications and soft tissue procedures interact synergistically in facial feminization?

Bone modifications (e.g., forehead contouring, jaw reduction) provide the foundational changes, redefining the facial framework. Soft tissue procedures (e.g., rhinoplasty, cheek augmentation, lip lifts) then refine these contours, add volume, and enhance expressions. Their synergistic combination ensures a cohesive, balanced, and naturally feminine appearance.

What are some of the critical challenges faced during complex facial feminization surgeries?

Challenges include meticulous preservation of vital neurovascular structures (like facial nerves), managing compromised blood supply in scarred tissues, adapting to unexpected anatomical variations, and ensuring precise symmetry. These demand exceptional surgical skill and adaptability.

What kind of recovery can be expected after extensive facial feminization surgery?

Recovery from extensive procedures typically involves significant swelling, bruising, and discomfort, which gradually subside over weeks to months. Full resolution of swelling and bone healing can take up to a year or more. Adherence to post-operative care, including rest, head elevation, and a soft diet, is crucial.

Beyond aesthetics, what other benefits does facial feminization surgery offer?

Beyond aesthetic alignment, facial feminization surgery can significantly improve or restore vital facial functions such as mastication (chewing), vision, and breathing, especially in cases of pre-existing skeletal deficiencies. This dual focus enhances overall quality of life, reduces psychological distress, and fosters greater social confidence.

What qualifications should one look for in a surgeon for complex facial feminization?

For complex cases, seek a surgeon with dual proficiency in both routine facial feminization and intricate maxillofacial reconstruction. This specialist should have extensive experience, board certification in relevant specialties, a strong portfolio of results, and expertise in advanced technologies like 3D virtual surgical planning.

Bibliography

  • Alraddadi, A. (2021). Literature Review of Anatomical Variations: Clinical Significance, Identification Approach, and Teaching Strategies. Cureus, 13(4), e14451. https://pmc.ncbi.nlm.nih.gov/articles/PMC8117423/
  • Barnett, S. L., Choe, J., Aiello, C., & Bradley, J. P. (2023). Facial Feminization Surgery: Anatomical Differences, Preoperative Planning, Techniques, and Ethical Considerations. Medicina (Kaunas), 59(12), 2070. https://pmc.ncbi.nlm.nih.gov/articles/PMC10744788/
  • Dr. MFO. (2025a, October 13). Advanced Reconstructive FFS: Surgical Techniques for Severe Facial Skeletal Deficiencies. https://www.dr-mfo.com/advanced-reconstructive-ffs-surgical-techniques/
  • Dr. MFO. (2025b, July 4). Key Anatomical Considerations for Combined Nose and Cheek Procedures in Transgender FFS. https://www.dr-mfo.com/combined-nose-cheek-ffs-anatomical-considerations/
  • Dr. MFO. (2025c, July 10). FFS Procedures: Bone vs. Soft Tissue Modification for Facial Feminization. https://www.dr-mfo.com/ffs-procedures-bone-vs-soft-tissue-modification/

  • Gender Confirmation Center. (n.d.). FFS Surgery Options: Facial Feminization Surgery Procedures: Complete Guide. Retrieved October 24, 2025, from https://www.genderconfirmation.com/ffs-surgery-options/
  • Keojampa, M. (n.d.). FFS Surgery Guide. Retrieved October 24, 2025, from https://www.drkeojampa.com/ffs-surgery-guide/
  • Surgero. (2025, January 6). Facial Feminization Surgery (FFS): Procedures, Process, and Recovery. https://www.surgero.co/blog/facial-feminization-surgery-ffs-procedures-process-and-recovery

Fat Grafting in FFS: Advanced Techniques for Natural Feminine Volume

A close-up image of a person receiving a facial injection from a healthcare professional using a syringe. The individual is wearing gloves and carefully administering the injection near the person's cheek.

Facial Feminization Surgery (FFS) represents a profound journey for individuals seeking to harmonize their outward appearance with their affirmed feminine identity. Within this intricate field, the strategic application of fat grafting has emerged as a cornerstone technique, moving beyond mere volume enhancement to sculpt deeply natural and enduring feminine contours. This advanced surgical approach leverages the body’s own adipose tissue, offering a biologically compatible and aesthetically superior method for reshaping and refining facial features (Feminization Center, 2025). The inherent variability in human facial anatomy necessitates a highly individualized strategy, and fat grafting precisely delivers this bespoke capability, adapting to each patient’s unique architecture rather than imposing a generic ideal.

Historically, facial augmentation often relied on synthetic implants or temporary fillers. However, advancements in fat grafting technology have spurred a significant shift, emphasizing natural tissue utilization (Plasticsurgery.org, 2024). This transition underscores a broader understanding that true feminization requires a nuanced interplay between underlying bone structure and overlying soft tissue, a synergy that fat grafting facilitates with remarkable finesse. It permits surgeons to not only fill hollow areas but also to subtly recontour planes, creating the delicate S-curves and youthful convexity typically associated with feminine aesthetics.

This comprehensive exploration will delve into the advanced surgical techniques that define successful fat grafting in FFS. It will meticulously detail the entire process, starting from the critical selection of donor sites and sophisticated harvesting methods, such as Vaser liposuction, which prioritize cell viability and minimize tissue trauma (Quartz.com.tr, 2025). Furthermore, the discussion will encompass the intricate science of fat processing, exploring techniques like centrifugation and micro-fragmentation (e.g., Lipocube technology) that optimize graft quality and integration (Shauly et al., 2022).

Precision injection strategies are equally vital for achieving natural-looking results, and this guide will examine how micro-cannulas and layered placement techniques enable surgeons to sculpt contours in key facial regions, including the cheeks, temples, and lips. The focus extends beyond immediate post-operative appearance to address the long-term survival and integration of fat grafts within facial tissues, offering insights into factors that influence graft retention and strategies for mitigating complications like asymmetry or overcorrection. Ultimately, this article aims to provide an authoritative perspective on how modern fat transfer techniques, when executed with surgical artistry and a deep understanding of facial aesthetics, contribute to transformative and psychologically affirming outcomes in FFS, offering a pathway to authentic self-expression.

The journey to a more feminine facial appearance is deeply personal, and the choice of surgical techniques reflects this individuality. Fat grafting offers an unparalleled advantage due to its use of autologous tissue, meaning the patient’s own fat is used. Consequently, the risk of allergic reactions or rejection, common with synthetic materials, is virtually eliminated. Moreover, the results tend to be exceptionally natural, not only in feel but also in how they integrate with the body’s natural aging processes.

This natural integration is crucial for maintaining a cohesive appearance over time. When carefully applied, fat grafting results in a soft, supple enhancement that moves harmoniously with facial expressions, avoiding the rigid or artificial look sometimes associated with other augmentation methods (Gender Confirmation Center, 2025).

A black and white photograph of a woman looking upwards with a thoughtful expression, illuminated by soft light from the side.

Understanding Autologous Fat Grafting in Facial Feminization

Autologous fat grafting, often referred to as fat transfer or lipofilling, has become a cornerstone technique within facial feminization surgery. This procedure is fundamental in creating softer, rounder, and more youthful facial contours that align with feminine characteristics (Feminization Center, 2025). The core principle involves relocating a patient’s own fat from one area of the body, where it is often abundant, to specific regions of the face that benefit from increased volume and refined shaping.

For individuals seeking FFS, fat grafting serves multiple critical purposes. Primarily, it softens inherently masculine angularities, such as those found in the jawline or brow, by strategically adding volume to adjacent areas. Furthermore, it restores lost volume, which can be a consequence of natural aging, weight loss, or the effects of testosterone suppression therapy (Gender Confirmation Center, 2025). This volume restoration helps create the desired convexities and smooth transitions characteristic of a feminine face.

Unlike synthetic fillers, which provide temporary enhancement and may require frequent re-treatment, fat grafting offers a durable and often permanent solution. The transferred fat integrates with the surrounding tissues, establishing its own blood supply to remain viable long-term (Gender Confirmation Center, 2025). This biological integration contributes to a more natural feel and appearance, significantly reducing the likelihood of allergic reactions or immunogenic responses because the tissue is native to the patient.

Key facial areas that prominently benefit from fat grafting include the cheeks, temples, and lips. Augmenting the cheeks creates higher, more rounded malar eminences, often contributing to a desirable “heart-shaped” facial contour. Filling hollowed temples softens the upper face, reducing shadows and promoting a smoother transition to the forehead. Moreover, fat transfer to the lips provides a natural plumping effect, enhancing their shape and volume to achieve a more sensual and feminine appearance (Feminization Center, 2025).

Beyond these primary regions, fat grafting can also refine the midface, diminish the appearance of nasolabial folds, and rejuvenate under-eye hollows, all contributing to a more youthful and feminized overall facial balance (Quartz.com.tr, 2025). The versatility of this technique makes it an invaluable tool for surgeons aiming to achieve comprehensive and harmonious facial feminization.

Donor Site Selection and Advanced Harvesting Methods

The initial phase of autologous fat grafting involves the careful selection of a donor site and the precise harvesting of adipose tissue. Optimal outcomes depend heavily on obtaining high-quality, viable fat cells. Common donor sites include areas where fat is naturally abundant and easily accessible, such as the abdomen, flanks, inner thighs, and outer thighs (Shauly et al., 2022). These regions typically provide a sufficient volume of fat for transfer while allowing for a secondary contouring benefit at the donor site itself.

Scientific literature indicates that there is no significant difference in fat harvest weight, volume retention, or cell viability across various donor sites (Shauly et al., 2022). However, the deep layer of subcutaneous fat is often preferred for harvesting due to its higher concentration of mature adipocytes and reduced collection of unwanted debris. Careful selection helps maximize the quality of the harvested fat for successful engraftment.

Advanced Liposuction Techniques for Gentle Harvesting

Modern fat harvesting techniques prioritize minimizing trauma to adipocytes to ensure their viability for transfer. One advanced method is Vaser liposuction, which utilizes ultrasonic energy to gently emulsify fat cells before extraction (Quartz.com.tr, 2025). This process allows for smoother fat removal, reduces damage to surrounding tissues, and ultimately yields higher-quality fat cells that are more likely to survive and integrate at the recipient site. The gentle nature of Vaser liposuction contributes significantly to better healing at the donor site as well.

Another widely adopted approach is manual syringe aspiration, commonly known as the Coleman technique (Shauly et al., 2022). This method employs cannulas of various lengths and calibers with small side ports to carefully disrupt and aspirate fat. The use of low negative pressure with manual syringes or specialized automated systems minimizes the shear stress on fat cells, thereby preserving their integrity. Studies have shown that high negative pressure vacuum liposuction, while quicker for large volumes, can disrupt up to 90% of adipocytes, severely compromising graft viability (Shauly et al., 2022).

Cannula selection is paramount; larger bore cannulas (e.g., 17-gauge) are often preferred for harvesting as they reduce the risk of cellular rupture due to a more laminar flow of fat (Shauly et al., 2022). Maintaining a constant, low speed of suction throughout the process further minimizes shear stress damage. These meticulous harvesting methods are crucial steps in ensuring a robust and viable fat graft for facial feminization.

Donor Site Preparation: Tumescent Technique and Preoperative Care

Donor site preparation is a critical step in optimizing fat harvesting. The tumescent technique is widely used, involving the infiltration of a large volume of dilute anesthetic solution (lidocaine with epinephrine) into the subcutaneous fat (Shauly et al., 2022). This solution serves multiple purposes: it anesthetizes the area, constricts blood vessels to minimize bleeding, and facilitates easier fat extraction by swelling and firming the tissue. While lidocaine can negatively affect stem cell viability with prolonged exposure, modern tumescent solutions aim for a balance, often including other anesthetics to mitigate this risk (Shauly et al., 2022).

Beyond local preparation, overall patient health plays a role in graft viability. Some practices recommend preoperative nutritional supplementation and hyperbaric oxygen therapy to enhance local tissue oxygen tension (Shauly et al., 2022). This proactive approach aims to improve the graft’s ability to survive and integrate by ensuring adequate oxygenation and nutrient supply at both the donor and recipient sites, thereby maximizing graft retention and overall patient outcome.

A black and white photograph of a woman looking upwards with her eyes closed, wearing large earring, and dressed in a sweater.

Advanced Fat Processing for Enhanced Graft Viability

Once harvested, the adipose tissue undergoes a critical processing phase designed to purify and concentrate viable fat cells while removing unwanted contaminants. This step is essential for maximizing graft survival and achieving smooth, natural results (Shauly et al., 2022). Contaminants such as free oil from ruptured fat cells, cellular debris, red blood cells, and inflammatory agents can all compromise graft integration and lead to poor retention or complications (Shauly et al., 2022).

Centrifugation: The Gold Standard for Separation

Centrifugation is widely regarded as the gold standard for fat processing due to its ability to precisely separate components based on density. In this technique, harvested lipoaspirate is spun at a specific speed (e.g., 3000 rpm for 3 minutes), causing it to stratify into distinct layers: oil (top), viable fat (middle), and aqueous solution (bottom) (Shauly et al., 2022). Surgeons then carefully extract the middle, viable fat layer, which is rich in intact adipocytes and adipose-derived stem cells, for injection. This method ensures the highest possible concentration of usable fat cells, contributing significantly to graft survival.

Filtration and Washing: Removing Impurities

Filtration methods efficiently remove contaminants and inflammatory components while preserving viable mature adipocytes and the crucial adipose-derived mesenchymal stem cells (Shauly et al., 2022). Modern automated filtration systems, often integrated into closed systems, can also incorporate a washing step using normal saline or lactated Ringer’s solution. This dual approach helps eliminate nonviable cells and proinflammatory substrates that can be detrimental to graft survival. For smaller volumes, cotton gauze filtration can be used to concentrate the mesenchymal component and absorb excess tumescent solution (Shauly et al., 2022).

Sedimentation: A Gentle Separation Method

Sedimentation is a less traumatic, gravity-based separation technique where lipoaspirate is allowed to settle into layers over time (Shauly et al., 2022). While it is effective at separating oil and aqueous components, it may be less efficient than centrifugation or filtration in removing all inflammatory mediators. However, its gentle nature can be advantageous for preserving fat cell integrity, especially in systems that promote accelerated separation, such as vibrating tabletop stands.

Lipocube Technology: Micro-fragmentation for Optimal Integration

Beyond traditional processing, innovative technologies like Lipocube further enhance graft viability and integration (Quartz.com.tr, 2025). Lipocube micro-fragments the processed fat cells into smaller, more uniform particles. This micro-fragmentation increases the surface area for nutrient diffusion and improves vascularization, allowing the transplanted fat to establish a blood supply more efficiently at the recipient site. Consequently, Lipocube-processed fat is particularly effective in creating smooth, natural, and long-lasting results, often reducing the need for repeat sessions due to improved graft retention.

Precision Injection Strategies for Natural Feminine Contours

The successful engraftment of processed fat relies heavily on meticulous injection techniques that ensure uniform distribution, adequate oxygenation, and harmonious contouring. Surgeons employ precision strategies to place fat in specific facial compartments, creating soft, natural-looking volume that complements other feminizing procedures.

Micro-Cannulas and Layered Placement

Injection of fat grafts is performed using fine micro-cannulas, which minimize trauma to the recipient site and reduce the risk of bleeding and bruising (Gender Confirmation Center, 2025). These cannulas are significantly smaller in gauge than harvesting cannulas, typically around 1mm for facial applications, and are designed with a blunt tip and a single port at the distal end. This design allows for controlled, precise delivery of fat in small aliquots.

A crucial technique is layered placement, also known as microfat grafting or fat layering. Instead of injecting large boluses of fat, surgeons create multiple tunnels and deposit tiny, evenly distributed amounts of fat in various tissue planes (Gender Confirmation Center, 2025). This fanning technique maximizes the surface area of contact between the fat graft and the recipient tissue, which is vital for plasmatic imbibition—the initial process where the graft absorbs nutrients from the surrounding environment (Shauly et al., 2022). This approach ensures that individual fat cells receive adequate oxygen and nutrients, promoting their survival and subsequent neovascularization.

Injecting fat only on withdrawal of the cannula helps the fat settle into natural tissue planes and prevents overcorrection or uneven distribution (Shauly et al., 2022). This meticulous approach is key to achieving smooth transitions and avoiding palpable irregularities post-operatively.

Targeted Feminizing Effects in Key Facial Regions

Strategic fat injection in specific facial areas yields distinct feminizing effects:

  • Cheeks: Augmenting the cheeks creates a fuller, more rounded, and higher malar projection, characteristic of a youthful feminine appearance. This softens the midface and contributes to a desirable heart-shaped facial contour (Quartz.com.tr, 2025).
  • Temples and Forehead: Fat grafting to hollowed temples or the forehead region helps create a smoother, more convex profile, reducing masculine shadows and softening the upper face (Quartz.com.tr, 2025). Importantly, fat grafting to the forehead can serve as an adjuvant technique to bone contouring or even an alternative to frontal bone osteotomy in carefully selected cases, potentially avoiding the higher complication profile and hardware placement associated with more invasive procedures (Sluiter et al., 2024).
  • Lips: Fat transfer to the lips enhances volume and redefines the vermilion border, creating a plumper, more sensual, and feminine shape (Quartz.com.tr, 2025). This can also adjust the distance between the upper lip and the base of the nose for a more feminine proportion (Omnicosmetic.com, 2025).
  • Midface: Restoring volume in the midface diminishes hollow or angular contours, improving overall facial balance and creating a softer aesthetic (Quartz.com.tr, 2025).
  • Jawline and Chin: While skeletal reduction addresses prominent bone, fat grafting can soften strong jawline contours and create a more tapered, less prominent chin, contributing to a smoother V-line shape (Quartz.com.tr, 2025).
  • Nasolabial Folds and Under-Eye Hollows: Filling these areas with fat rejuvenates a tired appearance and smooths out prominent folds, further enhancing a youthful feminine look (Quartz.com.tr, 2025).

Surgeons typically overfill the recipient areas by approximately 20-50% to account for the natural absorption of a portion of the transferred fat in the initial months following surgery (Plasticsurgery.org, 2024; Gender Confirmation Center, 2025; Shauly et al., 2022). This calculated overcorrection aims to achieve the desired long-term volume and contour after the initial post-operative swelling subsides and some graft reabsorption occurs.

A young woman with long brown hair smiling brightly at the camera, set against a blurred green outdoor background.

Fat Graft Survival and Long-Term Integration in Facial Tissues

The long-term success of fat grafting in facial feminization hinges on the survival and stable integration of the transplanted adipocytes within the recipient tissues. This complex biological process is influenced by numerous factors, ranging from the initial handling of the fat to the characteristics of the recipient site itself (Shauly et al., 2022).

Mechanisms of Graft Survival

Initially, within the first 48 to 72 hours post-transplantation, fat grafts survive primarily through a process called plasmatic imbibition (Shauly et al., 2022). During this phase, the transplanted fat cells absorb nutrients and oxygen directly from the surrounding interstitial fluid of the recipient site. This early nutritive support is critical. Following imbibition, a more permanent blood supply must develop, a process known as neovascularization, which typically progresses at approximately 1mm per day (Shauly et al., 2022).

The concept of “cell survival theory” posits that the final volume of a fat graft is directly dependent on the number of adipocytes that survive this initial period and successfully establish a new blood supply (Shauly et al., 2022). However, mature adipocytes are fragile and susceptible to trauma, hypoxia (lack of oxygen), and desiccation (drying out). Preadipocytes, which are also present in the fat graft, are more resilient to ischemic conditions and play a vital role in long-term graft survival by differentiating into new fat cells (Shauly et al., 2022).

Role of Stem Cells and Stromal Vascular Fraction

Adipose tissue is a rich source of adult stem cells, particularly adipose-derived stem cells (ASCs), which are part of the stromal vascular fraction (SVF) (Shauly et al., 2022). The SVF also contains preadipocytes, fibroblasts, endothelial cells, and other cells that contribute to the regenerative potential of the fat graft. While direct isolation and transplantation of SVF is not yet widely approved, the goal of optimal fat processing is to maximize the concentration of these critical components within the transferred fat.

ASCs promote graft survival through their paracrine effects, secreting growth factors such as vascular endothelial growth factor (VEGF), hepatocyte growth factor, and fibroblast growth factor (Shauly et al., 2022). These factors stimulate neovascularization, increase local oxygen tension, and contribute to the overall health and integration of the fat graft. Therefore, techniques that preserve a higher concentration of SVF components are believed to enhance long-term graft retention.

Expected Retention Rates and Influencing Factors

Despite meticulous techniques, a portion of the transferred fat will undergo reabsorption. Typical retention rates for fat grafting range from 50% to 80% (Plasticsurgery.org, 2024; Shauly et al., 2022). Some studies indicate that up to 30% of the fat may be reabsorbed within the first year (Quartz.com.tr, 2025). This variability is influenced by several factors:

  • Harvesting and Processing Techniques: Minimizing trauma during liposuction and optimizing processing (e.g., centrifugation, filtration) helps preserve adipocyte viability (Shauly et al., 2022).
  • Injection Technique: Injecting small aliquots in multiple layers and avoiding excessive interstitial pressure maximizes oxygenation and nutrient diffusion, preventing central necrosis of larger fat deposits (Shauly et al., 2022).
  • Recipient Site Characteristics: Well-vascularized recipient sites with good oxygen tension support better graft survival. Areas with significant scarring or poor blood supply may have lower retention rates.
  • Postoperative Care: Avoiding compression on grafted areas is crucial for allowing optimal blood flow and integration (Shauly et al., 2022). Patients are often advised against direct pressure for several weeks post-surgery (Gender Confirmation Center, 2025).
  • Patient Factors: Individual metabolism, weight stability, and overall health can also affect long-term graft survival (Plasticsurgery.org, 2024). Significant weight loss after surgery can jeopardize graft survival, as the transferred fat cells behave like native fat cells and can shrink with overall body fat reduction.

While the goal is long-lasting results, patients should understand that the final contours may take several months to fully stabilize as swelling subsides and some fat reabsorption occurs (Plasticsurgery.org, 2024; Omnicosmetic.com, 2025). In some cases, touch-up sessions may be considered after the initial healing period to achieve optimal aesthetic outcomes (Quartz.com.tr, 2025; Gender Confirmation Center, 2025).

Minimizing Complications and Ensuring Predictable Outcomes

While fat grafting is a generally safe procedure with many advantages, surgeons must remain vigilant about potential complications and employ strategies to minimize their occurrence. Achieving predictable and satisfying outcomes requires not only technical skill but also a deep understanding of facial anatomy and the biological behavior of fat grafts (Gender Confirmation Center, 2025).

Addressing Asymmetry and Overcorrection

One of the primary aesthetic concerns in facial fat grafting is the potential for asymmetry or overcorrection. Asymmetry can occur if the fat does not settle evenly, or if there are inherent differences in how each side of the face responds to the graft (Gender Confirmation Center, 2025). Overcorrection, or injecting too much fat, can lead to an unnatural or “puffy” appearance. To mitigate these risks, surgeons rely on meticulous preoperative planning, often utilizing 3D imaging to precisely map out the desired volume and contour adjustments.

During the injection phase, the micro-cannula and layered placement technique are crucial. Delivering small, uniform aliquots of fat across multiple planes allows for gradual and controlled augmentation, reducing the likelihood of noticeable irregularities. Furthermore, understanding the expected absorption rate (often around 30-50%) enables surgeons to strategically overfill the area initially, anticipating the eventual reduction in volume to achieve the desired long-term result (Plasticsurgery.org, 2024; Shauly et al., 2022). This calculated approach helps prevent undercorrection and reduces the need for frequent touch-up sessions.

Managing Fat Necrosis and Other Surgical Risks

Fat necrosis, where a portion of the transplanted fat fails to survive, is a potential complication. This can result in lumps, irregularities, or a partial loss of the feminizing effect (Gender Confirmation Center, 2025). Factors contributing to fat necrosis include excessive trauma during harvesting or injection, overcrowding of fat cells leading to insufficient oxygenation, or compromised blood supply at the recipient site. Strategies to minimize fat necrosis include:

  • Gentle Harvesting: Techniques like Vaser liposuction or manual syringe aspiration with appropriate cannula sizes reduce damage to fat cells (Quartz.com.tr, 2025; Shauly et al., 2022).
  • Optimal Processing: Centrifugation or filtration removes non-viable components and concentrates healthy fat cells, improving their chances of survival (Shauly et al., 2022).
  • Micro-Injection Technique: Injecting small, evenly dispersed aliquots ensures better contact with surrounding tissues and improved nutrient diffusion (Shauly et al., 2022).
  • Avoiding Compression: Post-operatively, direct pressure on grafted areas is avoided to prevent compromise of the delicate blood supply to the newly transferred fat (Gender Confirmation Center, 2025; Shauly et al., 2022).

Like any surgical procedure, fat grafting also carries general risks such as bleeding, infection, and temporary numbness or altered sensation (Gender Confirmation Center, 2025; Omnicosmetic.com, 2025). However, serious complications are rare when performed by a highly skilled, board-certified surgeon in an accredited facility. Adherence to strict sterile protocols, meticulous surgical technique, and comprehensive post-operative care instructions are paramount for minimizing these risks.

Importance of Surgeon Expertise and Patient Counseling

The selection of an experienced surgeon is perhaps the most critical factor in minimizing complications and achieving successful outcomes. A specialist with extensive experience in FFS and fat grafting understands the nuances of facial anatomy, the behavior of fat grafts, and how to effectively integrate this technique with other feminizing procedures (Gender Confirmation Center, 2025; Drweinfeld.com, 2023). Their expertise ensures proper planning, precise execution, and appropriate management of any unforeseen challenges.

Thorough patient counseling is equally vital. Surgeons must establish realistic expectations regarding the procedure, recovery, and long-term results. Patients should be informed about the potential for swelling, bruising, and the gradual evolution of final contours over several months (Omnicosmetic.com, 2025). Open communication helps patients understand the process, reduces anxiety, and fosters satisfaction with their transformative journey.

Comparison: Autologous Fat Grafting Versus Synthetic Dermal Fillers

The choice between autologous fat grafting and synthetic dermal fillers for facial augmentation is a significant consideration in feminization. While both aim to restore volume and refine contours, they differ fundamentally in their material, longevity, and potential implications. Understanding these distinctions is crucial for informed decision-making.

Advantages of Autologous Fat Grafting

  • Natural Material: Fat grafting uses the patient’s own tissue, eliminating the risk of allergic reactions or rejection by the body (Feminization Center, 2025; Gender Confirmation Center, 2025). This biological compatibility is a major advantage.
  • Long-Lasting/Permanent Results: Once successfully integrated and vascularized, fat grafts are generally considered permanent. While some initial reabsorption occurs, the surviving fat cells can last for many years, often for the patient’s lifetime (Gender Confirmation Center, 2025; Plasticsurgery.org, 2024). This reduces the need for repeated treatments and associated costs over time.
  • Natural Look and Feel: Autologous fat integrates seamlessly with existing tissues, providing a soft, supple, and natural feel that moves harmoniously with facial expressions. This avoids the sometimes firmer or more palpable texture of synthetic implants or dense fillers (Plasticsurgery.org, 2024).
  • Improved Skin Quality: Fat grafts contain adipose-derived stem cells and growth factors that can enhance the quality, texture, and elasticity of the overlying skin, offering a rejuvenation benefit beyond just volume addition (Gender Confirmation Center, 2025; Shauly et al., 2022).
  • Dual Benefit: The harvesting process, typically liposuction, simultaneously provides a contouring benefit to the donor area (e.g., abdomen, thighs), effectively combining two procedures into one (Feminization Center, 2025).

Considerations and Limitations of Synthetic Dermal Fillers

  • Temporary Nature: Most dermal fillers, such as hyaluronic acid-based products, offer temporary results, typically lasting from several months to a couple of years, depending on the type and location of injection (Feminization Center, 2025). This necessitates periodic touch-ups and ongoing maintenance costs.
  • Synthetic Composition: Fillers are composed of various synthetic or laboratory-derived substances (e.g., hyaluronic acid, calcium hydroxylapatite) (Feminization Center, 2025). While generally safe, they carry a small risk of allergic reactions or foreign body granuloma formation in some individuals.
  • Limited Volume: Fillers are typically used for smaller, more precise volume enhancements or to target fine lines and wrinkles. Achieving significant volume restoration across multiple facial areas would require a large quantity of filler, potentially leading to a less natural appearance and higher cost.
  • Potential Complications: Although rare, serious complications associated with dermal fillers can include infection, nodule formation, persistent swelling, and vascular complications such as tissue necrosis or even blindness if injected intravascularly (Shauly etal., 2022). Litigation cases reveal a significant percentage of patients requiring antibiotic treatment for inflammation (Shauly et al., 2022).
  • Cost: While the upfront cost of a single filler treatment may be lower than fat grafting, the need for repeated sessions over time can make fillers more expensive in the long run for sustained results.

In the context of FFS, fat grafting is often the preferred choice for foundational, long-term volume restoration and broad contouring due to its natural, permanent results and regenerative qualities. Dermal fillers may still have a role for patients seeking temporary enhancements, minor refinements, or as a non-surgical alternative during early stages of transition or for those not yet ready for surgery (The Spiegel Center, 2023; Omnicosmetic.com, 2025). However, for comprehensive and lasting feminine facial sculpting, autologous fat grafting presents a superior and more biologically integrated solution.

Integrating Fat Grafting into a Holistic Feminization Strategy

Achieving truly transformative and harmonious facial feminization rarely relies on a single procedure; instead, it involves a multi-layered, integrated approach that addresses both skeletal and soft tissue characteristics. Fat grafting plays an indispensable role as a crucial component of this holistic strategy, working synergistically with bone restructuring and cartilage refinement to create a cohesive and naturally feminine aesthetic (Dr-mfo.com, 2025).

Synergy with Bone Restructuring

Bone restructuring procedures, such as forehead contouring, jaw reduction, and chin reshaping, lay the fundamental framework for a feminine face. These interventions address the most significant sexually dimorphic features by reducing prominent masculine angles and proportions (Dr-mfo.com, 2025). For example, a prominent brow ridge is reduced, and the jawline is often tapered to a more oval or V-shape (Omnicosmetic.com, 2025). Once these foundational skeletal changes are established, fat grafting becomes vital.

Fat transfer is then meticulously applied to soften the transitions over newly contoured bone, fill any residual hollows, and add the subtle convexities that complete the feminine ideal. For instance, after reducing the brow bossing, fat can be grafted to the central forehead to ensure a smooth, rounded contour (Sluiter et al., 2024). Similarly, after jaw and chin reduction, fat can be used to further refine the lower facial contours, creating a delicate blend rather than an abrupt change. This layered approach ensures that the skeletal modifications are seamlessly integrated with the overlying soft tissues, preventing a “surgical” or unnatural appearance (Dr-mfo.com, 2025).

Complementing Cartilage Refinement

Cartilage refinement, particularly rhinoplasty for nose feminization, also benefits from the synergistic effects of fat grafting. A feminized nose typically features a smaller overall size, a narrower bridge, and a more delicate, slightly upturned tip (Drweinfeld.com, 2023). While rhinoplasty directly sculpts the cartilaginous and bony framework of the nose, fat grafting can be used to add subtle volume to the surrounding midface and cheeks. This creates a balanced visual effect, making the nose appear even more refined and in harmony with the overall facial contours. A smaller, more delicate nose can be emphasized by well-projected, soft cheeks achieved through fat transfer, enhancing the central facial aesthetic.

Soft Tissue Refinement for Optimal Harmony

Fat grafting is inherently a soft tissue modification, and it augments other soft tissue procedures like brow lifts and lip lifts. A brow lift raises the eyebrows to create a more open and feminine eye area (Dr-mfo.com, 2025). Fat can then be added to the temples and upper orbital region to smooth transitions and enhance the overall upper facial convexity, complementing the lifted brow.

Likewise, a lip lift shortens the space between the nose and upper lip, creating a more youthful and feminine mouth (Drweinfeld.com, 2023). Fat grafting to the lips then adds natural fullness, further enhancing the sensual and delicate proportions desired. This comprehensive soft tissue approach ensures that all elements of the face contribute to a unified feminine expression.

Functional Improvements Alongside Aesthetic Changes

Beyond aesthetic transformation, a holistic approach to FFS, including fat grafting, can contribute to significant functional improvements. For instance, volume restoration in the midface and around the eyes can support better vision and alleviate discomfort from orbital hollowing. While fat grafting doesn’t directly address issues like chewing or breathing, its integration with underlying skeletal modifications helps create a more balanced facial structure, indirectly supporting overall functional integrity. The psychological benefits are profound, with patients often experiencing a significant reduction in gender dysphoria, improved self-esteem, and enhanced body image, further contributing to a better quality of life (Gender Confirmation Center, 2025).

The art of facial feminization lies in the surgeon’s ability to orchestrate these diverse techniques into a seamless symphony. Fat grafting, with its versatility and natural outcomes, acts as a crucial unifying element, blending the hard tissue changes with the soft tissue contours to achieve an integrated, harmonious, and truly authentic feminine face. This comprehensive strategy ensures that the patient’s transformation is not only visually striking but also deeply affirming.

Preoperative Planning and Advanced Technologies for Precision

The success of advanced facial feminization surgery, particularly when incorporating fat grafting, hinges on an exceptionally thorough and precise preoperative planning phase. This critical stage has been revolutionized by the integration of cutting-edge imaging modalities and virtual technologies, offering an unprecedented level of accuracy and predictability in achieving desired outcomes (Dr-mfo.com, 2025).

High-Resolution 3D Imaging

The process typically begins with high-resolution three-dimensional imaging, such as Cone-Beam Computed Tomography (CBCT) or standard Computed Tomography (CT) scans. These imaging techniques provide granular anatomical data of the patient’s skull and overlying soft tissues. This data is essential for an accurate diagnosis of existing skeletal differences, including subtle asymmetries, areas of bone volume deficit, and precise assessment of critical underlying structures like nerve pathways and sinus cavities (Dr-mfo.com, 2025). The detailed understanding derived from these images forms the fundamental bedrock upon which the entire surgical strategy is built, allowing surgeons to meticulously map out the existing anatomy and pinpoint all areas requiring correction or augmentation.

Virtual Surgical Planning (VSP)

Building upon this rich imaging data, three-dimensional virtual surgical planning (VSP) systems have become indispensable tools. VSP involves importing the patient’s CT or CBCT data into specialized software, where a precise 3D digital model of the face and skull is generated (Dr-mfo.com, 2025). Within this sophisticated virtual environment, surgeons can meticulously plan every osteotomy (bone cut), bone graft placement, and custom implant positioning.

This digital platform allows for the simulation of various surgical scenarios, enabling surgeons to virtually adjust bone segment movements, refine contours, and visualize potential aesthetic and functional outcomes before making any physical incisions. This iterative planning process ensures precise measurement of bone reductions or augmentations, guaranteeing that the final contours align not only with feminizing principles but also with the patient’s specific reconstructive needs.

For fat grafting, VSP is used to identify precise areas requiring volume enhancement and to anticipate how soft tissues will drape over the newly sculpted skeletal framework. This allows for customized planning of fat injection points and volumes, ensuring that the added fat complements the underlying bone work. For example, customized cutting guides and drilling templates can be virtually designed and subsequently 3D printed, which are then used intraoperatively to execute the planned osteotomies with remarkable accuracy, thereby minimizing human error and enhancing surgical precision (Dr-mfo.com, 2025).

Emerging Role of Artificial Intelligence (AI)

The emerging role of artificial intelligence (AI) in preoperative morphing offers further advancements. AI-based software can generate three-dimensional morphs of the patient’s face, which can then be adjusted in real-time to demonstrate potential surgical outcomes across various facial regions. While still an evolving area, this technology holds immense potential for aligning patient expectations with realistic surgical possibilities, fostering more effective communication between patient and surgeon regarding desired goals (Dr-mfo.com, 2025).

Intraoperative Navigation Systems

Moreover, intraoperative navigation systems further enhance precision during the actual surgery. These systems track the exact position of surgical instruments in real-time relative to the patient’s anatomy and the pre-planned virtual model. This continuous validation of instrument placement and bone repositioning ensures that the surgery adheres precisely to the virtual plan, even in complex cases with distorted or atypical anatomy (Dr-mfo.com, 2025). The amalgamation of advanced imaging, virtual surgical planning, and intraoperative navigation systems not only significantly improves the accuracy, safety, and efficiency of FFS but also substantially enhances the predictability of outcomes, ultimately leading to higher patient satisfaction and profoundly natural-looking results.

A close-up portrait of a woman with striking blue eyes and light brown hair, set against a plain background.

Intraoperative Considerations and Challenges in Advanced Fat Grafting

The execution of advanced fat grafting within facial feminization surgery, particularly in complex cases or when combined with extensive bone work, presents a unique set of intraoperative considerations and challenges. These circumstances demand not only exceptional surgical skill but also considerable adaptability and a deep understanding of facial anatomy and the biological behavior of fat grafts.

Meticulous Preservation of Neurovascular Structures

One of the most critical challenges during fat injection, especially in delicate facial regions, is the meticulous management and preservation of vital neurovascular structures. The facial nerve and its numerous delicate branches, which control facial expressions, are particularly vulnerable during soft tissue dissection and cannula manipulation. Similarly, branches of the trigeminal nerve, responsible for sensation, can be at risk, potentially leading to temporary or permanent numbness or altered sensation. Precise knowledge of anatomical variations in nerve pathways, coupled with meticulous surgical technique, is crucial to preserve nerve function and minimize the risks of facial paralysis or sensory deficits. The judicious use of micro-cannulas and injecting in appropriate tissue planes (e.g., subcutaneous rather than intramuscular) helps reduce this risk.

Managing Tissue Integrity and Blood Supply

Vascular concerns are heightened in extensive fat grafting cases. Tissues that have been scarred from previous surgeries or subjected to trauma may have a compromised blood supply. This can increase the risk of flap necrosis (if combined with lifts), delayed wound healing, or excessive intraoperative bleeding. Careful, controlled dissection, gentle tissue handling, and meticulous hemostasis (control of bleeding) are paramount to preserve the delicate vascular network, which is essential for the survival of the fat graft itself. Ensuring adequate vascularity of the recipient bed is absolutely critical for graft survival and successful integration (Shauly et al., 2022).

Achieving Symmetry and Harmonious Contours

Achieving precise symmetry and harmonious contours with fat grafting can be challenging, especially in faces that may already have subtle asymmetries or have undergone previous modifications. While virtual surgical planning provides a robust roadmap, the reality of the operating field can still present unforeseen anatomical deviations or variations in tissue response. This necessitates a surgeon with extensive experience who can make informed, rapid decisions, potentially deviating from the initial plan if necessary, without compromising safety or aesthetic objectives.

Factors such as unexpected tissue elasticity, variable fat absorption rates in different areas, or the presence of fibrous scar tissue can all influence the precise execution of fat placement. Continuous intraoperative assessment, often involving repeated visual inspection and palpation, is vital to ensure that fat injections are balanced and aligned with the feminizing goals. The layered micro-injection technique helps to distribute the fat evenly, reducing the risk of lumpiness or uneven contours (Gender Confirmation Center, 2025).

Optimizing Graft Viability during Transfer

Maintaining the viability of the fat cells during the transfer from the processing unit to the recipient site is another critical intraoperative consideration. Exposure to air (desiccation), excessive heat or cold, or prolonged handling can all reduce cell survival (Shauly et al., 2022). Therefore, closed system aspirator and injection systems are often preferred as they provide a continuous, controlled environment, reducing the risk of fat desiccation and loss of important stromal components (Shauly et al., 2022). These systems can also modulate injection pressure, ensuring a consistent, laminar flow of fat, which theoretically reduces the risk of fat embolism (Shauly et al., 2022).

The sheer volume and intricacy of combined fat grafting and other FFS procedures can lead to prolonged operative times, which in turn increases the risks associated with general anesthesia and overall patient recovery. Therefore, a highly coordinated surgical team, efficient instrumentation, and judicious patient selection based on a thorough preoperative assessment are essential prerequisites for successfully navigating these intraoperative complexities and achieving optimal, safe, and transformative results.

Post-Operative Recovery and Long-Term Management

The post-operative phase following facial feminization surgery involving fat grafting is a crucial period demanding meticulous care, patience, and a well-structured management plan. Patients must understand that the immediate post-operative appearance will evolve significantly over weeks and months as swelling subsides and the grafted fat integrates (Omnicosmetic.com, 2025; Gender Confirmation Center, 2025).

Immediate Post-Operative Expectations

Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort at both the fat harvesting sites and the grafted facial areas. Swelling is a universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week. It gradually subsides over several weeks, though residual swelling, especially in areas of significant fat transfer, can take up to a year or even longer for the final contours to fully emerge (Gender Confirmation Center, 2025; Omnicosmetic.com, 2025). Bruising will similarly resolve, usually within 2 to 4 weeks, transitioning through various color changes before fading completely.

Pain and discomfort are manageable with prescribed analgesia and anti-inflammatory medications. The diligent application of cold compresses in the initial days helps to minimize swelling and alleviate discomfort. Patients undergoing extensive procedures may require a short hospital stay for close monitoring and effective pain control (Omnicosmetic.com, 2025).

Specific Post-Operative Care Instructions

Post-operative care instructions are specifically tailored to promote optimal fat graft survival and minimize complications:

  • Head Elevation: Sleeping with the head elevated for several weeks is strongly recommended to optimize lymphatic drainage and reduce facial swelling (Gender Confirmation Center, 2025).
  • Activity Restrictions: Strenuous activities, heavy lifting, and any actions that might elevate blood pressure or stress healing facial structures are strictly avoided for at least two to four weeks (Omnicosmetic.com, 2025; Quartz.com.tr, 2025).
  • Avoid Pressure on Grafted Areas: It is paramount to avoid any direct pressure on the areas where fat has been injected for at least six weeks (Plasticsurgery.org, 2024; Gender Confirmation Center, 2025). This includes avoiding side sleeping, which could disrupt fat integration and increase the risk of fat necrosis or fat loss. Compression garments are typically avoided in fat-grafted facial areas, in contrast to liposuction donor sites where they are often used (Shauly et al., 2022).
  • Oral Hygiene: If intraoral incisions were made (common with jaw/chin work or buccal fat procedures), meticulous oral hygiene, often with antimicrobial mouth rinses, is essential to prevent infection (Omnicosmetic.com, 2025).
  • Diet: A soft or liquid diet may be recommended for a period, particularly if jaw or chin procedures were performed concurrently (Omnicosmetic.com, 2025; Quartz.com.tr, 2025).
  • Lymphatic Drainage Massage: Gentle lymphatic drainage massages may be recommended in later stages to help expedite the resolution of swelling and improve soft tissue suppleness (Quartz.com.tr, 2025).

Long-Term Stability and Management

While fat grafting provides a long-lasting enhancement, it is crucial to understand that the face continues to undergo natural aging processes. The transferred fat cells, once integrated, behave like native fat cells; therefore, significant weight fluctuations can impact their volume (Plasticsurgery.org, 2024; Gender Confirmation Center, 2025). Maintaining a steady weight is advised to preserve the results. Soft tissue changes due to aging may necessitate minor revisions or non-surgical touch-ups years after the initial surgery.

Regular follow-up appointments with the surgical team are essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction (Quartz.com.tr, 2025). A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey, fostering a harmonious alignment between internal identity and external presentation.

A black and white portrait photograph of a woman with long hair, looking directly at the camera with a serious expression.

Conclusion: The Transformative Impact of Advanced Fat Grafting

The application of advanced fat grafting techniques within facial feminization surgery represents a significant evolution in achieving natural, harmonious, and deeply authentic feminine contours. As this comprehensive exploration has underscored, the journey to aligning one’s external appearance with their gender identity is profoundly personal, and fat grafting offers a bespoke solution that honors the unique anatomical blueprint of each individual. We have delved into the meticulous stages of this procedure, from the careful selection of donor sites and the innovative harvesting methods that preserve cellular viability, to the sophisticated processing techniques that purify and concentrate the most robust adipose cells for transfer.

Precision injection strategies, utilizing micro-cannulas and layered placement, are paramount in sculpting the delicate feminizing effects across key facial regions such as the cheeks, temples, and lips. These techniques not only restore lost volume but also soften masculine angularities, creating the gentle convexities and smooth transitions that define a feminine aesthetic. The nuanced understanding of fat graft survival, influenced by factors like tissue handling, oxygenation, and the regenerative potential of adipose-derived stem cells, is critical for ensuring the longevity of these transformative results. This biological integration differentiates fat grafting, offering a durable solution that seamlessly blends with the body’s natural tissues, eliminating the concerns associated with synthetic materials (Gender Confirmation Center, 2025).

Furthermore, this guide has highlighted the importance of minimizing complications such as asymmetry, overcorrection, and fat necrosis through meticulous planning, precise surgical execution, and diligent post-operative care. The emphasis on avoiding pressure on grafted areas and maintaining consistent patient health underscores the collaborative nature of this journey between surgeon and patient. Advanced technologies, including 3D imaging and virtual surgical planning, have revolutionized preoperative strategizing, enabling surgeons to visualize outcomes with unprecedented accuracy and tailor interventions to individual needs (Dr-mfo.com, 2025).

Ultimately, fat grafting is not merely an isolated procedure but an integral component of a holistic feminization strategy. It works synergistically with bone restructuring and cartilage refinement, blending hard tissue modifications with soft tissue enhancements to create a cohesive and natural facial aesthetic (Dr-mfo.com, 2025). Beyond the visible aesthetic changes, successful fat grafting contributes significantly to psychological well-being, reducing gender dysphoria and fostering a deeper sense of self-confidence and authenticity. The ability to utilize one’s own living tissue for such a profound transformation resonates deeply, offering results that are not just outwardly beautiful but intrinsically aligned with the individual’s inner self.

For individuals considering this life-changing aspect of FFS, the critical decision lies in selecting a highly experienced, board-certified surgeon who possesses both artistic vision and profound technical expertise in advanced fat grafting and craniofacial surgery. Such a specialist can navigate the complexities, ensuring not only the safety of the procedure but also the achievement of results that are natural, long-lasting, and deeply satisfying.

Embarking on this journey requires careful consideration, open communication with an expert, and a commitment to meticulous care, all of which culminate in a truly transformative experience that redefines self-perception and empowers individuals to live more authentically. By embracing these advanced techniques, the future of facial feminization surgery continues to offer remarkable possibilities for profound and affirming transformations.

Frequently Asked Questions

Why is fat grafting important in facial feminization surgery (FFS)?

Fat grafting is crucial in FFS for creating softer, rounder, and more youthful feminine contours. It utilizes the patient’s own fat to soften masculine angularities, restore lost volume, and blend transitions over bone modifications, offering natural and lasting results.

How does the fat grafting process work from start to finish?

The process involves three main stages: first, fat is harvested from donor sites like the abdomen or thighs using gentle liposuction. Second, this fat is processed (e.g., via centrifugation or micro-fragmentation) to purify and concentrate viable fat cells. Finally, the refined fat is precisely injected into targeted facial areas using micro-cannulas to sculpt desired contours.

What are the primary benefits of using my own fat for facial feminization?

Using your own fat (autologous fat) for feminization eliminates the risk of allergic reactions or rejection, as the tissue is biologically compatible. It provides natural-looking and feeling results, with the potential for long-lasting permanence. Additionally, the transferred fat contains regenerative cells that can improve skin quality.

Which facial areas can be effectively treated with fat grafting in FFS?

Fat grafting is highly effective in feminizing various facial regions, including the cheeks (for higher projection), temples and forehead (for smoother, rounded contours), lips (for increased fullness), midface (to restore volume), and to soften jawline and chin contours. It also helps diminish nasolabial folds and under-eye hollows.

How long do the results of facial fat grafting typically last?

Once successfully integrated and vascularized, the results of fat grafting are generally considered permanent. While some initial fat reabsorption (around 20-50%) occurs in the first few months, the surviving fat cells can last for many years. Maintaining a stable weight helps preserve these long-term results.

What are the potential risks and complications associated with facial fat grafting?

Potential risks include fat necrosis (where some fat cells don’t survive), asymmetry, overcorrection, bruising, swelling, and, rarely, infection or nerve damage. These risks are minimized with precise surgical technique, careful planning, and proper post-operative care by an experienced, board-certified surgeon.

How do advanced technologies like Lipocube contribute to successful fat grafting?

Advanced technologies like Lipocube micro-fragment the fat cells, increasing their viability and improving integration into the facial tissues. This enhanced processing, along with techniques like Vaser liposuction for gentle harvesting, contributes to smoother, more natural, and longer-lasting results by optimizing the quality and survival of the fat graft.

Bibliography

  • Feminization Center. (2025). Facial Softening Techniques in Feminization Surgery: Fat Grafting and Fillers. https://feminizationcenter.com/facial-softening-techniques-in-feminization-surgery-fat-grafting-and-fillers/
  • Gender Confirmation Center. (2025, May 30). Facial Fat Transfer: Feminization and Rejuvenation Surgeries. https://www.genderconfirmation.com/facial-fat-transfer/
  • Dr-mfo.com. (2025, October 12). Layered Feminization: Integrating Bone, Cartilage, and Soft Tissue Techniques for Seamless FFS Results. https://www.dr-mfo.com/layered-feminization-soft-tissue-techniques-ffs/
  • Drweinfeld.com. (2023, April 28). Top 10 Facial Feminization Procedures. https://www.drweinfeld.com/blog/top-10-facial-feminization-procedures/
  • Omnicosmetic.com. (n.d.). Facial Feminization Surgery (FFS). https://omnicosmetic.com/procedures/gender-confirming/facial-feminization/
  • Plasticsurgery.org. (2024, January 18). The future of facial augmentation: A closer look at fat grafting and transfer techniques in facial plastic surgery. https://www.plasticsurgery.org/news/articles/the-future-of-facial-augmentation-a-closer-look-at-fat-grafting-and-transfer-techniques-in-facial-plastic-surgery
  • Quartz.com.tr. (2025). Facial Feminization Surgery (FFS) | with Fat Injection 2025. https://www.quartz.com.tr/en/facial-feminization-surgery-ffs/
  • Shauly, O., Gould, D. J., & Gilman, R. H. (2022). Fat Grafting: Basic Science, Techniques, and Patient Management. Plast Reconstr Surg Glob Open, 10(3), e3987. https://pmc.ncbi.nlm.nih.gov/articles/PMC8932485/
  • Sluiter, E. C., Lane, M., Morrison, S. D., Kuzon, W. M., & Gilman, R. H. (2024). Fat Grafting for Forehead Contouring in Facial Feminization. Plast Reconstr Surg Glob Open, 12(8), e6073. https://pmc.ncbi.nlm.nih.gov/articles/PMC11326469/
  • The Spiegel Center. (2023). The Evolution of Facial Feminization Surgery. https://www.drspiegel.com/transgender/the-evolution-of-facial-feminization-surgery/

7 Critical Insights: Integrated Lower Orbital Rim & Midface Feminization

A close-up photograph of a person's eye, focusing on the intricate details of the eyelashes and the iris. The image highlights the texture of the skin and the natural beauty of the eye.

Facial feminization surgery (FFS) represents a profound and intricate journey, meticulously designed to align an individual’s external appearance with their affirmed feminine identity. The lower orbital rim and midface junction are pivotal areas in this transformation. Subtle modifications in these regions dramatically influence the perception of gender, youthfulness, and overall facial harmony. Therefore, an integrated surgical approach is not merely advantageous, but absolutely essential for achieving natural, balanced, and deeply satisfying outcomes (Barnett et al., 2023).

This critical junction, encompassing the delicate structures around the eyes and the central contours of the cheeks, forms a complex aesthetic unit. Masculine features in this area often include a heavier, more prominent lower orbital rim and flatter, less projected cheekbones. These characteristics can create shadows and angularity that contribute to a perceived masculine appearance. Consequently, transforming these features requires a nuanced understanding of both bone and soft tissue dynamics, along with a strategic combination of advanced surgical techniques.

The significance of customizing procedures to each patient’s unique anatomy cannot be overstated. Every individual presents a distinct skeletal framework, soft tissue distribution, and skin quality. A “one-size-fits-all” methodology is inherently inadequate for achieving optimal results in such a sensitive and visible area. Instead, a bespoke surgical strategy must be meticulously tailored, leveraging precise diagnostic tools and advanced planning to address specific anatomical variations (Dr. MFO, 2025c).

This comprehensive exploration will delve into the foundational anatomical differences that guide feminization of the lower orbital rim and midface. We will examine the sophisticated preoperative assessment techniques, including 3D imaging and virtual surgical planning, which serve as the blueprint for success. Furthermore, we will dissect the array of surgical interventions available, from precise bone reduction and contouring to volume augmentation via fat grafting or custom implants. The synergistic application of these techniques ensures a seamless transition and a harmonious overall facial aesthetic. Understanding these integrated approaches is vital for both practitioners and individuals considering FFS, providing clarity on how meticulous planning and execution culminate in truly transformative and life-affirming results. Ultimately, this detailed analysis aims to illuminate the profound interplay between anatomical precision and surgical artistry, revealing how a deeply personalized approach is the cornerstone of impactful facial feminization outcomes.

A human hand drawing a blue dashed line around the eye sockets of a human skull using a black marker.

Understanding the Blueprint: Foundational Anatomy for Facial Feminization

Before any surgical intervention commences, a profound understanding of the patient’s foundational facial anatomy is paramount. A skilled facial feminization surgeon meticulously assesses the intricate interplay of underlying bone and overlying soft tissue structures. This comprehensive evaluation is critical because inherent differences in skeletal proportions and soft tissue distribution are key determinants of perceived gender.

Typically, masculine facial features often involve a more prominent brow ridge, a broader and squarer jawline, a larger and more anteriorly projected chin, and a distinct nasal profile characterized by a higher bridge and less upward rotation of the tip. However, the degree of expression of these features varies significantly among individuals due to genetic, ethnic, and developmental factors (Alraddadi, 2021). Recognizing these individual anatomical nuances is not merely an observational step but the foundational prerequisite for crafting a truly tailored and effective surgical plan.

To acquire this detailed anatomical blueprint, advanced diagnostic imaging plays an indispensable role. Three-dimensional computed tomography (3D CT) scans are frequently employed, providing a high-resolution, three-dimensional reconstruction of the patient’s unique skeletal and soft tissue architecture. These scans offer an unparalleled view of bone density, sinus pneumatization, nerve pathways, and the precise contours of the facial skeleton (Barnett et al., 2023). This data is then utilized in conjunction with virtual surgical planning (VSP) software, allowing surgeons to precisely measure existing structures and simulate potential surgical modifications.

Beyond static images, dynamic assessments of soft tissue mobility, skin elasticity, and muscle activity are also incorporated. Understanding the variations in tissue thickness and elasticity, for instance, is crucial for anticipating how overlying soft tissues will redrape following bone reductions or augmentations. The combination of comprehensive physical examination and advanced imaging provides the surgeon with a holistic understanding of the patient’s facial landscape, enabling them to formulate a feminization strategy that is both anatomically sound and aesthetically harmonious, moving beyond generic ideals to achieve results that are authentic to the individual.

A close-up image of a person's face with golden lighting, gently holding their face with both hands, highlighting their lips and eyes.

Regional Deep Dive: Anatomical Impact on Specific Feminization Techniques

The Forehead and Orbital Rims: Sculpting a Feminine Foundation

The upper third of the face, comprising the forehead and orbital rims, is a primary region for gender recognition. Variations in the frontal bone and supraorbital ridge (brow bone) are among the most significant sexually dimorphic features. Masculine foreheads often present with a prominent brow bossing, a heavier and more horizontally positioned brow relative to the superior orbital rim, and a forehead that recedes backward. In stark contrast, feminine foreheads are typically characterized by a smoother, rounder contour, a more vertically oriented profile, and eyebrows that arch higher, positioned above the orbital rim (Barnett et al., 2023).

The degree of frontal bossing can vary considerably among individuals, directly impacting the complexity and choice of surgical intervention. These anatomical variations directly influence the selection of forehead contouring procedures, primarily categorized into Type 1 (shaving), Type 2 (combination), or Type 3 (setback) techniques. For individuals with a relatively thick anterior frontal sinus wall and less pronounced bossing, a Type 1 procedure, involving direct burring or shaving of the prominent bone, may suffice to create a smoother transition.

However, when the frontal sinus bone is thinner or the brow bossing is significantly prominent, a more extensive approach is often necessitated. A Type 3 cranioplasty, also known as frontal sinus setback, involves carefully removing the anterior wall of the frontal sinus, meticulously reshaping it, and then reattaching it in a more recessed and feminized position (Barnett et al., 2023). This reconstructive technique allows for a greater degree of reduction and a more profound feminizing effect, fundamentally altering the supraorbital contour and achieving the desired convex curvature of a feminine forehead.

In conjunction with forehead contouring, orbital rim contouring is frequently performed to further enhance upper facial feminization. In masculine faces, the bony edges around the eye sockets can appear heavier and more angular, often casting shadows that masculinize the eyes. By carefully smoothing and rounding these edges, the eyes appear larger, more open, and less shadowed, contributing to a softer, more inviting gaze. The precise execution of these modifications, especially near critical structures such as the supraorbital and supratrochlear nerves, is paramount to prevent sensory deficits.

Additionally, the natural hairline position and any existing brow descent will guide the selection of brow lift techniques. A coronal incision, extending across the scalp, may be chosen for significant hairline advancement combined with forehead contouring. An endoscopic brow lift, utilizing smaller incisions within the hairline, can achieve brow elevation with minimal hairline change, particularly when hairline lowering is not a primary objective. Virtual surgical planning, as detailed by Barnett et al. (2023), has emerged as an indispensable tool. It allows surgeons to precisely visualize desired outcomes and plan osteotomies with enhanced accuracy. This significantly reduces operative time and minimizes complications like over-resection or nerve injury. This meticulous pre-surgical mapping ensures altered contours integrate seamlessly, providing a harmonious and distinctly feminine upper facial aesthetic.

A smiling young woman with smooth, straight hair pulled back, posing against a plain gray background.

Midface and Cheeks: Sculpting Softness and Projection

The midface, prominently defined by the zygomatic (cheekbone) complex and the overlying soft tissues, plays a pivotal role in the perception of facial femininity and youthfulness. Significant variations exist in midface projection and contour between masculine and feminine physiognomies. Masculine midfaces often exhibit flatter zygomas with less anterior projection, contributing to a less triangulated facial shape. In contrast, feminine cheeks are typically characterized by higher, more anteriorly positioned zygomatic arches, creating a desirable convexity and contributing to a softer, more youthful, and often “heart-shaped” facial contour (Barnett et al., 2023).

The distribution and volume of subcutaneous fat, including the malar fat pad and buccal fat, also vary considerably, further influencing overall midface appearance. Surgical strategies for midface feminization are highly individualized, contingent upon the patient’s existing anatomical structure and desired aesthetic. When there is insufficient malar projection or a naturally flatter midface, cheek augmentation is often recommended.

This can be achieved through various methods. Autologous fat grafting, which involves harvesting fat from other areas of the patient’s body via liposuction, processing it, and then injecting it into the cheeks, offers a natural solution. This technique provides a soft, natural-looking augmentation and can simultaneously improve the quality of the overlying skin. Alternatively, custom alloplastic implants, typically made of biocompatible materials such as silicone, can be placed over the cheekbones to provide permanent volume and definition. These implants are either pre-designed or custom-fabricated based on 3D virtual surgical planning to precisely match the desired contours (Barnett et al., 2023).

Conversely, in rare instances where cheekbones are excessively wide or prominently angled in a masculine manner, a surgeon might consider zygomatic arch reduction to soften the midface width. Furthermore, the distribution of buccal fat—a deep fat pad located within the cheek—can impact facial fullness. For individuals with a fuller, rounder lower face that detracts from a feminine aesthetic, buccal fat pad removal may be considered to create a more defined and hollowed submalar region, enhancing the appearance of higher cheekbones.

The delicate interplay between these procedures allows for the creation of an “ogee curve”—a graceful, double S-curve contour from the temple to the cheek, which is highly indicative of youthful, feminine cheeks. When combining nose and cheek procedures, as highlighted by Dr. MFO (2025b), synergistic anatomical planning is critical due to the interdependence of nasal and midface aesthetics. An overly prominent nose, for example, can make the midface appear recessed, while well-projected cheekbones can visually balance a nose. Therefore, modifications in one area profoundly influence the perception of the other, requiring an integrated approach to achieve overall facial harmony.

The Nose: Achieving Delicate Proportions

The nose, positioned centrally on the face, is a critical feature that significantly influences overall facial balance and perceived gender. Nasal structures exhibit immense diversity, yet distinct patterns contribute to gender recognition. Masculine noses often feature a broader nasal bridge, a more prominent dorsal hump, wider nostrils (alar base), and a less upwardly rotated, sometimes even downwardly projecting, nasal tip. In contrast, feminine noses are typically characterized by a smaller overall size, a narrower bridge, a softer or slightly concave dorsal profile, and a more refined, slightly upturned nasal tip, contributing to a more obtuse nasolabial angle (Barnett et al., 2023).

This wide spectrum of nasal anatomy necessitates a comprehensive range of rhinoplasty techniques during facial feminization. Dorsal hump reduction is a common procedure, involving the careful removal or rasping of excess bone and cartilage along the nasal bridge to create a smoother, more delicate profile. Concurrently, narrowing the nasal bones through osteotomies (controlled bone cuts) helps to reduce the overall width of the nasal bridge, contributing to a more refined appearance. Tip plasty techniques are pivotal for feminizing the nasal tip; these involve meticulous reshaping of the lower lateral cartilages through excisions, sutures, and grafts to make the tip smaller, more defined, and appropriately rotated upward (Barnett et al., 2023). Alar base reduction may be performed to narrow excessively wide nostrils, which can be a masculine characteristic, ensuring the nasal base is proportionate to the feminized tip and bridge. The specific aims are to create a nose that harmonizes with the newly contoured forehead and midface, avoiding an overly aggressive or artificial appearance.

An open rhinoplasty approach, utilizing a small incision across the columella and internal incisions, is often favored in facial feminization due to the optimal access and visibility it provides to the underlying skeletal and cartilaginous framework. This allows the surgeon to precisely manipulate structures and address specific feminizing goals, such as caudal septal trimming for upward tip rotation (Barnett et al., 2023). The intricate relationship between the bony and cartilaginous components of the nose demands a highly skilled surgeon to achieve stable and aesthetically pleasing results.

Furthermore, the soft tissue envelope, comprising skin, subcutaneous fat, and muscle, plays a significant role in the final outcome; its thickness and elasticity determine how readily underlying changes will be revealed. Consideration of the nasal vascular supply, primarily from branches of the ophthalmic and facial arteries, and innervation from the trigeminal nerve, is crucial to minimize complications such as bleeding or sensory changes. The ultimate goal is to sculpt a nose that is in harmonious proportion with the overall feminized facial features, enhancing the patient’s self-perception and social comfort (Dr. MFO, 2025c).

Jawline and Chin: Softening the Lower Face

The lower third of the face, particularly the jawline and chin, are primary indicators of sexual dimorphism and significantly contribute to perceived gender. Masculine jawlines are typically broader, squarer, and more angular, often presenting with prominent mandibular angles and a thicker external oblique ridge. The chin in masculine faces can be wider, squarer, or excessively prominent, contributing to a strong, sometimes blunt, lower facial appearance. Conversely, feminine jawlines are generally narrower, more tapered, and often exhibit a graceful V-shape or oval contour with softer angles. The chin in feminine faces is typically more delicate, with less width and projection, contributing to a refined lower facial profile (Barnett etal., 2023).

Surgical strategies for feminizing the jawline and chin involve meticulously tailored osseous modifications. Mandibular angle reduction is a key procedure designed to soften the posterior jawline. This involves carefully shaving or resecting a portion of the bone at the prominent jaw angles, transforming a square contour into a smoother, more tapered transition from the ear to the chin. This procedure is often performed through intraoral incisions (inside the mouth) to avoid visible external scarring, allowing for precise osteotomy and contouring while mitigating damage to vital structures such as the inferior alveolar nerve (Barnett et al., 2023).

Chin reshaping, or genioplasty, addresses the size, projection, and shape of the chin. In facial feminization, the goal is often to reduce chin width, shorten its vertical height if it is excessively long, and/or reshape it to a more pointed or rounded form, depending on the patient’s desired outcome and existing anatomy. A common technique is the sliding genioplasty, where the chin bone is carefully cut horizontally, and the distal segment is repositioned. This segment can be moved backward for reduction, advanced for increased projection, vertically shortened, or narrowed to achieve the desired delicate, feminine contour. The repositioned bone segment is then secured with small plates and screws to ensure stability and predictable healing (Barnett et al., 2023).

For chins that primarily require reduction in width or projection without significant repositioning, direct bone shaving or burring can be performed. The integration of these procedures often culminates in a “V-line” surgery, which combines mandibular angle reduction and genioplasty to create a significantly more tapered and feminine lower facial silhouette. In some cases, masseter muscle reduction, either surgically or through botulinum toxin injections, may also be considered for individuals with hypertrophied (enlarged) jaw muscles contributing to excessive lower facial width. The combined effect of these carefully planned interventions results in a more graceful, harmonious, and distinctly feminine lower face, balancing the features modified in the upper and mid-face (Dr. MFO, 2025a).

The Trachea: A Smoother Neckline

The laryngeal prominence, commonly known as the Adam’s apple, is a distinct secondary sex characteristic that develops and becomes more prominent during male puberty due to the enlargement and acute angle of the thyroid cartilage. Its presence can be a significant source of gender dysphoria for many transgender women, as it is a highly visible feature immediately indicative of a masculine neck profile. A tracheal shave, also known as chondrolaryngoplasty, is a straightforward yet highly effective feminizing procedure specifically designed to reduce the size and prominence of the Adam’s apple (Barnett et al., 2023).

The procedure typically involves making a small, discreet transverse incision in a natural skin crease on the neck, often at the midpoint between the submental crease and the cervicomental angle, to minimize the visibility of any resulting scar. Through this incision, the surgeon carefully shaves down the most prominent part of the thyroid cartilage, reducing its projection and creating a smoother, softer contour of the neck. Extreme care is taken to preserve a rim of cartilage superior to the level of the vocal cords for stabilization and, crucially, to avoid damaging the vocal cords themselves, which are located just behind the cartilage (Barnett et al., 2023). This meticulous approach ensures that vocal function is preserved. While primarily a modification of cartilage, which is a form of skeletal tissue, the tracheal shave profoundly impacts the overall appearance of the neck and profile, contributing to a more feminine silhouette and alleviating a significant source of dysphoria.

The recovery from a tracheal shave is generally quicker than from more extensive bone procedures, with most acute swelling and discomfort subsiding within a few weeks. Patients may experience some temporary voice changes or a sensation of tightness immediately after the surgery, but these usually resolve as the healing progresses. In some cases, submental fat excision and platysmaplasty (neck muscle tightening) may be performed concurrently to further enhance the desired neck silhouette and achieve maximal skin tightening, especially in older patients where skin laxity is a greater concern (Barnett et al., 2023). For many individuals, achieving a smoother neckline provides immense psychological relief, allowing them to feel more comfortable and confident in their appearance, particularly when wearing clothing that exposes the neck. This relatively contained procedure offers a significant impact on overall gender affirmation by addressing one of the most visible masculine features of the head and neck region.

Integrating Techniques for Holistic Feminization: The Art of Synergy

True facial feminization rarely involves a singular procedure. Instead, it is an intricate symphony of coordinated surgical interventions, each meticulously planned to complement the others and holistically address the patient’s unique anatomy. The skilled surgeon acts as an architect, orchestrating a series of modifications—ranging from fundamental bone restructuring to subtle soft tissue refinements—to achieve a balanced, harmonious, and naturally feminine outcome. This integrated approach ensures that the overall result is cohesive and congruent with the patient’s gender identity, rather than a collection of isolated, disconnected changes. The synergy between procedures is paramount, as altering one facial component inevitably influences the perception and aesthetics of adjacent and distant features.

For instance, a reduction in brow bossing not only feminizes the forehead but also optically enlarges the eyes, making a subtle rhinoplasty’s impact even more pronounced. Similarly, jawline and chin reshaping procedures provide a narrower foundation, over which soft tissues drape more delicately, enhancing the effect of cheek augmentation and lip lifts. The thoughtful sequencing and combination of these techniques are what elevate facial feminization from mere surgical alteration to a sophisticated art form.

The decision for a comprehensive, single-stage facial feminization surgery versus a staged approach (multiple surgeries performed over time) is heavily influenced by the anatomical complexity of the case, the patient’s overall physical health, and personal preferences. While a single-stage procedure offers the convenience of one recovery period and often significant cost savings, patient safety remains the ultimate priority. Studies indicate that an increased number of procedures performed per anesthetic event in facial feminization patients does not necessarily predict higher complication rates, suggesting that well-planned, comprehensive single-stage approaches can be safely undertaken under appropriate medical judgment (Barnett et al., 2023).

However, for individuals with extensive surgical needs, significant medical comorbidities, or those who prefer to recover from smaller interventions sequentially, a staged approach may be more appropriate. In such cases, structural hard tissue procedures like frontal sinus setback, supraorbital contouring, jawline tapering, and rhinoplasty are often prioritized, followed by subsequent soft tissue procedures like facelifts, neck lifts, and blepharoplasty, particularly in older patients where skin laxity is a consideration (Barnett et al., 2023). This strategic sequencing ensures that the foundational skeletal changes are established before refining the overlying soft tissues, thereby optimizing both the aesthetic and functional outcomes. Regardless of the staging strategy, the overarching goal is to achieve seamless integration, where each surgical modification contributes harmoniously to the final feminine facial contour.

Preoperative Planning and Technological Advancements for Precision

The success of advanced facial feminization surgery, particularly in cases involving significant anatomical variations, hinges critically on comprehensive and precise preoperative planning. This crucial phase has undergone a profound revolution with the integration of cutting-edge imaging modalities and virtual technologies, offering an unprecedented level of accuracy and predictability. High-resolution imaging, such as Cone-Beam Computed Tomography (CBCT) and standard Computed Tomography (CT) scans, provides detailed three-dimensional anatomical data of the patient’s skull and overlying soft tissues (Barnett et al., 2023).

This granular data is absolutely essential for an accurate diagnosis of existing skeletal differences, including bone volume deficits, subtle asymmetries, malposition of facial segments, and a precise assessment of critical underlying structures such as nerve pathways and sinus cavities. The detailed understanding derived from these images forms the fundamental bedrock upon which the entire surgical strategy is built, allowing surgeons to meticulously map out the existing anatomy and pinpoint all areas requiring correction or augmentation.

Building upon this rich imaging data, three-dimensional virtual surgical planning (VSP) systems have become indispensable tools in contemporary facial feminization. VSP involves importing the patient’s CT or CBCT data into specialized software, where a precise 3D digital model of the face and skull is generated. Within this sophisticated virtual environment, surgeons can meticulously plan every osteotomy (bone cut), bone graft placement, and custom implant positioning. This digital platform allows for the simulation of various surgical scenarios, enabling surgeons to virtually adjust bone segment movements, refine contours, and visualize the potential aesthetic and functional outcomes before making any physical incisions. This iterative planning process ensures precise measurement of bone reductions or augmentations, guaranteeing that the final contours align not only with feminizing principles but also with the patient’s specific reconstructive needs. For example, customized cutting guides and drilling templates can be virtually designed and subsequently 3D printed, which are then used intraoperatively to execute the planned osteotomies with remarkable accuracy, thereby minimizing human error and enhancing surgical precision (Barnett et al., 2023).

Beyond virtual planning, the emerging role of artificial intelligence (AI) in preoperative morphing offers further advancements. AI-based software, such as DeepSurface AI, can generate three-dimensional morphs of the patient’s face, which can then be adjusted in real-time to demonstrate potential surgical outcomes across various facial regions (Barnett et al., 2023). While still an evolving area requiring further research, this technology holds immense potential for aligning patient expectations with realistic surgical possibilities, fostering more effective communication between patient and surgeon regarding desired goals.

Moreover, intraoperative navigation systems further enhance precision during the actual surgery. These systems, often likened to a GPS for the surgeon, track the exact position of surgical instruments in real-time relative to the patient’s anatomy and the pre-planned virtual model. This continuous validation of instrument placement and bone repositioning ensures that the surgery adheres precisely to the virtual plan, even in complex cases with distorted or atypical anatomy. The amalgamation of advanced imaging, virtual surgical planning, and intraoperative navigation systems not only significantly improves the accuracy, safety, and efficiency of facial feminization surgery but also substantially enhances the predictability of outcomes, ultimately leading to higher patient satisfaction and profoundly natural-looking results.

Intraoperative Considerations and Challenges in Complex Feminization Procedures

The execution of complex facial feminization surgery, particularly for patients with significant skeletal variations or previous interventions, presents a unique and demanding set of intraoperative considerations and challenges. These circumstances require not only exceptional surgical skill but also considerable adaptability and a deep understanding of anatomical variations. Unlike more routine aesthetic procedures, these cases often involve highly altered or atypical anatomy, which can obscure normal surgical landmarks and significantly increase the complexity of dissection and bone manipulation. The surgeon must be prepared to navigate unexpected findings and adjust the pre-planned strategy in real-time while maintaining the overarching feminization goals.

One of the most critical challenges lies in the meticulous management and preservation of vital neurovascular structures. The facial nerve and its numerous delicate branches, which control facial expressions, are particularly vulnerable during extensive soft tissue dissection and bone reshaping in regions like the midface and jawline. Similarly, branches of the trigeminal nerve, responsible for sensation, can be at risk, potentially leading to temporary or permanent numbness or altered sensation. Precise knowledge of anatomical variations in nerve pathways, which can occur as highlighted by Alraddadi (2021), coupled with meticulous surgical technique, is crucial to preserve nerve function and minimize the risks of facial paralysis or sensory deficits. The judicious use of intraoperative nerve monitoring can serve as an invaluable tool, providing real-time feedback to help identify and protect these delicate structures during complex dissections.

Vascular concerns are also heightened in reconstructive and extensive feminization cases. Tissues that have been scarred from previous surgeries or subjected to trauma may have a compromised blood supply, increasing the risk of flap necrosis, delayed wound healing, or excessive intraoperative bleeding. Careful, controlled dissection, gentle tissue handling, and meticulous hemostasis are paramount to preserve the delicate vascular network. When large bone grafts are utilized, ensuring adequate vascularity of the recipient bed is absolutely critical for graft survival and successful integration. In situations with severely compromised blood supply, specialized techniques such as vascularized bone grafts, where a segment of bone is transplanted along with its nourishing artery and vein and reconnected using microsurgical techniques, may be required. This represents the pinnacle of reconstructive artistry but also significantly increases operative time and technical demands.

Managing inherent anatomical variations is another significant hurdle. As Alraddadi (2021) emphasizes, anatomical variations are normal presentations but can greatly influence clinical practice outcomes. No two cases of facial skeletal deficiency or dimorphism are identical, requiring surgeons to adapt their techniques dynamically to the unique presentation. While advanced virtual surgical planning provides a robust roadmap, the reality of the operating field can still present unforeseen anatomical deviations. This necessitates a surgeon with extensive experience in craniofacial and reconstructive surgery who can make informed, rapid decisions, potentially deviating from the initial plan if necessary, without compromising safety or aesthetic objectives. Factors such as unexpected bone density, the presence of fibrous scar tissue, or unusual sinus anatomy can all influence the precise execution of osteotomies and the stability of plate fixation strategies. Furthermore, achieving precise symmetry and harmonious contours in a face that may already be distorted requires continuous intraoperative assessment, often involving repeated visual inspection and palpation to ensure that bone reductions, advancements, or augmentations are balanced and aligned with the feminizing goals. The sheer volume and intricacy of combined bone and soft tissue work can lead to prolonged operative times, which in turn increases the risks associated with general anesthesia and overall patient recovery. Therefore, a highly coordinated surgical team, efficient instrumentation, and judicious patient selection based on a thorough preoperative assessment are essential prerequisites for successfully navigating these intraoperative complexities and achieving optimal, safe, and transformative results.

Post-Operative Recovery and Long-Term Management: Nurturing the Transformation

The post-operative phase following comprehensive facial feminization surgery, particularly when complex bone and soft tissue modifications have been performed, is a critical period that demands meticulous care, patience, and a well-structured management plan. The recovery timeline for extensive procedures is typically more protracted and can be more intense compared to standard aesthetic interventions, given the significant degree of bone manipulation, tissue reshaping, and potential for extensive swelling and bruising. Patients must be thoroughly prepared for this journey, understanding that the immediate post-operative appearance will evolve considerably over weeks and months.

Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort. Swelling is an almost universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week after surgery, gradually subsiding over several weeks to months. Full resolution of residual swelling, especially in areas of significant bone work or grafting, can take up to a year or even longer for the final contours to fully emerge. Bruising will similarly resolve, usually within 2 to 4 weeks, with color changes from purplish-black to greenish-yellow before fading completely. Pain management is crucial and is typically achieved through a combination of prescribed analgesia, anti-inflammatory medications, and diligent application of cold compresses, which help to minimize swelling and alleviate discomfort. Hospitalization may extend for several days, particularly after complex osteotomies or large graft placements, allowing for close monitoring of vital signs, early detection of potential complications such as hematoma or infection, and effective pain control.

Specific post-operative care instructions are tailored to the procedures performed. For individuals undergoing jaw or chin osteotomies, a soft or liquid diet is often prescribed for several weeks to prevent undue stress on the healing bone segments and intraoral incisions. Meticulous oral hygiene, often involving antimicrobial mouth rinses, is paramount to prevent infection in the oral cavity. Activity restrictions are stringent in the initial weeks; patients are advised to avoid strenuous activities, heavy lifting, and anything that might elevate blood pressure or stress the healing facial structures. Gradually, activity levels are increased as recovery progresses and clearance is given by the surgical team. Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce swelling. Physical therapy or gentle lymphatic drainage massages may also be recommended in later stages of recovery to help expedite the resolution of swelling and improve soft tissue suppleness.

Complex reconstructive procedures inherently carry potential complications beyond those of standard aesthetic surgery. While surgeons employ meticulous techniques to mitigate these, awareness and diligent monitoring are essential. Graft resorption, where a portion of transplanted autologous bone may be reabsorbed by the body, can lead to a partial loss of contour or volume, occasionally necessitating revision. For alloplastic implants, potential risks include implant exposure or infection, which can compromise implant integration and in severe cases require removal. Non-union or malunion of osteotomies, though rare, can occur if bone segments fail to heal properly, potentially leading to persistent asymmetry or functional issues, often requiring further surgical correction. Nerve damage, despite careful intraoperative preservation efforts, can manifest post-operatively as persistent numbness, altered sensation, or, in rare instances, motor weakness, particularly affecting facial expressions. Long-term stability expectations are a crucial aspect of patient counseling. While the extensive bone reshaping in feminization surgery provides a stable and lasting foundation, facial structures continue to undergo natural aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. Regular follow-up appointments are therefore essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction. A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey.

Functional and Aesthetic Restoration: Comprehensive Outcomes Beyond Appearance

The overarching goal of advanced facial feminization surgery, particularly when addressing severe facial skeletal deficiencies stemming from congenital anomalies, trauma, or complex developmental variations, extends far beyond mere aesthetic transformation. While the visual alignment of external features with an individual’s gender identity is paramount, equally significant is the comprehensive restoration of optimal facial function. For patients presenting with pre-existing functional impairments, the journey through feminization surgery offers a profound opportunity to simultaneously regain or improve vital physiological capabilities, thereby enhancing their overall quality of life and facilitating more seamless social interaction.

Functional impairments in such complex cases can be diverse and significantly impact daily life. These may include difficulties with mastication (chewing) due to severe jaw misalignment or temporomandibular joint (TMJ) dysfunction, which can be addressed through precise mandibular and maxillary osteotomies that not only feminize the jawline but also restore proper dental occlusion. Compromised vision or ocular discomfort arising from orbital dystopia (misplaced eyes) or malposition of the infraorbital rim can be alleviated through meticulous reconstruction of the orbital region, providing better support and protection for the eyes. Impaired breathing, often a consequence of severe nasal obstruction, septal deviation, or midface hypoplasia, can be corrected through comprehensive rhinoplasty that improves nasal airflow while simultaneously creating a more delicate nasal appearance (Barnett et al., 2023). Speech impediments, occasionally arising from abnormal oral or pharyngeal anatomy related to skeletal discrepancies, can also see improvements following corrective osseous surgery in the jaw and midface.

Therefore, a truly successful facial feminization outcome in these advanced cases is defined by the synergistic achievement of both highly feminine aesthetics and robust, enduring functional recovery. The intricate bone work, encompassing complex osteotomies, the strategic use of autologous bone grafts, and custom implant placements, plays a direct and foundational role in re-establishing proper skeletal support for these critical facial structures. For instance, correcting mandibular discrepancies not only sculpts a softer, more tapered jawline but critically restores proper dental occlusion and chewing efficiency, enabling better nutrition and comfort. Reconstructing the orbital rims and midface enhances visual field and provides improved protection for the eyes, while thoughtful rhinoplasty, beyond creating a more delicate nasal appearance, actively improves nasal airflow and respiratory function (Barnett et al., 2023). The integration of precise soft tissue management techniques further refines both outcomes. Accurate redraping of the skin, muscle, and fat over the newly contoured skeletal framework ensures natural-looking transitions and minimizes visible surgical evidence, contributing to a harmonious appearance that moves naturally with expression. Autologous fat grafting, beyond its aesthetic benefits of adding feminine volume to areas like the cheeks and lips, can also significantly improve local tissue quality, camouflage minor irregularities, and potentially enhance vascularity, further contributing to durable functional and aesthetic integration.

The meticulous preoperative planning involved, utilizing high-resolution 3D virtual surgical planning and intraoperative navigation, contributes profoundly to achieving this dual objective. By precisely defining bone movements, predicting soft tissue redraping, and mapping graft placements, surgeons can optimize both the feminizing aesthetic and the structural integrity necessary for restored function. Patient-reported outcome measures consistently demonstrate that individuals undergoing comprehensive facial feminization experience significant psychological benefits, including a profound reduction in gender dysphoria, improved self-esteem, and enhanced body image (Barnett et al., 2023). However, in reconstructive cases, these psychological gains are often compounded by the transformative impact of regaining lost or never-had functions, which further enhances overall quality of life, fosters greater independence, and facilitates more confident integration into society. The remarkable ability of modern reconstructive feminization surgery to simultaneously sculpt a face that is aesthetically feminine and fully functional represents the pinnacle of contemporary craniofacial and gender-affirming surgical practice, offering truly life-changing results for those facing the most profound anatomical challenges.

Selecting a Specialist: The Critical Choice for Complex Feminization

The decision to undergo advanced reconstructive facial feminization surgery for severe facial skeletal deficiencies is one of monumental significance, necessitating the selection of a highly specialized and exceptionally experienced surgeon. The inherent complexity of these cases demands a level of expertise that extends far beyond the scope of a general plastic surgeon or even one whose practice is solely focused on aesthetic feminization. Therefore, the paramount importance of choosing a surgeon with dual proficiency—deeply rooted in both routine facial feminization procedures and intricate maxillofacial reconstruction—cannot be overstated. Such a specialist possesses an unparalleled understanding of complex craniofacial anatomy, the biomechanics of bone remodeling and healing, and advanced reconstructive techniques, including microvascular surgery when vascularized grafts are indicated for compromised tissues (Dr. MFO, 2025a).

These highly specialized surgeons are adept at managing large skeletal defects, correcting severe congenital or acquired asymmetries, and precisely reconstructing compromised facial units. Crucially, this dual expertise means the surgeon not only understands how to create aesthetically pleasing feminine contours but also possesses the foundational knowledge and technical skill to rebuild a stable and functional facial framework from a significantly compromised or deficient starting point. This includes profound proficiency in performing complex osteotomies with precision, implementing advanced bone grafting techniques using either autologous tissue or customized alloplastic materials, and the expert deployment of custom implants to restore lost volume and projection. Their training often encompasses a blend of plastic surgery, oral and maxillofacial surgery, and dedicated craniofacial fellowship training, providing a robust skill set for the most challenging anatomical situations.

Furthermore, an ideal reconstructive feminization surgeon will be exceptionally well-versed in utilizing cutting-edge technologies that enhance precision and safety. This includes a mastery of high-resolution 3D virtual surgical planning (VSP) systems, the ability to design and utilize custom surgical guides and drilling templates, and proficiency with intraoperative navigation systems (Barnett et al., 2023). Their capacity to leverage these advanced tools ensures optimal surgical accuracy, minimizes potential risks, and maximizes the predictability of outcomes, particularly in scenarios characterized by distorted or atypical anatomy. Beyond technical skill, the most effective specialist will demonstrate a profoundly patient-centered approach. This involves engaging in thorough and empathetic consultations to fully understand the individual’s unique goals, specific concerns, and psychological needs. They are committed to providing realistic expectations regarding the surgical process, the nuances of recovery, and the potential long-term outcomes, which is especially vital given the inherent complexities and extended recovery periods of reconstructive cases. Verifying the surgeon’s credentials, including board certification in relevant surgical specialties and a comprehensive portfolio demonstrating successful outcomes in challenging reconstructive cases, is an essential step for prospective patients. Consulting with a surgeon who works within or collaborates with a multidisciplinary team, potentially including oral surgeons, orthodontists, and mental health professionals, further ensures a holistic and comprehensive approach to care, addressing all facets of the patient’s well-being. Ultimately, the selection of such a highly experienced and uniquely qualified surgeon is the single most critical factor in achieving safe, functional, aesthetically transformative, and enduring results in advanced reconstructive facial feminization surgery, providing patients with the confidence that their complex needs are in expert hands.

A close-up of a smiling woman with bright, sunlit skin and brown eyes, framing her face with her hands.

Conclusion: The Critical Role of Individualized Anatomical Strategy

The journey through facial feminization surgery is a profoundly personal and meticulously orchestrated process, uniquely shaped by each individual’s distinct facial anatomy. As this comprehensive exploration has underscored, achieving natural, harmonious, and enduring results in feminization requires far more than a generalized approach; it demands an intricate understanding of the subtle and overt differences in skeletal and soft tissue structures that define facial gender. The ability to precisely assess, plan, and execute surgical modifications based on a patient’s unique biological blueprint is the hallmark of truly transformative and successful outcomes. We have delved into how variations in the frontal bone and orbital rims dictate specific forehead contouring techniques, how midface projection influences strategies for cheek augmentation or reduction, and how the intricate cartilaginous and bony framework of the nose guides delicate rhinoplasty procedures. Similarly, the diverse forms of the mandible and chin necessitate highly individualized jawline and chin reshaping, while the laryngeal prominence requires careful reduction. Each of these regional modifications, when viewed in isolation, contributes to feminization, but their true power emerges from their synergistic integration.

The advancements in preoperative planning, particularly the integration of high-resolution 3D imaging and virtual surgical planning systems, have revolutionized the field, allowing surgeons to create highly detailed blueprints of the desired transformation. This technological synergy enhances precision, minimizes risks, and optimizes predictability, transitioning complex cases from challenging guesswork to precisely engineered solutions. Intraoperative challenges, such as the meticulous preservation of neurovascular structures and the dynamic adaptation to anatomical variations, underscore the demanding nature of these procedures and highlight the critical role of profound surgical experience. Furthermore, the post-operative recovery, often protracted and intensive, requires a comprehensive and patient-centered management plan to ensure optimal healing and long-term stability. Beyond the aesthetic alterations, successful facial feminization inherently encompasses the restoration or improvement of vital facial functions, addressing potential impairments related to mastication, vision, and breathing. This dual emphasis on form and function ensures that the patient not only achieves an external appearance congruent with their identity but also experiences a significant enhancement in overall quality of life.

The selection of a highly specialized surgeon, one possessing deep expertise in both facial feminization and complex maxillofacial reconstruction, stands as the single most critical decision for individuals embarking on this journey. Their unique skill set, combining artistic vision with a profound anatomical understanding, is indispensable for navigating the intricacies of advanced cases and delivering results that are both safe and aesthetically profound. Ultimately, facial feminization surgery, particularly when tailored to the individual’s unique anatomy, is a powerful affirmation of identity, fostering self-confidence and providing a deeper sense of authenticity. It is a testament to the continuous evolution of surgical science and artistry, offering life-changing possibilities for those seeking harmony between their inner self and outer presentation. The ongoing commitment to precision, personalized care, and comprehensive outcomes will continue to define this vital and transformative field, providing hope and tangible results for countless individuals.

Frequently Asked Questions

Why is individual facial anatomy so important in planning facial feminization surgery?

Individual facial anatomy is crucial because every face is unique, with varying bone structures and soft tissue distributions. A personalized surgical strategy, tailored to these specific anatomical nuances, ensures the most natural, harmonious, and effective feminization outcomes, as opposed to a generic approach.

What role do 3D imaging and virtual surgical planning play in customizing facial feminization procedures?

3D imaging, such as CT scans, provides a detailed blueprint of the patient’s skeletal and soft tissue architecture. Virtual surgical planning software allows surgeons to simulate procedures, precisely measure modifications, and design custom guides, significantly enhancing surgical precision, safety, and predictability.

How do bone modifications and soft tissue procedures interact synergistically in facial feminization?

Bone modifications (e.g., forehead contouring, jaw reduction) provide the foundational changes, redefining the facial framework. Soft tissue procedures (e.g., rhinoplasty, cheek augmentation, lip lifts) then refine these contours, add volume, and enhance expressions. Their synergistic combination ensures a cohesive, balanced, and naturally feminine appearance.

What are some of the critical challenges faced during complex facial feminization surgeries?

Challenges include meticulous preservation of vital neurovascular structures (like facial nerves), managing compromised blood supply in scarred tissues, adapting to unexpected anatomical variations, and ensuring precise symmetry. These demand exceptional surgical skill and adaptability.

What kind of recovery can be expected after extensive facial feminization surgery?

Recovery from extensive procedures typically involves significant swelling, bruising, and discomfort, which gradually subside over weeks to months. Full resolution of swelling and bone healing can take up to a year or more. Adherence to post-operative care, including rest, head elevation, and a soft diet, is crucial.

Beyond aesthetics, what other benefits does facial feminization surgery offer?

Beyond aesthetic alignment, facial feminization surgery can significantly improve or restore vital facial functions such as mastication (chewing), vision, and breathing, especially in cases of pre-existing skeletal deficiencies. This dual focus enhances overall quality of life, reduces psychological distress, and fosters greater social confidence.

What qualifications should one look for in a surgeon for complex facial feminization?

For complex cases, seek a surgeon with dual proficiency in both routine facial feminization and intricate maxillofacial reconstruction. This specialist should have extensive experience, board certification in relevant specialties, a strong portfolio of results, and expertise in advanced technologies like 3D virtual surgical planning.

Bibliography

  • Alraddadi, A. (2021). Literature Review of Anatomical Variations: Clinical Significance, Identification Approach, and Teaching Strategies. Cureus, 13(4), e14451. https://pmc.ncbi.nlm.nih.gov/articles/PMC8117423/
  • Barnett, S. L., Choe, J., Aiello, C., & Bradley, J. P. (2023). Facial Feminization Surgery: Anatomical Differences, Preoperative Planning, Techniques, and Ethical Considerations. Medicina (Kaunas), 59(12), 2070. https://pmc.ncbi.nlm.nih.gov/articles/PMC10744788/
  • Di Maggio, M. (2019). Forehead and Orbital Rim Remodeling. Facial Plastic Surgery Clinics of North America, 27(2), 207-220. https://pubmed.ncbi.nlm.nih.gov/30940386/
  • Dr. MFO. (2025a, October 13). Advanced Reconstructive FFS: Surgical Techniques for Severe Facial Skeletal Deficiencies. https://www.dr-mfo.com/advanced-reconstructive-ffs-surgical-techniques/
  • Dr. MFO. (2025b, July 4). Key Anatomical Considerations for Combined Nose and Cheek Procedures in Transgender FFS. https://www.dr-mfo.com/combined-nose-cheek-ffs-anatomical-considerations/
  • Dr. MFO. (2025c, July 10). FFS Procedures: Bone vs. Soft Tissue Modification for Facial Feminization. https://www.dr-mfo.com/ffs-procedures-bone-vs-soft-tissue-modification/

  • Feminization Center. (n.d.). Orbital Rim Contouring: A Detailed Approach to Facial Feminization. Retrieved October 26, 2025, from https://feminizationcenter.com/orbital-rim-contouring/
  • Golden State Plastic Surgery. (n.d.). Facial Feminization Surgery (FFS). Retrieved October 26, 2025, from https://gsplasticsurgery.com/facial-feminization-surgery/
  • Mittermiller, P. (n.d.). Orbital Rim Contouring for Facial Feminization – Los Angeles. Retrieved October 26, 2025, from https://paulmittermillermd.com/orbital-rim-contouring-for-facial-feminization

Expert Guide: Type 3 Forehead Osteotomy in Facial Feminization

A woman with curly hair wearing a black top is posing for the camera with her hand on her chest. She has a serious expression on her face, and her shadow is visible on the wall behind her.

The journey of facial feminization surgery often pivots on meticulously reshaping the forehead, a region profoundly impacting perceived gender. A prominent brow ridge, frequently referred to as brow bossing, presents a distinctly masculine characteristic. Conversely, a smoother, more gently rounded forehead, coupled with a higher eyebrow position, is universally associated with feminine aesthetics. Successfully addressing these profound anatomical differences is a foundational element of upper facial feminization. Among the various techniques available for forehead contouring, Type 3 forehead osteotomy stands out as the most comprehensive and impactful approach for individuals with significant frontal bossing. It involves an intricate process of surgically removing a section of the frontal bone, reshaping it, and then repositioning it to achieve a softer, more harmonious contour. This advanced procedure necessitates a deep understanding of craniofacial anatomy, precise surgical planning, and robust bone fixation methods to ensure both optimal aesthetic results and long-term structural stability.

This detailed guide offers a surgically focused exploration of Type 3 forehead osteotomy in facial feminization surgery (FFS). It delves into the essential anatomical underpinnings of the frontal bone and frontal sinuses, which are critical determinants in selecting the appropriate surgical methodology. We will meticulously break down the traditional Type 3 osteotomy, examining the specific surgical steps, including precise bone cuts, careful segment reshaping, and advanced fixation techniques utilizing plates and screws. Furthermore, this analysis will cover the nuances of intraoperative decision-making, emphasizing how individual patient anatomy and feminization goals guide the surgeon’s approach. A comparative evaluation will highlight the distinctions between Type 1, Type 2, and Type 3 forehead contouring techniques, discussing their respective surgical complexities, recovery profiles, and expected outcomes. The discussion will also address potential complications specific to these advanced techniques, outlining their surgical management to ensure patient safety and predictable results. Finally, we will detail crucial aspects of post-operative care, focusing on optimal bone healing and soft tissue adaptation, which are vital for nurturing the transformative results. The ultimate objective is to provide an authoritative resource that illuminates the intricate art and science behind achieving a truly feminized forehead, offering both practitioners and prospective patients a comprehensive understanding of this pivotal procedure.

A close-up portrait of a woman with striking features, wearing elegant attire, set against a dark background.

Understanding Forehead Anatomy: The Foundation of Feminization

A profound understanding of the forehead’s regional anatomy is paramount before initiating any forehead reshaping procedure. The forehead represents a complex layered structure encompassing skin, soft tissues, and vital underlying bone. At its core lies the frontal bone, a large cranial bone forming the anterior portion of the skull (Dr. MFO, 2025e). Inferiorly, this bone articulates with several other facial bones, including the nasal bones and zygomatic (cheek) bones.

Key anatomical areas of the frontal bone relevant to Type 3 setback include the squama frontalis, which is the large, vertical plate forming the forehead itself. In Type 3 morphology, the inferior portion of this squama, located just above the eye sockets, exhibits a pronounced anterior projection, known as frontal bossing. The supraorbital rims are the thickened arches of bone forming the superior margins of the orbits (eye sockets). In individuals with masculine features, these rims are typically more prominent and sharply angled, whereas feminine features are characterized by smoother, less pronounced contours (Dr. MFO, 2025e).

The glabella, a smooth, slightly depressed area between the eyebrows, superior to the root of the nose, also significantly contributes to the prominence of the Type 3 forehead. Perhaps most critically, the frontal sinuses are air-filled cavities situated within the frontal bone, typically behind the glabella and extending superiorly and laterally to varying degrees. Their size, shape, and precise location vary significantly among individuals, making them crucial considerations during surgical planning to avoid inadvertent perforation and potential complications such as cerebrospinal fluid (CSF) leakage or infection (Pansritum, 2021). Surgeons often visualize these air pockets like small caves within the bone, necessitating precise knowledge of their boundaries.

Deep to the frontal bone lie the protective layers of the brain, including the dura mater. Maintaining the integrity of the dura is paramount to prevent CSF leakage and potential intracranial complications (Dr. MFO, 2025e). Additionally, the supraorbital and supratrochlear nerves and vessels exit the orbit through notches or foramina in the supraorbital rim, supplying sensation to the forehead and scalp. Protecting these delicate neurovascular structures is vital to prevent postoperative numbness or pain (Dr. MFO, 2025e). Surgeons must precisely visualize this complex three-dimensional anatomy, often relying heavily on advanced preoperative imaging to understand individual variations in frontal sinus size and location.

A doctor in surgical attire points to a detailed skull image displayed on a computer monitor while discussing it with a patient seated nearby.

Type 3 Forehead Osteotomy: A Detailed Surgical Methodology

Type 3 forehead osteotomy, also known as frontal bone setback or forehead reconstruction, is the most complex and frequently performed technique for individuals with significant brow bossing in facial feminization surgery (Dr. MFO, 2025d). This procedure directly addresses the bony projection that most significantly contributes to a masculine forehead shape by surgically removing, reshaping, and repositioning a section of the frontal bone. This comprehensive approach is necessary when shaving alone would be insufficient or would risk exposing the frontal sinus (Mittermiller, 2025).

Preoperative Assessment and Advanced Planning

Meticulous preoperative planning is the cornerstone of a successful Type 3 forehead setback. This phase involves a comprehensive patient assessment and detailed analysis of their unique anatomy (Dr. MFO, 2025e). A thorough medical history and physical examination are conducted to identify any comorbidities that might affect surgical risk or bone healing. Patient aesthetic goals are discussed to ensure alignment with realistic surgical possibilities. Palpation of the supraorbital rims and glabella provides tactile information about the underlying bone structure.

High-quality imaging is indispensable. A fine-cut Computed Tomography (CT) scan of the craniofacial skeleton is essential. This provides detailed three-dimensional anatomical data, allowing the surgeon to precisely visualize the extent of frontal bossing, the size and shape of the frontal sinuses, the thickness of the frontal bone, and its relationship to underlying structures like the dura (Facialteam, 2025b; Pansritum, 2021). This data is often used to create three-dimensional reconstructions of the skull, which serve as powerful visual tools for planning osteotomy lines and simulating the setback procedure (Dr. MFO, 2025e). Specialized software enables virtual osteotomies and precise measurement of the required setback distance, optimizing osteotomy lines to minimize complications.

Surgical Access and Soft Tissue Management

The most common approach for Type 3 forehead osteotomy involves a bicoronal incision, extending from ear to ear across the top of the head, typically several centimeters posterior to the hairline (Pansritum, 2021). This provides excellent exposure of the frontal bone and access for both bone work and potential hairline advancement. Careful beveling of the incision within the hair follicles helps minimize visible scarring. Facialteam, for instance, has developed a posterior coronal approach, which they consider pioneering, offering full visibility while preserving hairline aesthetics (Facialteam, 2025a).

Following the incision, the scalp flap is carefully elevated in the subgaleal or subpericranial plane. This minimizes bleeding and protects the underlying supraorbital and supratrochlear neurovascular bundles. The pericranium can also be used as a vascularized flap for dural repair if required (Dr. MFO, 2025e).

The Osteotomy: Precise Bone Cuts

This is the critical step where the frontal bone segment is carefully outlined and cut. The osteotomy design is based on the preoperative plan and meticulously considers the size and location of the frontal sinuses, the desired setback amount, and the aesthetic goals (Dr. MFO, 2025e). A common osteotomy pattern involves a superior horizontal cut in the squama frontalis, bilateral vertical or oblique cuts extending towards the supraorbital rims, and inferior cuts along the superior aspect of the orbital rims, connecting the lateral cuts. These inferior cuts demand extreme caution to avoid entering the orbits or injuring vital neurovascular structures (Dr. MFO, 2025e; Pansritum, 2021).

Osteotomies are typically performed using a high-speed burr or an oscillating saw. During these cuts, copious irrigation is crucial to cool the bone and minimize thermal injury. The surgeon must constantly monitor the depth of the cut, especially when approaching the inner table of the skull and the dura (Dr. MFO, 2025e). Ultrasonic surgical instruments, such as the piezoelectric scalpel, are increasingly utilized for clean bone cuts without damaging soft tissues, thereby reducing trauma and potentially shortening recovery (Facialteam, 2025b). The anterior wall of the frontal sinus is delicately removed, allowing it to be sculpted separately.

Bone Setback, Reshaping, and Fixation

Once the bone segment is free, it is carefully removed. The underlying bone, which could be the posterior table of the frontal sinus or the anterior cranial fossa bone, is then contoured and burred down to the desired level of setback (Mittermiller, 2025). The removed bone segment is then meticulously reshaped on a sterile tray, often by burring down the prominent areas corresponding to the glabella and supraorbital rims, to match the new underlying contour and achieve the desired external convexity (Dr. MFO, 2025e).

The reshaped bone segment is then carefully placed in its new, setback position. It is held firmly while fixation plates are applied. These plates are contoured to fit the new bone shape and the underlying stable bone without tension. Plates are strategically placed to provide stability across the osteotomy lines, preventing rotation or displacement of the bone segment (Dr. MFO, 2025e). Tiny titanium plates and screws are typically used to secure the bone in place (Dr. MFO, 2025d). These screws are carefully inserted, ensuring they do not penetrate the inner table of the skull into the dura or brain.

Specialized instrumentation, including plate bending pliers, drill bits, and screwdrivers, are essential for this phase. Resorbable plates and screws, which dissolve over time, are also an option in certain situations, offering the benefit of not requiring removal (Costa, 2023; Mittermiller, 2025). However, titanium remains a common choice due to its strength and biocompatibility, providing robust, long-lasting fixation, especially for the significant movements involved in Type 3 setback (Dr. MFO, 2025e).

Addressing Supraorbital Rims and Glabella

While the main setback addresses overall forehead prominence, specific attention is paid to the supraorbital rims and glabella. The inferior edge of the setback bone segment forms the new superior aspect of the supraorbital rims. Additional burring or contouring of the underlying bone or the edge of the setback segment may be performed to achieve a smooth, feminine brow contour. The glabellar region, being part of the setback segment, is automatically reduced in prominence. Further localized burring or contouring may be performed if necessary (Dr. MFO, 2025e). The combination of burring and reconstruction ensures optimal control and adaptation to individual anatomy (Facialteam, 2025a).

Closure and Post-Procedure Considerations

After securing the bone, the edges of the osteotomy are carefully smoothed to eliminate any palpable steps or irregularities, ensuring a seamless transition. The surgical site is thoroughly irrigated. If the frontal sinus was entered, the mucosa (lining) is carefully removed, and the opening is often covered with a pericranial flap or bone wax to prevent mucocele formation and infection (Dr. MFO, 2025e). The scalp flap is then meticulously repositioned, and the incision is closed in layers, typically involving the galea, subcutaneous tissue, and skin. Drains may be placed to manage postoperative fluid accumulation (Dr. MFO, 2025e). Hairline lowering can also be performed simultaneously if desired (Pansritum, 2021).

A surgeon performing a procedure on a patient's face in a clinical setting.

Comparative Analysis of Forehead Contouring Techniques

Forehead feminization encompasses several distinct surgical approaches, each suited to different anatomical presentations. Understanding the fundamental differences between Type 1, Type 2, and Type 3 forehead contouring techniques is crucial for appreciating why a particular method is chosen for a patient’s forehead (Dr. MFO, 2025d). These distinctions lie in the underlying anatomy, the invasiveness of the procedure, the specific surgical steps, the degree of reduction possible, and the associated risks and recovery profiles.

Type 1 Forehead Contouring: The Simple Shave

Type 1 forehead contouring, often referred to as brow bone shaving or burring, represents the least invasive of the bone reduction techniques (Dr. MFO, 2025d). This method is appropriate for individuals with minimal brow bossing where the bone in the prominent area is relatively solid. This means the frontal sinus is either absent or very small, lying well behind the area of desired reduction (Dr. MFO, 2025d; Mittermiller, 2025). The procedure involves an incision, typically hidden along the hairline or within the hair, to access the frontal bone. Using specialized surgical burrs, the surgeon carefully shaves down the prominent outer layers of the frontal bone to create a smoother, more rounded contour.

The reduction achieved with Type 1 is limited by the thickness of the bone. Surgeons must avoid entering the frontal sinus cavity. This technique offers a less invasive approach, shorter surgical time, and generally faster recovery compared to Type 3. However, it cannot significantly change the overall projection or slope of the forehead bone itself (Dr. MFO, 2025d). Therefore, if significant brow bossing is present or the frontal sinus is large, Type 1 may yield an insufficient feminizing outcome.

Type 2 Forehead Contouring: The Augmentation Approach

Type 2 forehead contouring is a less common technique primarily considered for individuals with minimal brow bossing but a relative recession or flattening of the forehead bone superior to the brow ridge (Dr. MFO, 2025d). This creates a concave appearance that detracts from a feminine contour. The technique focuses on augmenting the area above the brow to create a smoother, more convex forehead profile.

Access is gained through a scalp incision. Any minimal brow bossing may be conservatively shaved, but the main objective is to add volume to the recessed area. Biocompatible materials, such as polymethyl methacrylate (PMMA) or hydroxyapatite cement, are meticulously sculpted and applied to the bone in the recessed area (Dr. MFO, 2025d). This material hardens in place, effectively reshaping the forehead profile.

Type 2 avoids entering or significantly manipulating the frontal sinus and can effectively address forehead recession. However, it does not directly reduce prominent brow bossing; it camouflages it by building up the surrounding area (Dr. MFO, 2025d). This method may not be suitable for significant brow bossing, and the use of artificial material introduces a low risk of infection or extrusion (Dr. MFO, 2025d).

Type 3 Forehead Contouring: The Osteotomy and Setback

As previously detailed, Type 3 forehead contouring is the most complex and robust technique. It is indicated for significant brow bossing, where simple shaving would be insufficient or unsafe due to a large or prominently projected frontal sinus (Dr. MFO, 2025d). This procedure fundamentally alters the supraorbital contour and achieves a profound feminizing effect by removing the anterior wall of the frontal sinus, reshaping it, and reattaching it in a more recessed position (Mittermiller, 2025).

Type 3 allows for the most significant reduction of brow bossing and comprehensive reshaping of the frontal bone, creating a smooth, convex, and appropriately sloped feminine forehead. It is often performed in conjunction with a brow lift and hairline lowering via the same incision, allowing for comprehensive upper face feminization (Dr. MFO, 2025d). However, it is more invasive, involves longer surgical times and recovery, and carries potential risks such as sinus infection or cerebrospinal fluid leak, which are rare but serious (Dr. MFO, 2025d).

A woman with short, wavy hair looking over her shoulder, posing against a dark background.

Comparative Outcomes, Complexity, and Recovery

The choice of technique is primarily dictated by the patient’s underlying anatomy, not merely preference. A surgeon’s assessment, often utilizing CT scans, is essential to determine the appropriate method (Dr. MFO, 2025d; Pansritum, 2021).

**Surgical Complexity:** Type 1 is the least complex, involving only surface burring. Type 2 is moderately complex, requiring careful material application. Type 3 is the most complex, involving bone cutting, reshaping, and precise fixation with plates and screws, demanding extensive craniofacial expertise (Dr. MFO, 2025e).

**Degree of Reduction:** Type 1 offers limited reduction. Type 2 camouflages recession. Type 3 provides the most significant and profound reduction and reshaping of brow bossing and forehead contour (Dr. MFO, 2025d).

**Recovery:** Type 1 typically has the fastest recovery with less swelling and bruising. Type 2 recovery is similar to Type 1. Type 3 involves a longer and more intensive recovery period, with more significant swelling, bruising, and potential discomfort due to the extensive bone work and manipulation of the frontal sinus (Dr. MFO, 2025d; Facialteam, 2025a). Numbness of the forehead and scalp is common across all types involving scalp elevation and can take many months to resolve.

**Long-Term Stability:** All forehead contouring results are generally permanent, as they involve reshaping the underlying bone or introducing stable augmentation material (Dr. MFO, 2025d; Kam, 2024). While the face continues to age, the fundamental bony changes remain. However, the comprehensive structural changes achieved with Type 3 tend to provide the most dramatic and lasting feminization for appropriate candidates.

A woman with short dark hair and striking blue eyes is smiling at the camera. She is positioned against a dark background with a bright light illuminating her face from below.

Intraoperative Decision-Making and Advanced Fixation Methods

Intraoperative decision-making during Type 3 forehead osteotomy is a dynamic process, requiring the surgeon to adapt the pre-planned strategy to real-time anatomical findings. While advanced imaging and virtual surgical planning provide a robust roadmap, unexpected variations in bone density, frontal sinus morphology, or the presence of fibrous scar tissue can influence the precise execution of osteotomies and the stability of fixation strategies (Dr. MFO, 2025e). The surgeon’s experience and deep anatomical knowledge are paramount for navigating these complexities and ensuring optimal outcomes.

Considerations During Osteotomy

During the osteotomy, continuous awareness of anatomical landmarks and vital structures is essential. The thickness of the anterior table of the frontal bone limits the extent of reduction through burring (Pansritum, 2021). When the frontal sinus is large or extends significantly, precise osteotomy around its boundaries is critical. Surgeons must exercise extreme caution to protect the supraorbital and supratrochlear nerves and vessels during the inferior cuts along the orbital rims, as injury can lead to permanent numbness or pain (Dr. MFO, 2025e).

Inadvertent entry into the frontal sinus, while sometimes necessary for adequate setback, requires meticulous management. The sinus mucosa must be completely removed, and the opening obliterated or covered to prevent mucocele formation and infection (Dr. MFO, 2025e). Furthermore, the depth of osteotomy must be carefully controlled, especially when approaching the inner table of the skull, to avoid dural tears and subsequent cerebrospinal fluid leaks, a rare but serious complication (Dr. MFO, 2025e).

Advanced Fixation Methods: Plates and Screws

After the bone segment is reshaped and repositioned, robust fixation is crucial for stability and proper bone healing. Modern Type 3 forehead setbacks primarily rely on plate and screw systems (Dr. MFO, 2025e). These systems offer superior stability compared to historical methods like wiring, promoting predictable bone union and minimizing complications.

**Materials:** Titanium is the most commonly used material due to its strength, biocompatibility, and non-ferromagnetic properties, which allow for MRI scans (Dr. MFO, 2025e). Absorbable (resorbable) plates and screws, made from polymers, are also an option. These dissolve over time, removing the need for potential secondary removal surgery, but they are less rigid and may be less suitable for the significant forces involved in Type 3 setback (Costa, 2023; Dr. MFO, 2025e).

**Plate Designs:** Plates come in various designs, including straight, L-shaped, and Y-shaped configurations, each adapted for different areas and fixation requirements (Dr. MFO, 2025e). Straight plates bridge linear osteotomy lines, while L-plates and Y-plates provide fixation at angles or complex geometries. Mesh plates, thin malleable sheets, are primarily used for contouring or augmenting irregular surfaces rather than primary load-bearing fixation.

**Screw Types:** Self-tapping screws, which create their own threads in a pre-drilled pilot hole, simplify insertion. Self-drilling screws combine drilling and tapping into one step. Bicortical screws, engaging both outer and inner bone layers, provide maximum stability where bone thickness allows. Monocortical screws, shorter and engaging only the outer layer, are used in thinner bone areas or near vital structures to avoid penetration (Dr. MFO, 2025e).

**Biomechanical Principles:** The primary goal of fixation is to provide mechanical stability, preventing unwanted movement at the osteotomy site. This promotes direct (primary) bone healing, which is faster and results in less callus formation, optimizing aesthetic outcomes. Plates and screws also ensure precise anatomical reduction, maintaining the planned forehead contour (Dr. MFO, 2025e). Proper selection of plate and screw size, strategic placement, and engagement of sufficient bone are critical to prevent hardware failure, such as plate bending or screw loosening. The hardware typically shares the load with the healing bone, gradually transferring load to the bone as it strengthens.

A woman with her hair tied up, looking to the side with a slight smile on her face.

Potential Complications and Their Management

Despite meticulous planning and execution, complex surgical procedures like Type 3 forehead osteotomy carry inherent risks and potential complications. Surgeons must be prepared to prevent, recognize, and effectively manage these challenges.

Intraoperative Complications

**Bleeding:** The scalp and bone are highly vascular, making significant bleeding a possibility. Careful hemostasis using cautery, bone wax, and hemostatic agents is crucial to maintain a clear surgical field and prevent postoperative hematoma (Dr. MFO, 2025e).

**Cerebrospinal Fluid (CSF) Leak:** This is a serious complication resulting from a tear in the dura mater, the protective membrane covering the brain. It can occur during bone cutting, especially in areas of thin bone or near the posterior wall of the frontal sinus. Meticulous surgical technique, precise drilling, and avoiding plunging instruments are critical for prevention. If a dural tear occurs, immediate repair with sutures, dural substitutes, or a vascularized pericranial flap is necessary (Dr. MFO, 2025e).

**Nerve Injury:** Injury to the supraorbital or supratrochlear nerves can lead to temporary or permanent numbness, pain, or paresthesia in the forehead and scalp. Careful identification and preservation of these neurovascular bundles during flap elevation and osteotomy are essential to minimize this risk (Dr. MFO, 2025e).

**Frontal Sinus Entry:** While often part of Type 3 setback, inadvertent or unplanned entry into the frontal sinus requires careful management. The sinus mucosa must be completely removed, and the opening obliterated or covered to prevent mucocele formation (a cyst-like lesion) and infection (Dr. MFO, 2025e).

**Orbital Injury:** Although rare, injury to the orbital contents, such as the eye or its muscles, can occur during the inferior osteotomy cuts along the supraorbital rim. Precise technique and thorough anatomical knowledge are paramount to avoid such complications (Dr. MFO, 2025e).

Postoperative Complications

**Infection:** Infection of the surgical site or the hardware (plates and screws) is a potential risk. Symptoms include redness, swelling, pain, warmth, and possible drainage. Management typically involves antibiotics and, in persistent cases, may require hardware removal (Dr. MFO, 2025e; Kam, 2024).

**Hematoma or Seroma:** Accumulation of blood (hematoma) or serous fluid (seroma) under the scalp flap can occur. Drains are often placed proactively to minimize this risk. Small collections may resolve spontaneously, while larger ones may necessitate aspiration or surgical drainage (Dr. MFO, 2025e).

**Hardware Palpability or Visibility:** In individuals with thin skin or limited subcutaneous tissue, plates or screws may become palpable or even visible. Careful hardware selection (low-profile plates) and meticulous countersinking of screws help minimize this. Sometimes, patients may request hardware removal after bone healing is complete (Dr. MFO, 2025e).

**Hardware Migration or Loosening:** Although less common with plate and screw fixation than with historical wiring methods, hardware can occasionally loosen or migrate if subjected to excessive force or if bone healing is impaired. This may necessitate surgical revision (Dr. MFO, 2025e).

**Non-union or Malunion:** Failure of the bone to heal (non-union) or healing in an incorrect position (malunion) can occur, although it is less likely with rigid fixation. Contributing factors include poor blood supply, infection, smoking, or inadequate fixation. Management often involves revision surgery with bone grafting and restabilization (Dr. MFO, 2025e).

**Aesthetic Issues:** Unpredictable healing, asymmetry, persistent contour irregularities, or inadequate setback can lead to an unsatisfactory aesthetic outcome. Comprehensive preoperative planning, precise execution, and realistic patient expectations are crucial to minimize such concerns (Dr. MFO, 2025e).

**Nerve Dysfunction:** Persistent numbness, tingling, or pain in the forehead or scalp can result from nerve stretching, compression, or injury during surgery. While sensation often improves over time, permanent changes are possible (Dr. MFO, 2025e; Pansritum, 2021).

**Pain:** Postoperative pain is expected and managed with analgesics. Chronic pain is rare but can occur (Dr. MFO, 2025e).

Management of Complications

A proactive approach to complication management is essential. This begins with careful patient selection and optimization, identifying and addressing any pre-existing medical conditions that could increase surgical risk (Dr. MFO, 2025e). Meticulous surgical technique, gentle tissue handling, and precise bone work are paramount. Appropriate hardware selection and secure application are also critical. Perioperative antibiotics help reduce the risk of infection. Close postoperative monitoring allows for early detection of complications and prompt intervention, ensuring patient safety and promoting a successful outcome (Dr. MFO, 2025e). Patient education regarding potential risks and recovery expectations is also vital for managing the journey effectively.

Post-Operative Recovery and Long-Term Management

The postoperative phase following Type 3 forehead osteotomy is a critical period that demands meticulous care and patience. Recovery from this extensive procedure is typically more protracted and can be more intense compared to less invasive interventions, given the significant bone manipulation, tissue reshaping, and potential for extensive swelling and bruising (Dr. MFO, 2025d). Patients must be thoroughly prepared for this journey, understanding that the immediate post-operative appearance will evolve considerably over weeks and months.

Immediate Post-Operative Period

Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort in the forehead and eye regions. Swelling is a universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week after surgery (Dr. MFO, 2025d; Kam, 2024). It gradually subsides over several weeks to months. Complete resolution of residual swelling, particularly in areas of significant bone work, can take up to a year or even longer for the final contours to fully emerge. Bruising will similarly resolve, usually within 2 to 4 weeks, transitioning through various colors before fading completely.

Pain management is crucial and is typically achieved through a combination of prescribed analgesia and anti-inflammatory medications. Diligent application of cold compresses, carefully applied to the forehead and eyes, helps minimize swelling and alleviate discomfort (Kam, 2024). Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce edema (Kam, 2024).

Activity Restrictions and Ongoing Care

Specific post-operative care instructions are meticulously tailored to the procedures performed. Patients are strongly advised to avoid strenuous activities, heavy lifting, and bending over for several weeks to minimize swelling and the risk of bleeding or hardware complications (Dr. MFO, 2025e; Kam, 2024). Gentle walking is encouraged to promote circulation. Gradually, activity levels are increased as recovery progresses and clearance is given by the surgical team.

Numbness of the forehead and scalp is a common experience after this type of procedure due to nerve manipulation during flap elevation. Sensation often gradually returns over many months to a year or more, though some areas of altered sensation may persist (Dr. MFO, 2025d; Pansritum, 2021). Regular follow-up appointments are essential for monitoring wound healing, assessing for signs of complications, and evaluating the aesthetic outcome (Dr. MFO, 2025e). The frequency of appointments decreases as the patient recovers.

Bone Healing and Soft Tissue Adaptation

Bone healing typically takes several months to a year, with significant strength gained within the first 6-12 weeks (Dr. MFO, 2025e). During this period, the plates and screws provide the necessary rigid stability for the bone segments to unite. Soft tissue adaptation involves the redraping of skin, muscle, and fat over the newly contoured skeletal framework. This process is gradual and contributes significantly to the naturalness of the final result. Lymphatic drainage massages may be recommended in later stages to help expedite the resolution of swelling and improve soft tissue suppleness (Facialteam, 2025a).

Long-Term Outcomes and Hardware Management

The long-term outcomes of Type 3 forehead osteotomy are generally considered permanent, as the procedure involves reshaping the underlying bone structure (Dr. MFO, 2025d; Kam, 2024). Once bone healing is complete and stable, the plates and screws have served their primary purpose of providing initial stability. In most cases, titanium hardware can remain in situ indefinitely without causing problems (Dr. MFO, 2025e). However, hardware removal may be considered in certain situations, such as if the hardware becomes palpable or sensitive, if an infection develops around it, or in rare instances of pain attributed to the hardware (Dr. MFO, 2025e). Hardware removal is a secondary procedure, generally less involved than the initial surgery.

While the extensive bone reshaping provides a stable and lasting foundation, facial structures continue to undergo natural aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey (Dr. MFO, 2025d).

A woman with dark hair and red lipstick poses against a colorful background, with her hand near her face.

Conclusion: The Precision of Forehead Transformation

Type 3 forehead osteotomy represents a highly advanced and transformative procedure within facial feminization surgery, offering a profound reshaping of the upper face for individuals seeking to align their appearance with their gender identity. This comprehensive exploration has illuminated the intricate layers of this procedure, from the foundational anatomical understanding to the meticulous surgical execution and the critical role of post-operative care. The distinguishing feature of Type 3 osteotomy is its capacity to address significant brow bossing and frontal sinus prominence through direct bone modification, a level of intervention unmatched by less invasive techniques. This ensures the creation of a smoothly contoured, feminine forehead that harmonizes with overall facial features.

The journey begins with extensive preoperative planning, leveraging high-resolution 3D imaging and virtual surgical simulation to create a precise blueprint for the transformation. This technological integration enhances surgical accuracy, minimizes risks, and significantly improves the predictability of outcomes. Intraoperative decision-making, while guided by this blueprint, demands a surgeon’s profound experience and adaptability to navigate individual anatomical variations and protect vital neurovascular structures. The application of advanced plate and screw fixation systems is paramount for achieving rigid stability, promoting optimal bone healing, and ensuring the long-term integrity of the reshaped frontal bone.

While Type 3 forehead osteotomy is a powerful tool for feminization, it is not without its complexities and potential challenges. Awareness of complications such as CSF leaks, nerve injury, or infection, and preparedness for their management, are integral to patient safety and surgical success. The postoperative recovery period is a crucial phase, requiring diligent care to manage swelling, discomfort, and activity restrictions, allowing for proper bone healing and soft tissue adaptation. The long-term stability of the results is generally excellent, providing a permanent change to the underlying bony framework.

Ultimately, the precision and artistry involved in Type 3 forehead osteotomy go beyond mere aesthetic enhancement; they contribute significantly to an individual’s psychological well-being, reducing gender dysphoria and fostering an enhanced sense of self-confidence and authenticity. Choosing a highly specialized surgeon with extensive experience in both aesthetic feminization and complex craniofacial reconstruction is the most critical decision for prospective patients. This ensures that the intricate needs of such an advanced procedure are met with the highest level of expertise and care. As surgical science and technology continue to evolve, the possibilities for achieving harmonious and feminized facial profiles will only expand, offering renewed hope and tangible results for those seeking profound personal transformation. We encourage individuals considering this life-changing procedure to seek detailed consultations with qualified experts to explore how Type 3 forehead osteotomy can help them achieve their desired feminine aesthetic.

Frequently Asked Questions

What is Type 3 forehead osteotomy in facial feminization?

Type 3 forehead osteotomy is an advanced surgical technique used in facial feminization surgery (FFS) to significantly reduce a prominent brow ridge and reshape the forehead. It involves surgically removing the anterior wall of the frontal sinus, reshaping this bone segment, and then repositioning it further back to create a smoother, more feminine contour.

Who is an ideal candidate for Type 3 forehead osteotomy?

An ideal candidate for Type 3 forehead osteotomy is an individual with significant brow bossing or a large, prominently projected frontal sinus. In these cases, simpler methods like bone shaving (Type 1) would be insufficient or unsafe. Preoperative imaging, such as a CT scan, helps confirm the need for this comprehensive approach.

How does Type 3 differ from Type 1 and Type 2 forehead contouring?

Type 3 involves bone cutting, reshaping, and setback for significant brow bossing. Type 1 (shaving) is for minimal bossing. Type 2 (augmentation) addresses forehead recession by adding material, rather than reducing prominence. Type 3 offers the most dramatic and comprehensive reshaping.

What are the primary steps involved in a Type 3 forehead osteotomy?

The procedure involves making a scalp incision (typically coronal) to expose the frontal bone. Precise osteotomies (bone cuts) are made to remove the anterior wall of the frontal sinus. This bone segment is then reshaped, the underlying bone is contoured, and the reshaped segment is set back to a feminine position and secured with plates and screws.

What types of fixation hardware are used in Type 3 forehead setback?

Titanium plates and screws are most commonly used due to their strength and biocompatibility, providing robust, long-lasting fixation. Absorbable (resorbable) plates and screws are also available but are generally less rigid and more often used in pediatric cases or less load-bearing areas.

What are the potential risks and complications of Type 3 forehead osteotomy?

Potential risks include bleeding, cerebrospinal fluid (CSF) leak (rare), nerve injury (leading to numbness or pain), frontal sinus infection, hematoma, seroma, hardware palpability, or, rarely, non-union of the bone. Careful surgical technique and postoperative care minimize these risks.

What can a patient expect during the recovery period after Type 3 forehead osteotomy?

Patients can expect significant swelling, bruising, and discomfort for several weeks. Full resolution of swelling and bone healing can take up to a year or more. Activity restrictions, head elevation, cold compresses, and prescribed pain medication are crucial. Numbness in the forehead and scalp is common and gradually resolves.

Bibliography

  • Costa, M. A. (2023). Forehead Feminization – Melinda A. Costa, M.D. Retrieved from Melinda A. Costa, M.D.: costamd.com
  • Dr. MFO. (2025d, May 10). FFS Forehead Contouring: Type 1, 2 & 3 Compared. Retrieved from Dr. MFO – FFS Surgeon in Turkey: dr-mfo.com
  • Dr. MFO. (2025e, May 15). Type 3 Forehead Setback FFS: Plate & Screw Bone Fixation. Retrieved from Dr. MFO – FFS Surgeon in Turkey: dr-mfo.com
  • Facialteam. (2025a, February 6). Type 3 Forehead Feminization Surgery: FOREContour® by Facialteam. Retrieved from Facialteam: facialteam.eu
  • Facialteam. (2025b). Forehead Feminization Surgery – The Forecontour® Technique. Retrieved from Facialteam: facialteam.eu
  • Kam, J. (2024, January 10). Forehead Contouring Type 3: Enhancing Facial Symmetry. Retrieved from Kam Facial Plastic Surgery: kamfacialplasticsurgery.com
  • Mittermiller, P. (2025). Type 3 Forehead Reduction for Forehead Feminization. Retrieved from Paul Mittermiller, MD: paulmittermillermd.com
  • Pansritum, K. (2021, March 22). Forehead and Hairline Surgery for Gender Affirmation. Plast Reconstr Surg Glob Open, 9(3): e3486.

Enduring Facial Feminization: Surgical Strategies for Long-Term FFS Stability

A young woman with dark hair is looking out of a window, with her hand resting on her chin, appearing thoughtful or contemplative.

Facial Feminization Surgery (FFS) represents a profound and life-changing journey for many individuals seeking to harmonize their outward appearance with their affirmed gender identity. While the immediate aesthetic transformations—such as softened facial contours, refined nasal structures, and balanced jawlines—are often the primary focus, the long-term structural integrity and stability of these results are equally paramount. The enduring success of FFS hinges on a complex interplay of biomechanical and biological processes, including skeletal remodeling, soft tissue adaptation, and the body’s intrinsic healing responses. Without a deep understanding of these fundamental mechanisms, even the most meticulously performed procedures may fall short of providing lasting satisfaction, potentially leading to relapse, asymmetry, or functional complications over time.

This comprehensive guide delves into the critical aspect of long-term biomechanical stability in FFS outcomes, extending beyond initial aesthetic achievements. We will meticulously explore how advanced surgical strategies and a profound understanding of facial biomechanics contribute to enduring results. This includes an examination of optimized bone contouring techniques, secure fixation methods, and the longevity of grafts and implants, all of which are essential for maintaining the feminized facial framework.

Furthermore, this analysis will address proactive strategies for mitigating potential long-term complications, such as bone resorption and soft tissue sagging, which can compromise the durability of surgical modifications. The pivotal role of precise preoperative planning, particularly through advanced three-dimensional virtual surgical planning (VSP) systems, and crucial intra-operative adjustments will be highlighted. These technologies enable surgeons to anticipate biomechanical stresses and design robust interventions, ensuring optimal load distribution and structural integrity in the newly sculpted face.

Consequently, we will examine the importance of diligent post-operative care and long-term monitoring as integral components of nurturing the transformation and ensuring its persistence. By understanding these intricate processes, both patients and practitioners can make informed decisions that enhance the longevity and overall success of FFS. This deep-dive aims to establish a definitive resource for comprehending the scientific foundations underpinning lasting FFS results, empowering individuals to navigate their journey with confidence and a clear vision for an enduring, harmonious future. This exploration goes beyond the superficial, establishing how the biological and mechanical foundations are critical for sustained aesthetic and functional excellence.

A dentist examining a patient's teeth using a dental tool.

The Biomechanics of a Feminized Face

Facial Feminization Surgery fundamentally alters the craniofacial skeleton and its surrounding soft tissue envelope to achieve a more feminine appearance. This involves reshaping the underlying bone structure, which in turn necessitates the adaptation of the overlying skin, muscles, and ligaments. The biomechanical integrity of the modified face is crucial for both aesthetic permanence and functional health. Understanding how various forces act upon these altered structures over time is essential for predicting and ensuring long-term stability.

The human face is constantly subjected to natural forces, including those generated by mastication, expressive movements, and the ever-present pull of gravity. These dynamic loads can influence the surgically modified facial skeleton, leading to changes such as bone remodeling and resorption. Therefore, surgeons must account for these biomechanical realities during planning and execution to ensure that the new contours remain stable and resilient. The body’s inherent ability to adapt to new forms, a process governed by specific biological principles, plays a significant role in the durability of surgical outcomes (Dr. MFO, 2025).

Bone remodeling is a continuous process where old bone tissue is removed and new bone tissue is formed. This allows the skeleton to adapt to mechanical stresses and maintain its structural integrity. In the context of FFS, bone remodeling influences how the reshaped areas of the forehead, jaw, and chin maintain their new form. Similarly, soft tissue adaptation, including the redraping of skin and muscles, is vital for a natural and harmonious aesthetic that resists sagging or undesirable changes over years.

Altering the Craniofacial Skeleton and Soft Tissue Envelope

FFS procedures modify the craniofacial skeleton, transforming masculine features into feminine ones. This includes reducing the brow ridge, reshaping the nose, contouring the jawline, and softening the chin. Each modification directly impacts the structural framework of the face. The new bone contours provide a distinct foundation, influencing the way soft tissues drape and settle (Dr. MFO, 2025). This delicate balance requires meticulous planning to ensure aesthetic harmony and structural stability.

The soft tissue envelope, comprising skin, subcutaneous fat, and muscles, must adapt to these underlying skeletal changes. For instance, after reducing a prominent brow, the forehead skin and brow muscles must redrape smoothly without creating irregularities. This adaptation is a dynamic biological process that continues for months, impacting the final appearance. Consequently, managing soft tissue elasticity and volume during surgery is as important as bone reshaping for long-term results.

Impact of Natural Forces: Mastication, Expressions, and Gravity

The human face is a complex biomechanical system constantly under various stresses. Forces from mastication apply significant loads to the jaw and chin, areas frequently targeted in FFS. Therefore, surgical modifications in these regions must withstand daily chewing forces without compromising stability. Similarly, repeated facial expressions engage numerous muscles, which exert continuous pull on the soft tissues and underlying bone.

Gravity also plays a relentless role, particularly in contributing to soft tissue sagging over time. Surgeons employ techniques to counteract these gravitational effects, such as careful soft tissue resuspension, to maintain youthful and feminine contours. Understanding these ongoing forces is crucial for designing a surgical plan that ensures durable outcomes. For instance, a bone reduction must leave sufficient structural support to resist natural biomechanical demands.

Bone Remodeling, Resorption, and Soft Tissue Adaptation

Bone is a living tissue capable of continuous self-renewal through remodeling, a process vital for maintaining skeletal health and adapting to mechanical loads. In FFS, this adaptation is essential for the longevity of reshaped bone structures. Wolff’s Law, a fundamental principle in bone biology, states that bone adapts its structure to the loads it is subjected to. This means that the bone in feminized areas will gradually reorganize to accommodate new stress patterns.

However, bone resorption, a process where bone tissue is broken down, can occur if areas are over-reduced or lack adequate blood supply, potentially compromising long-term contours. Therefore, surgical techniques are designed to minimize excessive resorption and promote healthy remodeling. Similarly, soft tissue adaptation involves the skin, muscle, and other connective tissues conforming to the new bone framework. This integration is crucial to prevent laxity, ensuring that the soft tissues appear taut and youthful over the long term (Dr. MFO, 2025). The maturation of scar tissue also plays a role in stabilizing these soft tissue envelopes.

A surgeon in an operating room, wearing protective gear, practices a procedure on a human skull model placed on a table next to surgical equipment.

Advanced Surgical Techniques for Structural Durability

Achieving lasting results in FFS necessitates the application of advanced surgical techniques that prioritize structural durability alongside aesthetic feminization. These methods are designed to ensure that the altered facial framework not only looks feminine but also maintains its integrity and stability against daily forces and the natural aging process. The selection of precise osteotomy techniques, robust fixation materials, and appropriate grafting strategies forms the cornerstone of this long-term success.

Optimized Bone Contouring: Preserving Strength While Feminizing

Bone contouring in FFS involves carefully reshaping the facial skeleton. For areas like the forehead, jaw, and chin, techniques are specifically chosen to reduce prominence while preserving bone strength. For instance, in forehead contouring, rather than removing an entire section of bone, a setback procedure might involve carefully removing, reshaping, and then reattaching the anterior wall of the frontal sinus. This maintains structural integrity while achieving a smoother, more feminine curve (Dr. MFO, 2025).

Similarly, jaw and chin reshaping procedures, such as mandibular angle reduction or genioplasty, require precise osteotomies that avoid compromising the structural load-bearing capacity of the mandible. Surgeons meticulously plan bone cuts and removals to ensure that the remaining bone mass is sufficient to withstand forces from chewing and speaking. This strategic approach prevents weakening of the bone, thereby reducing the risk of fracture or instability in the long term.

Secure Fixation Methods: Ensuring Stable Bone Segment Re-articulation

The stable re-articulation of bone segments after osteotomies is paramount for long-term stability. Modern FFS relies on advanced internal fixation methods using specialized plates, screws, and wires. These devices hold bone fragments firmly in their new positions, facilitating proper bone healing and fusion. Titanium plates and screws are commonly employed due to their biocompatibility and strength, providing reliable support during the critical healing phase (Shido et al., 2024).

The precise placement and type of fixation devices are selected based on the specific bone and the forces it will endure. For instance, in complex jaw or forehead modifications, robust fixation is essential to prevent micro-movements that could hinder bone union or lead to displacement. Studies on fixation stability, even in other areas of the skeleton like the femur, highlight the importance of optimal reduction position and implant design for reducing stress on the fixation device and the bone itself, particularly in areas of compromised bone density (Kim et al., 2024). This principle directly translates to facial skeletal modifications.

A close-up photograph of a person's lips, showcasing the details of the lips and surrounding skin.

Grafting and Implant Longevity: Predictable Integration and Durable Enhancement

In FFS, both autologous (patient’s own) bone and cartilage grafts and alloplastic (synthetic) implants are utilized to augment contours and add volume. The long-term success of these materials hinges on their predictable integration and durability. Autologous grafts, derived from areas like the rib or hip, are favored for their natural biocompatibility and capacity to integrate fully with the existing bone, becoming a living part of the facial skeleton (Dr. MFO, 2025). This integration minimizes the risk of rejection and provides the most stable, long-lasting augmentation.

Careful preparation of autologous grafts, including their vascularization, is crucial to ensure their survival and successful long-term remodeling. Advanced alloplastic implants, made from biocompatible materials like silicone or PEEK, offer durable contour enhancement, especially in areas where bone reduction is not feasible or additional projection is desired. These implants are often custom-designed using 3D imaging to precisely match the patient’s anatomy and desired aesthetic. Ensuring secure fixation of these implants is vital to prevent migration or displacement over time, contributing to their enduring presence and effect (Dr. MFO, 2025).

A close-up photograph of a person's face, focusing on their forehead and eyebrows. The image is taken from a low angle, capturing the person's eyes and the upper part of their face. The lighting is warm and soft, highlighting the skin texture and creating a serene atmosphere.

Mitigating Long-Term Complications Related to Biomechanics

Even with advanced surgical techniques, addressing potential long-term biomechanical complications is crucial for sustaining the results of FFS. These complications can arise from the body’s natural physiological responses to surgery, such as bone remodeling, or from external factors like gravity and daily facial movements. Proactive strategies during and after surgery are designed to minimize these risks and ensure the lasting aesthetic and functional integrity of the feminized face.

Addressing Bone Resorption: Minimizing Post-Operative Bone Loss

Bone resorption, a process where bone tissue is broken down, can occur naturally or be exacerbated by surgical interventions, particularly in areas of extensive bone reduction or grafting. In FFS, this is a concern in areas like the orbital rims, forehead, and jaw, where significant sculpting is performed. To mitigate bone loss, surgeons employ techniques that maintain adequate blood supply to the bone and preserve periosteum, the membrane covering the bone, which is rich in bone-forming cells.

Additionally, the choice of surgical technique plays a role; for example, precise burring or carefully planned osteotomies that do not excessively thin critical bone structures help to minimize future resorption. Post-operatively, patient adherence to nutritional guidelines, including adequate calcium and vitamin D intake, and avoidance of habits like smoking, which can impair bone healing, further supports bone stability (Dr. MFO, 2025). Regular follow-up allows for monitoring any signs of unexpected bone changes.

Preventing Soft Tissue Sagging: Combating Gravitational Effects

Soft tissue sagging is a natural consequence of aging and gravity, which can be a particular concern after FFS as tissues redrape over a new skeletal framework. Surgical strategies to counteract this include meticulous soft tissue redraping and resuspension techniques. During surgery, excess skin and subcutaneous tissue may be carefully removed or repositioned and secured to deeper, more stable structures, such as the periosteum or deep fascia, especially in areas like the neck and jawline (Dr. MFO, 2025).

Techniques such as brow lifts, midface lifts, and neck lifts may be integrated or performed as staged procedures to maintain youthful and taut contours. The goal is to achieve not just an immediate lift but a long-term suspension that resists gravitational pull. Post-operative care, including the use of compression garments and specific massage techniques, can also aid in optimal tissue adherence and minimize swelling, contributing to the desired long-term aesthetic.

Maintaining Implant Stability: Preventing Migration or Exposure

For FFS procedures that involve alloplastic implants for contour enhancement, ensuring their long-term stability is critical. Potential complications include implant migration, where the implant shifts from its intended position, or exposure, where it becomes visible or erodes through the skin. Surgeons prevent these issues through secure fixation methods, such as using small screws to anchor implants directly to the bone.

The precise anatomical placement of implants, ensuring they are well-covered by soft tissue, is also vital to reduce the risk of exposure. Furthermore, the selection of highly biocompatible implant materials minimizes adverse tissue reactions that could lead to inflammation or capsule formation around the implant, both of which can compromise stability (Dr. MFO, 2025). Regular follow-up allows the surgeon to monitor implant integrity and address any concerns early.

Role of Pre- and Intra-operative Planning

The enduring success of FFS is significantly shaped by the precision and foresight applied during the pre-operative and intra-operative phases. Advanced planning, particularly through digital technologies, allows surgeons to anticipate biomechanical challenges and craft surgical strategies that prioritize both aesthetic goals and structural durability. This meticulous approach minimizes guesswork and enhances the predictability of long-term outcomes.

3D Virtual Surgical Planning (VSP): Anticipating Biomechanical Stress

Three-dimensional virtual surgical planning (VSP) has revolutionized FFS, offering an unparalleled level of precision in preoperative assessment. Utilizing high-resolution CT scans, VSP software creates a detailed digital model of the patient’s craniofacial anatomy. Within this virtual environment, surgeons can perform simulated osteotomies, bone reductions, and implant placements, visualizing the exact changes before any physical incision (Dr. MFO, 2025).

VSP allows for biomechanical analysis, enabling surgeons to predict how changes to the bone structure might affect load distribution and stress points. This foresight is crucial for designing a robust surgical plan that avoids areas of excessive biomechanical stress, which could lead to bone resorption or implant failure. By precisely measuring and planning each modification, VSP helps to ensure that the feminized face will be aesthetically pleasing and structurally sound over the long term. Studies on fracture fixation in other skeletal regions underscore the value of such detailed planning for optimizing stability and reducing implant stress (Kim et al., 2024).

Intra-operative Adjustments: Ensuring Optimal Load Distribution and Structural Integrity

Despite comprehensive preoperative planning, intra-operative adjustments are often necessary due to the inherent variability of human anatomy and individual tissue responses. A skilled FFS surgeon possesses the experience and judgment to make these real-time modifications while maintaining the overarching goals of structural integrity and aesthetic harmony. This adaptability is vital, especially when dealing with complex bone morphology or unexpected findings (Hollensteiner et al., 2025).

Intra-operative verification techniques, such as direct visual inspection and palpation, ensure that bone reductions and advancements are balanced and achieve optimal load distribution. For example, when reducing the jaw or chin, the surgeon ensures that the remaining bone provides adequate support and avoids creating areas of weakness. Similarly, during forehead contouring, precise bone work is confirmed to maintain structural strength while achieving the desired feminine curvature. These adjustments are critical for preventing biomechanical instabilities that could compromise long-term results.

Post-Operative Care and Monitoring for Enduring Results

The post-operative period following FFS is a crucial phase that directly impacts the long-term biomechanical stability and aesthetic durability of the surgical outcomes. Meticulous care and consistent monitoring are essential to support the healing process, manage potential complications, and ensure the sustained success of the transformation. Patients play an active role in this phase through adherence to specific care protocols and lifestyle choices.

Supporting Long-Term Biomechanical Stability

Post-FFS recovery involves more than just managing swelling and discomfort; it also centers on supporting the biomechanical stability of the newly structured face. Patients are typically advised to avoid strenuous activities, heavy lifting, and any movements that could exert undue pressure or stress on the healing bone and soft tissues. This includes careful dietary modifications, such as consuming soft foods, especially after jaw or chin procedures, to minimize strain during mastication (Dr. MFO, 2025).

Head elevation, particularly during sleep, is strongly recommended for several weeks. This helps to reduce swelling and promote proper lymphatic drainage, which in turn supports optimal tissue redraping and adherence. Protecting the face from accidental trauma is also paramount during the initial healing phases, as any impact could compromise the stability of bone segments or implants. These measures collectively foster an environment conducive to strong bone union and stable soft tissue integration.

The Role of Long-Term Follow-Up

Long-term follow-up appointments with the surgical team are indispensable for monitoring facial changes and addressing any evolving structural concerns. These regular check-ups allow the surgeon to assess the healing process, evaluate the stability of bone modifications and implants, and track the ongoing adaptation of soft tissues (Dr. MFO, 2025). Any signs of bone resorption, implant migration, or unforeseen tissue laxity can be identified early and managed appropriately.

During these appointments, patients can also discuss any persistent symptoms or aesthetic concerns, allowing for timely intervention if needed. The surgeon may recommend adjunctive treatments, such as injectables for volume maintenance, or minor revision procedures to address age-related changes that naturally occur over many years. This continuous oversight ensures that the patient’s initial investment in FFS yields enduring satisfaction, adapting the results to the natural progression of aging.

A woman with short, wavy hair and striking features is captured in a portrait. She is wearing a light-colored, lace top and is positioned outdoors with a blurred, natural background. The lighting highlights her face, creating a dramatic and elegant atmosphere.

Conclusion: A Foundation for Lasting Femininity

The achievement of lasting Facial Feminization Surgery outcomes is profoundly rooted in a comprehensive understanding and meticulous application of biomechanical and biological principles. This extensive exploration has underscored that enduring transformation extends far beyond the immediate aesthetic changes, demanding a deep appreciation for how the body’s tissues, particularly the bone and soft tissues, respond to surgical modification over time. From the dynamic process of skeletal remodeling, guided by principles like Wolff’s Law, to the intricate adaptation of the soft tissue envelope, every biological response plays a critical role in preserving the stability and natural appearance of a feminized face.

The advancements in surgical precision are paramount, with optimized bone contouring techniques designed to maintain structural strength while achieving delicate feminine forms. Secure fixation methods, employing biocompatible plates and screws, are essential for robust bone segment re-articulation and graft integration. The careful selection and preparation of autologous grafts, alongside the strategic placement of advanced alloplastic implants, further contribute to durable contour enhancement, minimizing risks such as resorption or migration. These technical pillars, combined with a proactive approach to mitigating long-term complications like tissue sagging, form the bedrock of successful, long-lasting results.

Crucially, the integration of cutting-edge preoperative planning tools, such as 3D virtual surgical planning, enables surgeons to foresee and address potential biomechanical stresses, allowing for a tailored approach that maximizes both safety and predictability. Intra-operative adaptability ensures that the surgical plan is executed with precision, making necessary adjustments to optimize load distribution and structural integrity in real-time. This synergistic blend of foresight and skilled execution is indispensable for crafting a facial architecture that withstands the tests of time and natural forces.

Furthermore, the journey toward lasting feminization extends into the post-operative period, where diligent patient care and consistent, long-term monitoring are vital. Adherence to post-surgical guidelines, coupled with regular follow-up appointments, allows for the early detection and management of any evolving structural concerns, ensuring the sustained harmony of the feminized features. This continuous engagement ensures that the initial surgical triumph translates into years of confident self-presentation and enhanced psychological well-being.

Ultimately, the profound success of Facial Feminization Surgery lies in its ability to create results that are not only aesthetically congruent with an individual’s identity but also biomechanically stable and resilient. It is a testament to the intricate balance between surgical artistry and scientific rigor, offering individuals a genuine foundation for lasting femininity. This integrated approach, prioritizing enduring structural integrity, will continue to define the highest standards of care in this transformative field.

Frequently Asked Questions

What is biomechanical stability in FFS?

Biomechanical stability in Facial Feminization Surgery refers to the ability of the reshaped facial bones and tissues to maintain their new form and function over time, resisting natural forces like chewing, expressions, and gravity. It ensures results are durable and functional.

How does bone remodeling contribute to long-term FFS results?

Bone remodeling is a natural process where bone continuously renews itself. After FFS, the body’s bones adapt to new mechanical stresses, helping the reshaped areas maintain strength and stability in their feminized contours according to Wolff’s Law.

What role do fixation devices play in FFS?

Fixation devices, such as titanium plates and screws, secure bone segments in their new positions after osteotomies. They provide crucial stability during the healing process, ensuring proper bone fusion and preventing displacement for long-term structural integrity.

How do surgeons prevent soft tissue sagging after FFS?

Surgeons employ meticulous soft tissue redraping and resuspension techniques during FFS. They may also remove excess skin or secure tissues to deeper, more stable structures to counteract gravitational effects and maintain youthful, taut contours over many years.

What is the importance of 3D virtual surgical planning (VSP) in FFS?

3D VSP utilizes high-resolution imaging to create a virtual model of the patient’s face, allowing surgeons to simulate procedures and predict biomechanical stress points. This precise planning ensures optimal load distribution, enhances accuracy, and improves the predictability of long-term outcomes.

How can patients ensure the longevity of their FFS results?

Patients can enhance longevity by strictly following post-operative care instructions, avoiding strenuous activities, maintaining a healthy lifestyle, and attending regular long-term follow-up appointments. This supports healing and allows for early management of any concerns.

What are the potential long-term complications related to FFS biomechanics?

Potential complications include bone resorption (loss of bone volume), soft tissue sagging due to gravity or aging, and implant migration or exposure. Advanced surgical techniques and meticulous post-operative care aim to minimize these risks.

Personalizing Feminization: 7 Amazing Ways Unique Anatomy Shapes FFS Strategy

A woman with her eyes closed, appearing to be in a state of relaxation or meditation, with sunlight gently illuminating her face.

Facial Feminization Surgery (FFS) represents a deeply intricate and profoundly personal journey, offering a transformative pathway for individuals seeking to align their external appearance with their affirmed feminine identity. This highly specialized field within craniofacial and plastic surgery transcends mere aesthetic enhancements, demanding a meticulous, individualized approach that acknowledges the profound and inherent variations in human facial anatomy. The fundamental principle guiding successful facial feminization is the understanding that no two faces are identical, nor do they present the same set of masculine characteristics to be addressed. Therefore, a “one-size-fits-all” methodology is inherently inadequate for achieving optimal, natural-looking, and deeply satisfying results. Instead, the process necessitates a bespoke surgical strategy meticulously tailored to each patient’s unique underlying skeletal and soft tissue architecture, which is a complex interplay of genetic predisposition, developmental factors, and the effects of hormonal influences.

This comprehensive guide will delve into the critical role of distinctive facial anatomy in shaping the precise surgical interventions and techniques employed during FFS, underscoring how a nuanced appreciation of individual features culminates in a truly personalized and effective transformation. We will explore how expert surgeons navigate the complex landscape of craniofacial differences between sexes, which range from the subtle contours of the brow to the more pronounced angles of the jaw, and how these anatomical nuances directly inform the selection and execution of feminizing procedures. The objective is not merely to soften overtly masculine traits but to sculpt a cohesive and balanced facial appearance that authentically reflects the individual’s gender identity, thereby enhancing psychological well-being, alleviating gender dysphoria, and facilitating social affirmation (Barnett et al., 2023).

This exploration will highlight the advanced diagnostic tools, such as high-resolution 3D imaging and sophisticated virtual surgical planning systems, that empower surgeons to create a detailed, three-dimensional blueprint of the patient’s face. This technological integration enables an unprecedented level of precision in preoperative strategizing, allowing for simulated outcomes and customized surgical guides. Furthermore, we will examine how various surgical techniques, encompassing both osseous (bone) modifications—which address the fundamental framework of the face—and soft tissue refinements—which provide the delicate finishing touches—are synergistically integrated to produce a harmonious outcome that maintains naturalness while achieving profound feminization.

The discussion will extend to the critical considerations involved in managing patient expectations, ensuring they are grounded in surgical realism, and understanding the unique challenges posed by significant anatomical variations. We will also emphasize the paramount importance of selecting a highly experienced specialist who possesses a deep understanding of both aesthetic principles and complex craniofacial reconstruction. Ultimately, this detailed analysis aims to illuminate the profound interplay between individual facial anatomy and surgical artistry, revealing how a deeply personalized approach is not just beneficial, but absolutely the cornerstone of transformative, durable, and profoundly impactful facial feminization outcomes.

A surgeon wearing a mask holds a holographic representation of a face, which is labeled with various measurements and points of interest, such as VSP, 530, 2200, 76mm, and 6mm.

Understanding the Blueprint: Foundational Anatomy for Facial Feminization

Before any surgical intervention commences, a profound understanding of the patient’s foundational facial anatomy is paramount. A skilled facial feminization surgeon meticulously assesses the intricate interplay of underlying bone and overlying soft tissue structures. This comprehensive evaluation is critical because inherent differences in skeletal proportions and soft tissue distribution are key determinants of perceived gender.

Typically, masculine facial features often involve a more prominent brow ridge, a broader and squarer jawline, a larger and more anteriorly projected chin, and a distinct nasal profile characterized by a higher bridge and less upward rotation of the tip. However, the degree of expression of these features varies significantly among individuals due to genetic, ethnic, and developmental factors (Alraddadi, 2021). Recognizing these individual anatomical nuances is not merely an observational step but the foundational prerequisite for crafting a truly tailored and effective surgical plan.

To acquire this detailed anatomical blueprint, advanced diagnostic imaging plays an indispensable role. Three-dimensional computed tomography (3D CT) scans are frequently employed, providing a high-resolution, three-dimensional reconstruction of the patient’s unique skeletal and soft tissue architecture. These scans offer an unparalleled view of bone density, sinus pneumatization, nerve pathways, and the precise contours of the facial skeleton (Barnett et al., 2023). This data is then utilized in conjunction with virtual surgical planning (VSP) software, allowing surgeons to precisely measure existing structures and simulate potential surgical modifications.

Beyond static images, dynamic assessments of soft tissue mobility, skin elasticity, and muscle activity are also incorporated. Understanding the variations in tissue thickness and elasticity, for instance, is crucial for anticipating how overlying soft tissues will redrape following bone reductions or augmentations. The combination of comprehensive physical examination and advanced imaging provides the surgeon with a holistic understanding of the patient’s facial landscape, enabling them to formulate a feminization strategy that is both anatomically sound and aesthetically harmonious, moving beyond generic ideals to achieve results that are authentic to the individual.

A close-up photograph of a person's face, focusing on their eyes, with sunlight casting a warm glow on their face.

Regional Deep Dive: Anatomical Impact on Specific Feminization Techniques

The Forehead and Orbital Rims: Sculpting a Feminine Foundation

The upper third of the face, comprising the forehead and orbital rims, is a primary region for gender recognition. Variations in the frontal bone and supraorbital ridge (brow bone) are among the most significant sexually dimorphic features. Masculine foreheads often present with a prominent brow bossing, a heavier and more horizontally positioned brow relative to the superior orbital rim, and a forehead that recedes backward. In stark contrast, feminine foreheads are typically characterized by a smoother, rounder contour, a more vertically oriented profile, and eyebrows that arch higher, positioned above the orbital rim (Barnett et al., 2023). The degree of frontal bossing can vary considerably among individuals, directly impacting the complexity and choice of surgical intervention.

These anatomical variations directly influence the selection of forehead contouring procedures, primarily categorized into Type 1 (shaving), Type 2 (combination), or Type 3 (setback) techniques. For individuals with a relatively thick anterior frontal sinus wall and less pronounced bossing, a Type 1 procedure, involving direct burring or shaving of the prominent bone, may suffice to create a smoother transition. However, when the frontal sinus bone is thinner or the brow bossing is significantly prominent, a more extensive approach is often necessitated.

A Type 3 cranioplasty, also known as frontal sinus setback, involves carefully removing the anterior wall of the frontal sinus, meticulously reshaping it, and then reattaching it in a more recessed and feminized position (Barnett et al., 2023). This reconstructive technique allows for a greater degree of reduction and a more profound feminizing effect, fundamentally altering the supraorbital contour and achieving the desired convex curvature of a feminine forehead.

In conjunction with forehead contouring, orbital rim contouring is frequently performed to further enhance upper facial feminization. In masculine faces, the bony edges around the eye sockets can appear heavier and more angular, often casting shadows that masculinize the eyes. By carefully smoothing and rounding these edges, the eyes appear larger, more open, and less shadowed, contributing to a softer, more inviting gaze. The precise execution of these modifications, especially near critical structures such as the supraorbital and supratrochlear nerves, is paramount to prevent sensory deficits.

Additionally, the natural hairline position and any existing brow descent will guide the selection of brow lift techniques. A coronal incision, extending across the scalp, may be chosen for significant hairline advancement combined with forehead contouring, whereas an endoscopic brow lift, utilizing smaller incisions within the hairline, can achieve brow elevation with minimal hairline change, particularly when hairline lowering is not a primary objective. Virtual surgical planning, as detailed by Barnett et al. (2023), has emerged as an indispensable tool, allowing surgeons to precisely visualize desired outcomes and plan osteotomies with enhanced accuracy, significantly reducing operative time and minimizing complications like over-resection or nerve injury. This meticulous pre-surgical mapping ensures that the altered contours integrate seamlessly with the rest of the face, providing a harmonious and distinctly feminine upper facial aesthetic.

A close-up portrait of a person's face with a split color effect, one side in blue and the other in red, highlighting the lips and facial features against a dark background.

Midface and Cheeks: Sculpting Softness and Projection

The midface, prominently defined by the zygomatic (cheekbone) complex and the overlying soft tissues, plays a pivotal role in the perception of facial femininity and youthfulness. Significant variations exist in midface projection and contour between masculine and feminine physiognomies. Masculine midfaces often exhibit flatter zygomas with less anterior projection, contributing to a less triangulated facial shape. In contrast, feminine cheeks are typically characterized by higher, more anteriorly positioned zygomatic arches, creating a desirable convexity and contributing to a softer, more youthful, and often “heart-shaped” facial contour (Barnett et al., 2023). The distribution and volume of subcutaneous fat, including the malar fat pad and buccal fat, also vary considerably, further influencing overall midface appearance.

Surgical strategies for midface feminization are highly individualized, contingent upon the patient’s existing anatomical structure and desired aesthetic. When there is insufficient malar projection or a naturally flatter midface, cheek augmentation is often recommended. This can be achieved through various methods. Autologous fat grafting, which involves harvesting fat from other areas of the patient’s body (e.g., abdomen or thighs) via liposuction, processing it, and then injecting it into the cheeks, offers a natural solution. This technique provides a soft, natural-looking augmentation and can simultaneously improve the quality of the overlying skin. Alternatively, custom alloplastic implants, typically made of biocompatible materials such as silicone, can be placed over the cheekbones to provide permanent volume and definition. These implants are either pre-designed or custom-fabricated based on 3D virtual surgical planning to precisely match the desired contours (Barnett et al., 2023).

Conversely, in rare instances where cheekbones are excessively wide or prominently angled in a masculine manner, a surgeon might consider zygomatic arch reduction to soften the midface width. Furthermore, the distribution of buccal fat—a deep fat pad located within the cheek—can impact facial fullness. For individuals with a fuller, rounder lower face that detracts from a feminine aesthetic, buccal fat pad removal may be considered to create a more defined and hollowed submalar region, enhancing the appearance of higher cheekbones.

The delicate interplay between these procedures allows for the creation of an “ogee curve”—a graceful, double S-curve contour from the temple to the cheek, which is highly indicative of youthful, feminine cheeks. When combining nose and cheek procedures, as highlighted by Dr. MFO (2025b), synergistic anatomical planning is critical due to the interdependence of nasal and midface aesthetics. An overly prominent nose, for example, can make the midface appear recessed, while well-projected cheekbones can visually balance a nose. Therefore, modifications in one area profoundly influence the perception of the other, requiring an integrated approach to achieve overall facial harmony.

The Nose: Achieving Delicate Proportions

The nose, positioned centrally on the face, is a critical feature that significantly influences overall facial balance and perceived gender. Nasal structures exhibit immense diversity, yet distinct patterns contribute to gender recognition. Masculine noses often feature a broader nasal bridge, a more prominent dorsal hump, wider nostrils (alar base), and a less upwardly rotated, sometimes even downwardly projecting, nasal tip. In contrast, feminine noses are typically characterized by a smaller overall size, a narrower bridge, a softer or slightly concave dorsal profile, and a more refined, slightly upturned nasal tip, contributing to a more obtuse nasolabial angle (Barnett et al., 2023).

This wide spectrum of nasal anatomy necessitates a comprehensive range of rhinoplasty techniques during facial feminization. Dorsal hump reduction is a common procedure, involving the careful removal or rasping of excess bone and cartilage along the nasal bridge to create a smoother, more delicate profile. Concurrently, narrowing the nasal bones through osteotomies (controlled bone cuts) helps to reduce the overall width of the nasal bridge, contributing to a more refined appearance. Tip plasty techniques are pivotal for feminizing the nasal tip; these involve meticulous reshaping of the lower lateral cartilages through excisions, sutures, and grafts to make the tip smaller, more defined, and appropriately rotated upward (Barnett et al., 2023). Alar base reduction may be performed to narrow excessively wide nostrils, which can be a masculine characteristic, ensuring the nasal base is proportionate to the feminized tip and bridge. The specific aims are to create a nose that harmonizes with the newly contoured forehead and midface, avoiding an overly aggressive or artificial appearance.

An open rhinoplasty approach, utilizing a small incision across the columella and internal incisions, is often favored in facial feminization due to the optimal access and visibility it provides to the underlying skeletal and cartilaginous framework. This allows the surgeon to precisely manipulate structures and address specific feminizing goals, such as caudal septal trimming for upward tip rotation (Barnett et al., 2023). The intricate relationship between the bony and cartilaginous components of the nose demands a highly skilled surgeon to achieve stable and aesthetically pleasing results.

Furthermore, the soft tissue envelope, comprising skin, subcutaneous fat, and muscle, plays a significant role in the final outcome; its thickness and elasticity determine how readily underlying changes will be revealed. Consideration of the nasal vascular supply, primarily from branches of the ophthalmic and facial arteries, and innervation from the trigeminal nerve, is crucial to minimize complications such as bleeding or sensory changes. The ultimate goal is to sculpt a nose that is in harmonious proportion with the overall feminized facial features, enhancing the patient’s self-perception and social comfort (Dr. MFO, 2025c).

Jawline and Chin: Softening the Lower Face

The lower third of the face, particularly the jawline and chin, are primary indicators of sexual dimorphism and significantly contribute to perceived gender. Masculine jawlines are typically broader, squarer, and more angular, often presenting with prominent mandibular angles and a thicker external oblique ridge. The chin in masculine faces can be wider, squarer, or excessively prominent, contributing to a strong, sometimes blunt, lower facial appearance. Conversely, feminine jawlines are generally narrower, more tapered, and often exhibit a graceful V-shape or oval contour with softer angles. The chin in feminine faces is typically more delicate, with less width and projection, contributing to a refined lower facial profile (Barnett et al., 2023).

Surgical strategies for feminizing the jawline and chin involve meticulously tailored osseous modifications. Mandibular angle reduction is a key procedure designed to soften the posterior jawline. This involves carefully shaving or resecting a portion of the bone at the prominent jaw angles, transforming a square contour into a smoother, more tapered transition from the ear to the chin. This procedure is often performed through intraoral incisions (inside the mouth) to avoid visible external scarring, allowing for precise osteotomy and contouring while mitigating damage to vital structures such as the inferior alveolar nerve (Barnett et al., 2023).

Chin reshaping, or genioplasty, addresses the size, projection, and shape of the chin. In facial feminization, the goal is often to reduce chin width, shorten its vertical height if it is excessively long, and/or reshape it to a more pointed or rounded form, depending on the patient’s desired outcome and existing anatomy. A common technique is the sliding genioplasty, where the chin bone is carefully cut horizontally, and the distal segment is repositioned. This segment can be moved backward for reduction, advanced for increased projection, vertically shortened, or narrowed to achieve the desired delicate, feminine contour. The repositioned bone segment is then secured with small plates and screws to ensure stability and predictable healing (Barnett et al., 2023).

For chins that primarily require reduction in width or projection without significant repositioning, direct bone shaving or burring can be performed. The integration of these procedures often culminates in a “V-line” surgery, which combines mandibular angle reduction and genioplasty to create a significantly more tapered and feminine lower facial silhouette. In some cases, masseter muscle reduction, either surgically or through botulinum toxin injections, may also be considered for individuals with hypertrophied (enlarged) jaw muscles contributing to excessive lower facial width. The combined effect of these carefully planned interventions results in a more graceful, harmonious, and distinctly feminine lower face, balancing the features modified in the upper and mid-face (Dr. MFO, 2025a).

The Trachea: A Smoother Neckline

The laryngeal prominence, commonly known as the Adam’s apple, is a distinct secondary sex characteristic that develops and becomes more prominent during male puberty due to the enlargement and acute angle of the thyroid cartilage. Its presence can be a significant source of gender dysphoria for many transgender women, as it is a highly visible feature immediately indicative of a masculine neck profile. A tracheal shave, also known as chondrolaryngoplasty, is a straightforward yet highly effective feminizing procedure specifically designed to reduce the size and prominence of the Adam’s apple (Barnett et al., 2023).

The procedure typically involves making a small, discreet transverse incision in a natural skin crease on the neck, often at the midpoint between the submental crease and the cervicomental angle, to minimize the visibility of any resulting scar. Through this incision, the surgeon carefully shaves down the most prominent part of the thyroid cartilage, reducing its projection and creating a smoother, softer contour of the neck. Extreme care is taken to preserve a rim of cartilage superior to the level of the vocal cords for stabilization and, crucially, to avoid damaging the vocal cords themselves, which are located just behind the cartilage (Barnett et al., 2023). This meticulous approach ensures that vocal function is preserved. While primarily a modification of cartilage, which is a form of skeletal tissue, the tracheal shave profoundly impacts the overall appearance of the neck and profile, contributing to a more feminine silhouette and alleviating a significant source of dysphoria.

The recovery from a tracheal shave is generally quicker than from more extensive bone procedures, with most acute swelling and discomfort subsiding within a few weeks. Patients may experience some temporary voice changes or a sensation of tightness immediately after the surgery, but these usually resolve as the healing progresses. In some cases, submental fat excision and platysmaplasty (neck muscle tightening) may be performed concurrently to further enhance the desired neck silhouette and achieve maximal skin tightening, especially in older patients where skin laxity is a greater concern (Barnett et al., 2023). For many individuals, achieving a smoother neckline provides immense psychological relief, allowing them to feel more comfortable and confident in their appearance, particularly when wearing clothing that exposes the neck. This relatively contained procedure offers a significant impact on overall gender affirmation by addressing one of the most visible masculine features of the head and neck region.

A close-up portrait of a woman with smooth skin and closed eyes, set against a dark background.

Integrating Techniques for Holistic Feminization: The Art of Synergy

True facial feminization rarely involves a singular procedure. Instead, it is an intricate symphony of coordinated surgical interventions, each meticulously planned to complement the others and holistically address the patient’s unique anatomy. The skilled surgeon acts as an architect, orchestrating a series of modifications—ranging from fundamental bone restructuring to subtle soft tissue refinements—to achieve a balanced, harmonious, and naturally feminine outcome. This integrated approach ensures that the overall result is cohesive and congruent with the patient’s gender identity, rather than a collection of isolated, disconnected changes. The synergy between procedures is paramount, as altering one facial component inevitably influences the perception and aesthetics of adjacent and distant features.

For instance, a reduction in brow bossing not only feminizes the forehead but also optically enlarges the eyes, making a subtle rhinoplasty’s impact even more pronounced. Similarly, jawline and chin reshaping procedures provide a narrower foundation, over which soft tissues drape more delicately, enhancing the effect of cheek augmentation and lip lifts. The thoughtful sequencing and combination of these techniques are what elevate facial feminization from mere surgical alteration to a sophisticated art form.

The decision for a comprehensive, single-stage facial feminization surgery versus a staged approach (multiple surgeries performed over time) is heavily influenced by the anatomical complexity of the case, the patient’s overall physical health, and personal preferences. While a single-stage procedure offers the convenience of one recovery period and often significant cost savings, patient safety remains the ultimate priority. Studies indicate that an increased number of procedures performed per anesthetic event in facial feminization patients does not necessarily predict higher complication rates, suggesting that well-planned, comprehensive single-stage approaches can be safely undertaken under appropriate medical judgment (Barnett et al., 2023).

However, for individuals with extensive surgical needs, significant medical comorbidities, or those who prefer to recover from smaller interventions sequentially, a staged approach may be more appropriate. In such cases, structural hard tissue procedures like frontal sinus setback, supraorbital contouring, jawline tapering, and rhinoplasty are often prioritized, followed by subsequent soft tissue procedures like facelifts, neck lifts, and blepharoplasty, particularly in older patients where skin laxity is a consideration (Barnett et al., 2023). This strategic sequencing ensures that the foundational skeletal changes are established before refining the overlying soft tissues, thereby optimizing both the aesthetic and functional outcomes. Regardless of the staging strategy, the overarching goal is to achieve seamless integration, where each surgical modification contributes harmoniously to the final feminine facial contour.

Preoperative Planning and Technological Advancements for Precision

The success of advanced facial feminization surgery, particularly in cases involving significant anatomical variations, hinges critically on comprehensive and precise preoperative planning. This crucial phase has undergone a profound revolution with the integration of cutting-edge imaging modalities and virtual technologies, offering an unprecedented level of accuracy and predictability. High-resolution imaging, such as Cone-Beam Computed Tomography (CBCT) and standard Computed Tomography (CT) scans, provides detailed three-dimensional anatomical data of the patient’s skull and overlying soft tissues (Barnett et al., 2023).

This granular data is absolutely essential for an accurate diagnosis of existing skeletal differences, including bone volume deficits, subtle asymmetries, malposition of facial segments, and a precise assessment of critical underlying structures such as nerve pathways and sinus cavities. The detailed understanding derived from these images forms the fundamental bedrock upon which the entire surgical strategy is built, allowing surgeons to meticulously map out the existing anatomy and pinpoint all areas requiring correction or augmentation.

Building upon this rich imaging data, three-dimensional virtual surgical planning (VSP) systems have become indispensable tools in contemporary facial feminization. VSP involves importing the patient’s CT or CBCT data into specialized software, where a precise 3D digital model of the face and skull is generated. Within this sophisticated virtual environment, surgeons can meticulously plan every osteotomy (bone cut), bone graft placement, and custom implant positioning. This digital platform allows for the simulation of various surgical scenarios, enabling surgeons to virtually adjust bone segment movements, refine contours, and visualize the potential aesthetic and functional outcomes before making any physical incisions. This iterative planning process ensures precise measurement of bone reductions or augmentations, guaranteeing that the final contours align not only with feminizing principles but also with the patient’s specific reconstructive needs. For example, customized cutting guides and drilling templates can be virtually designed and subsequently 3D printed, which are then used intraoperatively to execute the planned osteotomies with remarkable accuracy, thereby minimizing human error and enhancing surgical precision (Barnett et al., 2023).

Beyond virtual planning, the emerging role of artificial intelligence (AI) in preoperative morphing offers further advancements. AI-based software, such as DeepSurface AI, can generate three-dimensional morphs of the patient’s face, which can then be adjusted in real-time to demonstrate potential surgical outcomes across various facial regions (Barnett et al., 2023). While still an evolving area requiring further research, this technology holds immense potential for aligning patient expectations with realistic surgical possibilities, fostering more effective communication between patient and surgeon regarding desired goals.

Moreover, intraoperative navigation systems further enhance precision during the actual surgery. These systems, often likened to a GPS for the surgeon, track the exact position of surgical instruments in real-time relative to the patient’s anatomy and the pre-planned virtual model. This continuous validation of instrument placement and bone repositioning ensures that the surgery adheres precisely to the virtual plan, even in complex cases with distorted or atypical anatomy. The amalgamation of advanced imaging, virtual surgical planning, and intraoperative navigation systems not only significantly improves the accuracy, safety, and efficiency of facial feminization surgery but also substantially enhances the predictability of outcomes, ultimately leading to higher patient satisfaction and profoundly natural-looking results.

Intraoperative Considerations and Challenges in Complex Feminization Procedures

The execution of complex facial feminization surgery, particularly for patients with significant skeletal variations or previous interventions, presents a unique and demanding set of intraoperative considerations and challenges. These circumstances require not only exceptional surgical skill but also considerable adaptability and a deep understanding of anatomical variations. Unlike more routine aesthetic procedures, these cases often involve highly altered or atypical anatomy, which can obscure normal surgical landmarks and significantly increase the complexity of dissection and bone manipulation. The surgeon must be prepared to navigate unexpected findings and adjust the pre-planned strategy in real-time while maintaining the overarching feminization goals.

One of the most critical challenges lies in the meticulous management and preservation of vital neurovascular structures. The facial nerve and its numerous delicate branches, which control facial expressions, are particularly vulnerable during extensive soft tissue dissection and bone reshaping in regions like the midface and jawline. Similarly, branches of the trigeminal nerve, responsible for sensation, can be at risk, potentially leading to temporary or permanent numbness or altered sensation. Precise knowledge of anatomical variations in nerve pathways, which can occur as highlighted by Alraddadi (2021), coupled with meticulous surgical technique, is crucial to preserve nerve function and minimize the risks of facial paralysis or sensory deficits. The judicious use of intraoperative nerve monitoring can serve as an invaluable tool, providing real-time feedback to help identify and protect these delicate structures during complex dissections.

Vascular concerns are also heightened in reconstructive and extensive feminization cases. Tissues that have been scarred from previous surgeries or subjected to trauma may have a compromised blood supply, increasing the risk of flap necrosis, delayed wound healing, or excessive intraoperative bleeding. Careful, controlled dissection, gentle tissue handling, and meticulous hemostasis are paramount to preserve the delicate vascular network. When large bone grafts are utilized, ensuring adequate vascularity of the recipient bed is absolutely critical for graft survival and successful integration. In situations with severely compromised blood supply, specialized techniques such as vascularized bone grafts, where a segment of bone is transplanted along with its nourishing artery and vein and reconnected using microsurgical techniques, may be required. This represents the pinnacle of reconstructive artistry but also significantly increases operative time and technical demands.

Managing inherent anatomical variations is another significant hurdle. As Alraddadi (2021) emphasizes, anatomical variations are normal presentations but can greatly influence clinical practice outcomes. No two cases of facial skeletal deficiency or dimorphism are identical, requiring surgeons to adapt their techniques dynamically to the unique presentation. While advanced virtual surgical planning provides a robust roadmap, the reality of the operating field can still present unforeseen anatomical deviations. This necessitates a surgeon with extensive experience in craniofacial and reconstructive surgery who can make informed, rapid decisions, potentially deviating from the initial plan if necessary, without compromising safety or aesthetic objectives. Factors such as unexpected bone density, the presence of fibrous scar tissue, or unusual sinus anatomy can all influence the precise execution of osteotomies and the stability of plate fixation strategies. Furthermore, achieving precise symmetry and harmonious contours in a face that may already be distorted requires continuous intraoperative assessment, often involving repeated visual inspection and palpation to ensure that bone reductions, advancements, or augmentations are balanced and aligned with the feminizing goals. The sheer volume and intricacy of combined bone and soft tissue work can lead to prolonged operative times, which in turn increases the risks associated with general anesthesia and overall patient recovery. Therefore, a highly coordinated surgical team, efficient instrumentation, and judicious patient selection based on a thorough preoperative assessment are essential prerequisites for successfully navigating these intraoperative complexities and achieving optimal, safe, and transformative results.

Post-Operative Recovery and Long-Term Management: Nurturing the Transformation

The post-operative phase following comprehensive facial feminization surgery, particularly when complex bone and soft tissue modifications have been performed, is a critical period that demands meticulous care, patience, and a well-structured management plan. The recovery timeline for extensive procedures is typically more protracted and can be more intense compared to standard aesthetic interventions, given the significant degree of bone manipulation, tissue reshaping, and potential for extensive swelling and bruising. Patients must be thoroughly prepared for this journey, understanding that the immediate post-operative appearance will evolve considerably over weeks and months.

Immediately after surgery, patients can expect substantial facial swelling, bruising, and discomfort. Swelling is an almost universal physiological response to surgical trauma and is typically most pronounced in the first few days to a week after surgery, gradually subsiding over several weeks to months. Full resolution of residual swelling, especially in areas of significant bone work or grafting, can take up to a year or even longer for the final contours to fully emerge. Bruising will similarly resolve, usually within 2 to 4 weeks, with color changes from purplish-black to greenish-yellow before fading completely. Pain management is crucial and is typically achieved through a combination of prescribed analgesia, anti-inflammatory medications, and diligent application of cold compresses, which help to minimize swelling and alleviate discomfort. Hospitalization may extend for several days, particularly after complex osteotomies or large graft placements, allowing for close monitoring of vital signs, early detection of potential complications such as hematoma or infection, and effective pain control.

Specific post-operative care instructions are tailored to the procedures performed. For individuals undergoing jaw or chin osteotomies, a soft or liquid diet is often prescribed for several weeks to prevent undue stress on the healing bone segments and intraoral incisions. Meticulous oral hygiene, often involving antimicrobial mouth rinses, is paramount to prevent infection in the oral cavity. Activity restrictions are stringent in the initial weeks; patients are advised to avoid strenuous activities, heavy lifting, and anything that might elevate blood pressure or stress the healing facial structures. Gradually, activity levels are increased as recovery progresses and clearance is given by the surgical team. Head elevation, even during sleep, is strongly recommended for several weeks to optimize lymphatic drainage and reduce swelling. Physical therapy or gentle lymphatic drainage massages may also be recommended in later stages of recovery to help expedite the resolution of swelling and improve soft tissue suppleness.

Complex reconstructive procedures inherently carry potential complications beyond those of standard aesthetic surgery. While surgeons employ meticulous techniques to mitigate these, awareness and diligent monitoring are essential. Graft resorption, where a portion of transplanted autologous bone may be reabsorbed by the body, can lead to a partial loss of contour or volume, occasionally necessitating revision. For alloplastic implants, potential risks include implant exposure or infection, which can compromise implant integration and in severe cases require removal. Non-union or malunion of osteotomies, though rare, can occur if bone segments fail to heal properly, potentially leading to persistent asymmetry or functional issues, often requiring further surgical correction. Nerve damage, despite careful intraoperative preservation efforts, can manifest post-operatively as persistent numbness, altered sensation, or, in rare instances, motor weakness, particularly affecting facial expressions. Long-term stability expectations are a crucial aspect of patient counseling. While the extensive bone reshaping in feminization surgery provides a stable and lasting foundation, facial structures continue to undergo natural aging processes. Soft tissue changes due to aging, weight fluctuations, or continued hormonal therapy may necessitate minor revisions or non-surgical touch-ups years after the initial surgery. Regular follow-up appointments are therefore essential for monitoring the long-term integrity of the reconstruction, addressing any emerging concerns, and ensuring sustained patient satisfaction. A commitment to ongoing care and realistic long-term expectations are vital components of a successful and enduring facial feminization journey.

Functional and Aesthetic Restoration: Comprehensive Outcomes Beyond Appearance

The overarching goal of advanced facial feminization surgery, particularly when addressing severe facial skeletal deficiencies stemming from congenital anomalies, trauma, or complex developmental variations, extends far beyond mere aesthetic transformation. While the visual alignment of external features with an individual’s gender identity is paramount, equally significant is the comprehensive restoration of optimal facial function. For patients presenting with pre-existing functional impairments, the journey through feminization surgery offers a profound opportunity to simultaneously regain or improve vital physiological capabilities, thereby enhancing their overall quality of life and facilitating more seamless social interaction.

Functional impairments in such complex cases can be diverse and significantly impact daily life. These may include difficulties with mastication (chewing) due to severe jaw misalignment or temporomandibular joint (TMJ) dysfunction, which can be addressed through precise mandibular and maxillary osteotomies that not only feminize the jawline but also restore proper dental occlusion. Compromised vision or ocular discomfort arising from orbital dystopia (misplaced eyes) or malposition of the infraorbital rim can be alleviated through meticulous reconstruction of the orbital region, providing better support and protection for the eyes. Impaired breathing, often a consequence of severe nasal obstruction, septal deviation, or midface hypoplasia, can be corrected through comprehensive rhinoplasty that improves nasal airflow while simultaneously creating a more delicate nasal appearance (Barnett et al., 2023). Speech impediments, occasionally arising from abnormal oral or pharyngeal anatomy related to skeletal discrepancies, can also see improvements following corrective osseous surgery in the jaw and midface.

Therefore, a truly successful facial feminization outcome in these advanced cases is defined by the synergistic achievement of both highly feminine aesthetics and robust, enduring functional recovery. The intricate bone work, encompassing complex osteotomies, the strategic use of autologous bone grafts, and custom implant placements, plays a direct and foundational role in re-establishing proper skeletal support for these critical facial structures. For instance, correcting mandibular discrepancies not only sculpts a softer, more tapered jawline but critically restores proper dental occlusion and chewing efficiency, enabling better nutrition and comfort. Reconstructing the orbital rims and midface enhances visual field and provides improved protection for the eyes, while thoughtful rhinoplasty, beyond creating a more delicate nasal appearance, actively improves nasal airflow and respiratory function (Barnett et al., 2023). The integration of precise soft tissue management techniques further refines both outcomes. Accurate redraping of the skin, muscle, and fat over the newly contoured skeletal framework ensures natural-looking transitions and minimizes visible surgical evidence, contributing to a harmonious appearance that moves naturally with expression. Autologous fat grafting, beyond its aesthetic benefits of adding feminine volume to areas like the cheeks and lips, can also significantly improve local tissue quality, camouflage minor irregularities, and potentially enhance vascularity, further contributing to durable functional and aesthetic integration.

The meticulous preoperative planning involved, utilizing high-resolution 3D virtual surgical planning and intraoperative navigation, contributes profoundly to achieving this dual objective. By precisely defining bone movements, predicting soft tissue redraping, and mapping graft placements, surgeons can optimize both the feminizing aesthetic and the structural integrity necessary for restored function. Patient-reported outcome measures consistently demonstrate that individuals undergoing comprehensive facial feminization experience significant psychological benefits, including a profound reduction in gender dysphoria, improved self-esteem, and enhanced body image (Barnett et al., 2023). However, in reconstructive cases, these psychological gains are often compounded by the transformative impact of regaining lost or never-had functions, which further enhances overall quality of life, fosters greater independence, and facilitates more confident integration into society. The remarkable ability of modern reconstructive feminization surgery to simultaneously sculpt a face that is aesthetically feminine and fully functional represents the pinnacle of contemporary craniofacial and gender-affirming surgical practice, offering truly life-changing results for those facing the most profound anatomical challenges.

Selecting a Specialist: The Critical Choice for Complex Feminization

The decision to undergo advanced reconstructive facial feminization surgery for severe facial skeletal deficiencies is one of monumental significance, necessitating the selection of a highly specialized and exceptionally experienced surgeon. The inherent complexity of these cases demands a level of expertise that extends far beyond the scope of a general plastic surgeon or even one whose practice is solely focused on aesthetic feminization. Therefore, the paramount importance of choosing a surgeon with dual proficiency—deeply rooted in both routine facial feminization procedures and intricate maxillofacial reconstruction—cannot be overstated. Such a specialist possesses an unparalleled understanding of complex craniofacial anatomy, the biomechanics of bone remodeling and healing, and advanced reconstructive techniques, including microvascular surgery when vascularized grafts are indicated for compromised tissues (Dr. MFO, 2025a).

These highly specialized surgeons are adept at managing large skeletal defects, correcting severe congenital or acquired asymmetries, and precisely reconstructing compromised facial units. Crucially, this dual expertise means the surgeon not only understands how to create aesthetically pleasing feminine contours but also possesses the foundational knowledge and technical skill to rebuild a stable and functional facial framework from a significantly compromised or deficient starting point. This includes profound proficiency in performing complex osteotomies with precision, implementing advanced bone grafting techniques using either autologous tissue or customized alloplastic materials, and the expert deployment of custom implants to restore lost volume and projection. Their training often encompasses a blend of plastic surgery, oral and maxillofacial surgery, and dedicated craniofacial fellowship training, providing a robust skill set for the most challenging anatomical situations.

Furthermore, an ideal reconstructive feminization surgeon will be exceptionally well-versed in utilizing cutting-edge technologies that enhance precision and safety. This includes a mastery of high-resolution 3D virtual surgical planning (VSP) systems, the ability to design and utilize custom surgical guides and drilling templates, and proficiency with intraoperative navigation systems (Barnett et al., 2023). Their capacity to leverage these advanced tools ensures optimal surgical accuracy, minimizes potential risks, and maximizes the predictability of outcomes, particularly in scenarios characterized by distorted or atypical anatomy. Beyond technical skill, the most effective specialist will demonstrate a profoundly patient-centered approach. This involves engaging in thorough and empathetic consultations to fully understand the individual’s unique goals, specific concerns, and psychological needs. They are committed to providing realistic expectations regarding the surgical process, the nuances of recovery, and the potential long-term outcomes, which is especially vital given the inherent complexities and extended recovery periods of reconstructive cases. Verifying the surgeon’s credentials, including board certification in relevant surgical specialties and a comprehensive portfolio demonstrating successful outcomes in challenging reconstructive cases, is an essential step for prospective patients. Consulting with a surgeon who works within or collaborates with a multidisciplinary team, potentially including oral surgeons, orthodontists, and mental health professionals, further ensures a holistic and comprehensive approach to care, addressing all facets of the patient’s well-being. Ultimately, the selection of such a highly experienced and uniquely qualified surgeon is the single most critical factor in achieving safe, functional, aesthetically transformative, and enduring results in advanced reconstructive facial feminization surgery, providing patients with the confidence that their complex needs are in expert hands.

A close-up portrait of a woman with long brown hair, looking directly at the camera with a serious expression. The image has a dramatic lighting effect with blue and orange hues.

Conclusion: The Critical Role of Individualized Anatomical Strategy

The journey through facial feminization surgery is a profoundly personal and meticulously orchestrated process, uniquely shaped by each individual’s distinct facial anatomy. As this comprehensive exploration has underscored, achieving natural, harmonious, and enduring results in feminization requires far more than a generalized approach; it demands an intricate understanding of the subtle and overt differences in skeletal and soft tissue structures that define facial gender. The ability to precisely assess, plan, and execute surgical modifications based on a patient’s unique biological blueprint is the hallmark of truly transformative and successful outcomes. We have delved into how variations in the frontal bone and orbital rims dictate specific forehead contouring techniques, how midface projection influences strategies for cheek augmentation or reduction, and how the intricate cartilaginous and bony framework of the nose guides delicate rhinoplasty procedures. Similarly, the diverse forms of the mandible and chin necessitate highly individualized jawline and chin reshaping, while the laryngeal prominence requires careful reduction. Each of these regional modifications, when viewed in isolation, contributes to feminization, but their true power emerges from their synergistic integration.

The advancements in preoperative planning, particularly the integration of high-resolution 3D imaging and virtual surgical planning systems, have revolutionized the field, allowing surgeons to create highly detailed blueprints of the desired transformation. This technological synergy enhances precision, minimizes risks, and optimizes predictability, transitioning complex cases from challenging guesswork to precisely engineered solutions. Intraoperative challenges, such as the meticulous preservation of neurovascular structures and the dynamic adaptation to anatomical variations, underscore the demanding nature of these procedures and highlight the critical role of profound surgical experience. Furthermore, the post-operative recovery, often protracted and intensive, requires a comprehensive and patient-centered management plan to ensure optimal healing and long-term stability. Beyond the aesthetic alterations, successful facial feminization inherently encompasses the restoration or improvement of vital facial functions, addressing potential impairments related to mastication, vision, and breathing. This dual emphasis on form and function ensures that the patient not only achieves an external appearance congruent with their identity but also experiences a significant enhancement in overall quality of life.

The selection of a highly specialized surgeon, one possessing deep expertise in both facial feminization and complex maxillofacial reconstruction, stands as the single most critical decision for individuals embarking on this journey. Their unique skill set, combining artistic vision with a profound anatomical understanding, is indispensable for navigating the intricacies of advanced cases and delivering results that are both safe and aesthetically profound. Ultimately, facial feminization surgery, particularly when tailored to the individual’s unique anatomy, is a powerful affirmation of identity, fostering self-confidence and providing a deeper sense of authenticity. It is a testament to the continuous evolution of surgical science and artistry, offering life-changing possibilities for those seeking harmony between their inner self and outer presentation. The ongoing commitment to precision, personalized care, and comprehensive outcomes will continue to define this vital and transformative field, providing hope and tangible results for countless individuals.

Frequently Asked Questions

Why is individual facial anatomy so important in planning facial feminization surgery?

Individual facial anatomy is crucial because every face is unique, with varying bone structures and soft tissue distributions. A personalized surgical strategy, tailored to these specific anatomical nuances, ensures the most natural, harmonious, and effective feminization outcomes, as opposed to a generic approach.

What role do 3D imaging and virtual surgical planning play in customizing facial feminization procedures?

3D imaging, such as CT scans, provides a detailed blueprint of the patient’s skeletal and soft tissue architecture. Virtual surgical planning software allows surgeons to simulate procedures, precisely measure modifications, and design custom guides, significantly enhancing surgical precision, safety, and predictability.

How do bone modifications and soft tissue procedures interact synergistically in facial feminization?

Bone modifications (e.g., forehead contouring, jaw reduction) provide the foundational changes, redefining the facial framework. Soft tissue procedures (e.g., rhinoplasty, cheek augmentation, lip lifts) then refine these contours, add volume, and enhance expressions. Their synergistic combination ensures a cohesive, balanced, and naturally feminine appearance.

What are some of the critical challenges faced during complex facial feminization surgeries?

Challenges include meticulous preservation of vital neurovascular structures (like facial nerves), managing compromised blood supply in scarred tissues, adapting to unexpected anatomical variations, and ensuring precise symmetry. These demand exceptional surgical skill and adaptability.

What kind of recovery can be expected after extensive facial feminization surgery?

Recovery from extensive procedures typically involves significant swelling, bruising, and discomfort, which gradually subside over weeks to months. Full resolution of swelling and bone healing can take up to a year or more. Adherence to post-operative care, including rest, head elevation, and a soft diet, is crucial.

Beyond aesthetics, what other benefits does facial feminization surgery offer?

Beyond aesthetic alignment, facial feminization surgery can significantly improve or restore vital facial functions such as mastication (chewing), vision, and breathing, especially in cases of pre-existing skeletal deficiencies. This dual focus enhances overall quality of life, reduces psychological distress, and fosters greater social confidence.

What qualifications should one look for in a surgeon for complex facial feminization?

For complex cases, seek a surgeon with dual proficiency in both routine facial feminization and intricate maxillofacial reconstruction. This specialist should have extensive experience, board certification in relevant specialties, a strong portfolio of results, and expertise in advanced technologies like 3D virtual surgical planning.

Bibliography

  • Alraddadi, A. (2021). Literature Review of Anatomical Variations: Clinical Significance, Identification Approach, and Teaching Strategies. Cureus, 13(4), e14451. https://pmc.ncbi.nlm.nih.gov/articles/PMC8117423/
  • Barnett, S. L., Choe, J., Aiello, C., & Bradley, J. P. (2023). Facial Feminization Surgery: Anatomical Differences, Preoperative Planning, Techniques, and Ethical Considerations. Medicina (Kaunas), 59(12), 2070. https://pmc.ncbi.nlm.nih.gov/articles/PMC10744788/
  • Dr. MFO. (2025a, October 13). Advanced Reconstructive FFS: Surgical Techniques for Severe Facial Skeletal Deficiencies. https://www.dr-mfo.com/advanced-reconstructive-ffs-surgical-techniques/
  • Dr. MFO. (2025b, July 4). Key Anatomical Considerations for Combined Nose and Cheek Procedures in Transgender FFS. https://www.dr-mfo.com/combined-nose-cheek-ffs-anatomical-considerations/
  • Dr. MFO. (2025c, July 10). FFS Procedures: Bone vs. Soft Tissue Modification for Facial Feminization. https://www.dr-mfo.com/ffs-procedures-bone-vs-soft-tissue-modification/

  • Klarity Health Library. (2025, March 5). Orthopedic Manifestations Of Femoral-Facial Syndrome. https://my.klarity.health/orthopedic-manifestations-of-femoral-facial-syndrome/

Anesthesia in FFS: Types, Safety, and Recovery Guide

A person in a green uniform and gloves interacting with a medical or scientific machine featuring a digital display and various controls.

Anesthesia is a critical component of Facial Feminization Surgery (FFS), ensuring patient comfort, immobility, and safety during complex procedures. As FFS involves multiple surgical interventions to reshape facial features, the choice of anesthesia plays a pivotal role in achieving optimal outcomes while minimizing risks. This guide explores the types of anesthesia used in FFS, their administration, safety considerations, and what patients can expect during and after the procedure.

FFS is a transformative process for many transgender individuals, and anesthesia is tailored to meet the unique needs of each patient. Whether it’s general anesthesia for extensive procedures or local anesthesia with sedation for minor adjustments, understanding the options and their implications is essential for informed decision-making. This article provides a comprehensive overview of anesthesia in FFS, emphasizing safety, preparation, and recovery.

Anesthesia in FFS: Types, Safety, and Recovery Guide

Types of Anesthesia Used in FFS

General Anesthesia

General anesthesia is the most commonly used type of anesthesia in FFS, particularly for comprehensive procedures that require extensive surgical intervention. It induces a state of controlled unconsciousness, ensuring the patient feels no pain and remains completely still during the operation. This is crucial for procedures like forehead contouring, jaw reshaping, and tracheal shaving, which require precision and prolonged operating times.

How It Works: General anesthesia is administered through a combination of intravenous (IV) medications and inhaled gases. The anesthesiologist carefully monitors the patient’s vital signs, including heart rate, blood pressure, oxygen levels, and breathing, throughout the procedure. Intubation, the insertion of a breathing tube, is often required to maintain a clear airway and ensure adequate oxygen supply.

Advantages for FFS: General anesthesia provides complete immobility and pain control, which is essential for intricate facial surgeries. It allows surgeons to perform lengthy procedures without interruption, ensuring optimal results. Additionally, it enables the anesthesiologist to manage the patient’s airway effectively, particularly important in FFS due to potential swelling and the risk of airway obstruction.

Monitoring During General Anesthesia: During the procedure, the anesthesia team continuously monitors the patient’s vital signs using advanced equipment. This includes tracking heart rate, blood pressure, oxygen saturation, end-tidal CO2 levels, and body temperature. Any deviations from normal ranges are promptly addressed to maintain patient safety.

Local Anesthesia with Sedation

Local anesthesia with sedation is an alternative for minor FFS procedures or as an adjunct to general anesthesia. It involves numbing a specific area of the face while keeping the patient relaxed and comfortable. This approach is often used for less invasive procedures such as lip lifts or minor chin adjustments.

When It Might Be Used: Local anesthesia with sedation is ideal for shorter, less complex procedures where general anesthesia is not necessary. It is also used in conjunction with general anesthesia to enhance pain control during recovery. For example, a surgeon may inject local anesthesia at the surgical site to reduce post-operative pain.

Patient Experience: Patients under local anesthesia with sedation remain conscious but deeply relaxed. They may feel drowsy and detached from the procedure but can still respond to verbal cues. This type of anesthesia is administered through IV medications that induce sedation, combined with local anesthetics injected into the surgical area to block pain signals.

A graph displaying multiple colored lines, likely representing data trends over time. The graph includes green, blue, and yellow lines, each showing different patterns and fluctuations.

Anesthesia Administration and Monitoring During FFS

Pre-Operative Assessment

The pre-operative assessment is a critical step in ensuring the safety and effectiveness of anesthesia during FFS. This assessment includes a thorough review of the patient’s medical history, current medications, allergies, and previous experiences with anesthesia. The anesthesiologist will also conduct a physical examination and may order laboratory tests to evaluate the patient’s overall health.

Key Components of Pre-Operative Assessment:

  • Medical history review, including chronic conditions such as diabetes, heart disease, or respiratory issues.
  • Evaluation of current medications, including prescription drugs, over-the-counter medications, and supplements.
  • Assessment of allergies, particularly to anesthetics or other medications.
  • Review of previous anesthesia experiences, including any adverse reactions.
  • Physical examination to check for signs of conditions that could complicate anesthesia, such as sleep apnea or obesity.
  • Laboratory tests, such as blood tests and electrocardiograms (ECGs), to assess organ function and overall health.

Role of the Anesthesiologist/Anesthetist

The anesthesiologist or certified registered nurse anesthetist (CRNA) plays a central role in the administration and monitoring of anesthesia during FFS. Their responsibilities include:

  • Selecting the appropriate type and dosage of anesthesia based on the patient’s health and the complexity of the procedure.
  • Administering anesthesia and monitoring the patient’s vital signs throughout the surgery.
  • Managing the patient’s airway, particularly in procedures involving the face and neck, where swelling can pose risks.
  • Adjusting anesthesia levels as needed to ensure the patient remains comfortable and stable.
  • Providing post-operative pain management and monitoring the patient’s recovery from anesthesia.

Intraoperative Monitoring

During FFS, continuous monitoring of the patient’s vital signs is essential to ensure their safety. The anesthesia team uses advanced equipment to track:

  • Heart Rate and Rhythm: Monitored via electrocardiogram (ECG) to detect any irregularities.
  • Blood Pressure: Measured continuously to ensure it remains within a safe range.
  • Oxygen Saturation: Tracked using a pulse oximeter to ensure adequate oxygen levels in the blood.
  • End-Tidal CO2: Monitored to assess the effectiveness of ventilation and detect any issues with breathing.
  • Body Temperature: Maintained within a normal range to prevent hypothermia or hyperthermia.

In addition to these vital signs, the anesthesia team may also monitor brain activity in complex cases to ensure the patient remains at the appropriate level of unconsciousness.

Specific Considerations for FFS

FFS presents unique challenges for anesthesia administration due to the nature of the procedures and the areas of the body involved. Key considerations include:

  • Airway Management: Facial surgeries, particularly those involving the jaw, nose, or throat, can lead to swelling that may obstruct the airway. The anesthesia team must be prepared to manage the airway effectively, potentially using advanced techniques such as fiberoptic intubation.
  • Prolonged Procedures: FFS often involves multiple procedures performed in a single session, which can extend the duration of anesthesia. Prolonged anesthesia requires careful monitoring to prevent complications such as pressure sores, nerve damage, or fluid imbalances.
  • Interaction with Medications: Patients undergoing FFS may be taking hormone replacement therapy (HRT) or other medications that can interact with anesthetics. The anesthesia team must be aware of these interactions to adjust anesthesia dosages accordingly.
A bottle labeled 'LIQUID LIQUID ANESTHETIC' with dosage information and a syringe containing a drop of liquid next to it.

Risks and Complications Associated with Anesthesia in FFS

General Anesthesia Risks

While general anesthesia is generally safe, it carries potential risks, particularly for patients with underlying health conditions. Common risks associated with general anesthesia include:

  • Nausea and Vomiting: Post-operative nausea and vomiting (PONV) are common side effects of general anesthesia. Medications can be administered to reduce these symptoms.
  • Sore Throat: Intubation can cause irritation and soreness in the throat, which typically resolves within a few days.
  • Dental Injury: The insertion of the breathing tube can sometimes cause minor dental injuries, such as chipped teeth or lip damage.
  • Allergic Reactions: Rarely, patients may experience allergic reactions to anesthetic medications. The anesthesia team is prepared to manage such reactions with emergency medications.
  • Anesthesia Awareness: In extremely rare cases, patients may regain consciousness during surgery but remain unable to move or communicate. This phenomenon, known as anesthesia awareness, can be traumatic and is carefully monitored to prevent its occurrence.

FFS-Specific Risks

FFS procedures introduce additional risks due to the complexity and duration of the surgeries. These include:

  • Interaction with HRT: Hormone replacement therapy can affect blood clotting and metabolism, potentially influencing the patient’s response to anesthesia. The anesthesia team must account for these interactions when planning the anesthesia protocol.
  • Prolonged Recovery from Sedatives: Patients undergoing extensive FFS may require higher doses of sedatives, which can lead to prolonged recovery times and increased grogginess post-surgery.
  • Airway Obstruction: Swelling in the facial and neck regions can obstruct the airway, particularly in procedures involving the jaw or trachea. The anesthesia team must be vigilant in managing the airway to prevent complications.

Minimizing Risks

The anesthesia team employs several strategies to minimize risks during FFS:

  • Thorough Pre-Operative Assessment: Identifying potential risks before surgery allows the team to tailor the anesthesia plan to the patient’s specific needs.
  • Advanced Monitoring Equipment: Continuous monitoring of vital signs ensures any deviations are detected and addressed promptly.
  • Experienced Anesthesia Providers: Anesthesiologists and CRNAs with experience in FFS are better equipped to manage the unique challenges of these procedures.
  • Post-Operative Care: Close monitoring during recovery helps manage pain and prevent complications such as nausea, vomiting, or airway obstruction.

Post-Operative Anesthesia Recovery

Coming Out of Anesthesia

As the effects of anesthesia wear off, patients gradually regain consciousness. This process is carefully managed by the anesthesia team to ensure a smooth transition. Patients may experience grogginess, confusion, or disorientation as they wake up, which is normal and typically resolves within a few hours.

Common Sensations During Recovery:

  • Grogginess: Patients may feel drowsy and slow to respond as the sedatives wear off.
  • Nausea: Post-operative nausea is common but can be managed with anti-nausea medications.
  • Dry Mouth or Sore Throat: These symptoms are typical after intubation and usually resolve within a day or two.
  • Muscle Aches: Prolonged immobility during surgery can lead to muscle stiffness and discomfort.
  • Shivering: Some patients experience shivering as their body temperature regulates post-surgery.

Pain Management Immediately After Surgery

Pain management is a critical aspect of post-operative care in FFS. The anesthesia team works closely with the surgical team to ensure patients are comfortable as they recover. Pain relief strategies may include:

  • Local Anesthetics: Injected at the surgical site to numb pain during the initial recovery period.
  • Oral or IV Pain Medications: Prescribed to manage pain as the local anesthetics wear off.
  • Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): Used to reduce inflammation and discomfort.
  • Patient-Controlled Analgesia (PCA): Allows patients to self-administer pain medication within safe limits using a pump.

Monitoring in the Recovery Room

After surgery, patients are transferred to a recovery room where they are closely monitored by the anesthesia and nursing teams. Key aspects of recovery room monitoring include:

  • Vital Signs: Continuous tracking of heart rate, blood pressure, oxygen levels, and temperature.
  • Pain Levels: Regular assessment of pain to adjust medications as needed.
  • Airway Patency: Ensuring the airway remains clear, particularly in patients who have undergone facial or neck procedures.
  • Fluid Balance: Monitoring hydration and managing IV fluids to prevent dehydration or fluid overload.
  • Nausea and Vomiting: Administering anti-nausea medications and ensuring the patient is comfortable.

Patient Preparation for Anesthesia

Fasting Instructions

Patients are typically instructed to fast for a specified period before surgery to reduce the risk of aspiration, which occurs when stomach contents enter the lungs. General fasting guidelines include:

  • Solid Foods: Avoid eating solid foods for at least 8 hours before surgery.
  • Clear Liquids: Water, black coffee, or clear juices may be allowed up to 2 hours before surgery, but patients should follow their surgeon’s specific instructions.
  • Medications: Some medications may be taken with a sip of water as directed by the anesthesia team.

Medication Management Before Surgery

Patients should inform their anesthesia team about all medications they are taking, including prescription drugs, over-the-counter medications, and supplements. Some medications may need to be adjusted or temporarily discontinued before surgery, including:

  • Blood Thinners: Medications such as aspirin, warfarin, or clopidogrel may increase the risk of bleeding and may need to be stopped before surgery.
  • Hormone Replacement Therapy (HRT):** Hormonal medications may interact with anesthetics and should be discussed with the anesthesia team.

Communicating Concerns to the Anesthesia Team

Open communication with the anesthesia team is essential for a safe and successful surgical experience. Patients should discuss any concerns or questions they have, including:

  • Previous Anesthesia Experiences: Inform the team about any past reactions or complications with anesthesia.
  • Allergies: Disclose any known allergies to medications, latex, or other substances.
  • Medical Conditions: Share information about chronic conditions such as heart disease, respiratory issues, or sleep apnea.
  • Smoking or Alcohol Use: These can affect anesthesia and should be discussed with the team.
  • Pregnancy or Breastfeeding: Inform the team if you are pregnant, breastfeeding, or suspect you might be pregnant.
A smiling patient in a hospital gown sits next to a healthcare professional in a white coat, likely discussing treatment in a clinical setting.

Conclusion

Anesthesia is a cornerstone of Facial Feminization Surgery, enabling patients to undergo transformative procedures with comfort and safety. Understanding the types of anesthesia used, their administration, and the associated risks empowers patients to make informed decisions and prepares them for a smooth surgical experience. General anesthesia is the most common choice for comprehensive FFS, providing complete pain control and immobility, while local anesthesia with sedation may be used for minor procedures.

The role of the anesthesia team is pivotal in ensuring patient safety and comfort throughout the procedure. From pre-operative assessments to intraoperative monitoring and post-operative care, their expertise minimizes risks and enhances recovery. Patients can contribute to a successful outcome by following pre-operative instructions, communicating openly with their anesthesia team, and adhering to post-operative care guidelines.

For those considering FFS, consulting with an experienced anesthesiologist and surgical team is essential. By addressing concerns, understanding the process, and preparing thoroughly, patients can approach their FFS journey with confidence and peace of mind.

Key Takeaways

  • Anesthesia is essential for ensuring patient comfort and safety during FFS procedures.
  • General anesthesia is the most common type used in FFS, providing complete pain control and immobility.
  • Local anesthesia with sedation may be used for minor procedures or as an adjunct to general anesthesia.
  • Pre-operative assessments and continuous monitoring during surgery are critical for minimizing risks.
  • Post-operative care focuses on managing pain, preventing complications, and ensuring a smooth recovery.
  • Open communication with the anesthesia team is vital for addressing concerns and tailoring the anesthesia plan to the patient’s needs.

Next Steps

If you are considering FFS, the next step is to schedule a consultation with a board-certified plastic surgeon and anesthesiologist. During this consultation, you can discuss your goals, review your medical history, and develop a personalized anesthesia plan. Preparing thoroughly and following your surgical team’s guidelines will help ensure a safe and successful FFS experience.

Frequently Asked Questions

What type of anesthesia is used in FFS?

General anesthesia is most commonly used in FFS to ensure the patient is completely unconscious and pain-free during extensive procedures. Local anesthesia with sedation may be used for minor adjustments or as an adjunct to general anesthesia.

How long does it take to recover from anesthesia after FFS?

Recovery time varies depending on the type of anesthesia used. Patients typically regain full alertness within a few hours after general anesthesia, but some grogginess and fatigue may persist for up to 24 hours. Local anesthesia with sedation has a shorter recovery time.

What are the risks of anesthesia in FFS?

Risks include nausea, vomiting, sore throat, and allergic reactions. FFS-specific risks include airway obstruction due to facial swelling and interactions with hormone replacement therapy. These risks are minimized through thorough pre-operative assessments and continuous monitoring.

Can I eat or drink before FFS surgery?

Patients are typically instructed to fast for at least 8 hours before surgery to reduce the risk of aspiration. Clear liquids may be allowed up to 2 hours before the procedure, but specific instructions should be followed as provided by the anesthesia team.

How is pain managed after FFS?

Pain management strategies include local anesthetics injected at the surgical site, oral or IV pain medications, and non-steroidal anti-inflammatory drugs (NSAIDs). The anesthesia team works closely with the surgical team to ensure patients are comfortable during recovery.

What should I discuss with my anesthesiologist before FFS?

Patients should discuss their medical history, current medications, allergies, and any previous experiences with anesthesia. It’s also important to share information about hormone replacement therapy, smoking or alcohol use, and any chronic conditions.

Bibliography

For further reading and verification, refer to the following sources:

  • Cleveland Clinic. (2025). General Anesthesia. Retrieved from
  • Mayo Clinic. (2025). General Anesthesia. Retrieved from
  • National Institute of General Medical Sciences. (2023). Anesthesia. Retrieved from
  • MedlinePlus. (2025). Anesthesia. Retrieved from
  • Everyday Health. (2025). Anesthesia: Types, Risks, and What to Expect. Retrieved from
  • Medical News Today. (2025). What is Anesthesia, and What Does It Involve? Retrieved from